Related Experiment Video
Updated: Aug 6, 2026
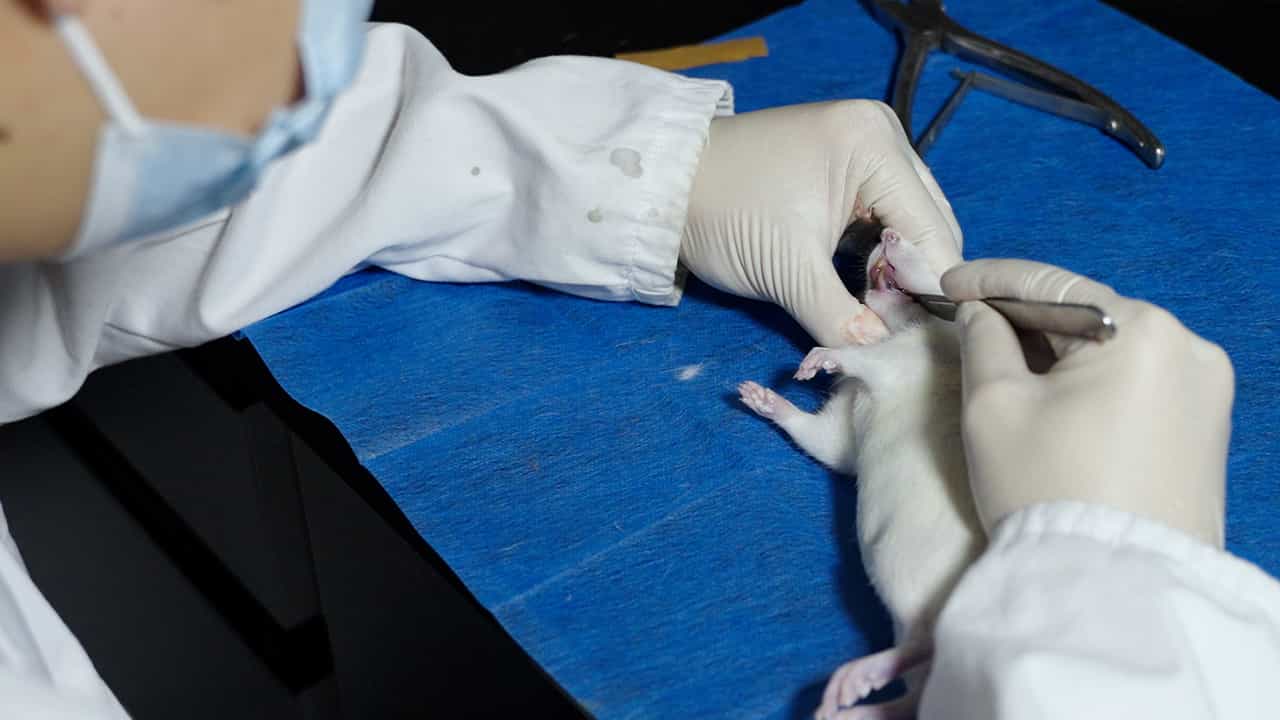
Immunofluorescent Labeling in Nasal Mucosa Tissue Sections of Allergic Rhinitis Rats via Multicolor Immunoassay
Published on: September 22, 2023
Allergic rhinitis is the strongest independent predictor of obstructive sleep apnea severity in preschool children
1Department of Otorhinolaryngology, The Second Affiliated Hospital, Yuying Children's Hospital of Wenzhou Medical University, Wenzhou, China.

Objective:
It is known that both adenoid hypertrophy (AH) and allergic rhinitis (AR) can cause obstructive sleep apnea (OSA), but their relative importance, especially when tonsil size is considered, remains unclear. This study aimed to compare the independent contributions of AR, AH, and tonsil hypertrophy to OSA severity and to determine the primary contributing factor.
Method:
A total of 177 children aged 3 to 6 were included in the study. They were divided into four groups based on adenoid size (nasal endoscopic obstruction ≥ 75%) and AR (serum total IgE, inhalant-specific IgE, or clinical diagnosis): Group A (AH alone, n = 39), Group B (mixed factors, n = 63), Group C (AR alone, n = 53), and Group D (control, n = 22). OSA severity was assessed using the apnea-hypopnea index (AHI) measured by polysomnography. Intergroup comparisons were performed using the Kruskal-Wallis test. Spearman's correlation analysis was used to evaluate the correlation between total IgE and AHI. A multivariate linear regression model was employed to identify independent predictors of ln_AHI.
Result:
The AHI in Group B was significantly higher than that in Groups A, C, and D (P < 0.05). Total IgE showed a weak but significant positive correlation with AHI (r_s = 0.15, P = 0.042). AR was the strongest independent predictor of ln_AHI (standardized β = 0.258, 95% CI: 0.095-0.311, P < 0.0001), followed by tonsil size, BMI, adenoid size and gender, while age was not statistically significant.
Conclusion:
Among preschool children, AR is the strongest independent predictor of OSA severity, followed by the size of the adenoid and tonsil. Clinically, for preschool children with OSA, assessing allergic status should be prioritized alongside evaluation of adenotonsillar anatomy, and anti‑allergic therapy should be considered as a key component of OSA management, either as a stand‑alone treatment in mild cases or as an adjunct to adenotonsillectomy in more severe cases.
Related Concept Videos
 01:28
Asthma I: Introduction
 01:21
Sleep Apnea
The condition is more prevalent among...
 01:29
Asthma-I: Introduction
 01:17
Other Pulmonary Disorders
 01:13
Asthma III: Clinical Manifestations
 01:30
Tonsillitis I: Introduction
Etiology
Three primary contributing factors have been identified.