Related Experiment Video
Updated: Aug 6, 2026
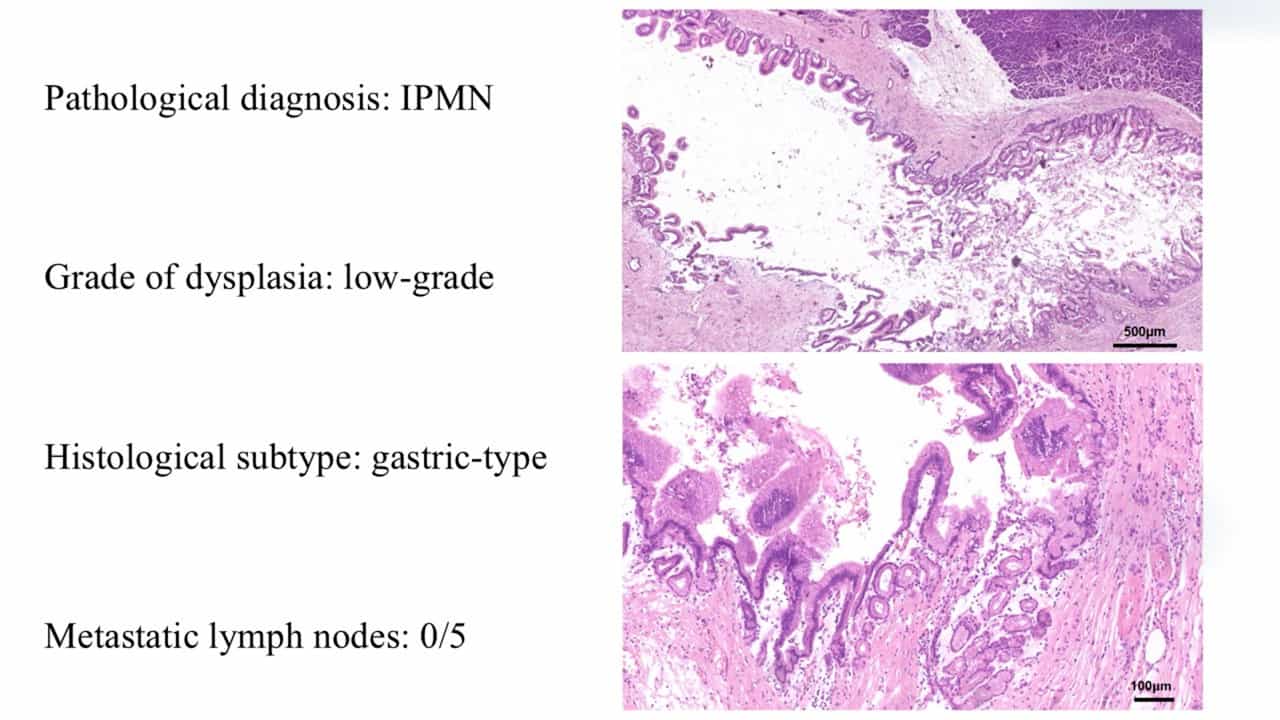

Robotic Duodenum-preserving Total Pancreatic Head Resection for Intraductal Papillary Mucinous Neoplasms
Published on: April 17, 2026
Outcomes of Post-Endoscopic Ultrasound Pancreatic Cancer Compared to Detected Pancreatic Cancer: A Multicenter Cohort
Rahul Karna1, Himsikhar Khataniar2, Omar Al Ta'ani2
1Division of Gastroenterology & Hepatology, University of Minnesota Medical Center, MN, USA.

Background And Aims:
Endoscopic ultrasound (EUS) can detect pre-malignant lesions in pancreas. Despite advances in training, EUS remains an operator dependent procedure and interval pancreatic cancer (PC) can be diagnosed after a preceding cancer-negative EUS. We aim to study outcomes of PC occurring after a EUS negative for cancer.
Methods:
We utilized the TriNetX multi-institutional database to assess patients with PC and a preceding EUS. Patients whose EUS occurred less than 6 months before PC diagnosis were categorized as detected pancreatic cancer (D-PC), while those with EUS that did not detect PC between 6 and 18 months before PC diagnosis were categorized as post EUS-pancreatic cancer (PEPC). Propensity matched cohort analysis was performed after controlling for covariates to assess surgery, chemotherapy, hospitalization and all-cause mortality.
Results:
Out of 20,828 included PC patients, 5.4% (n=1,127 ) were PEPC and 94.6% (n=19,701) were D-PC. At three years, PEPC cohort had significantly lower chemotherapy utilization (33.07% vs. 45.46%), surgery (9.53% vs 22.37%), all cause hospitalization (53.57% vs 69.70%) and all-cause mortality (27.90% vs. 33.42%) compared to D-PC. Predictors of mortality in PEPC cohort include White race (aHR 1.191), type 2 diabetes mellitus (aHR 1.144), nicotine use (aHR 1.233), location in head (aHR 1.319) and body (aHR 1.225) of pancreas.
Conclusions:
Nearly 5.4% pancreatic cancer occur after negative EUS in the previous 6-18 months. D-PC had higher chance of surgical resection and chemotherapy but also higher rates of mortality at 3-years. Further large scale studies with patient and procedure level data assessment to allow root-cause analysis is needed to determine its etiology and associated factors to limit its incidence.