Related Experiment Video
Updated: Aug 6, 2026
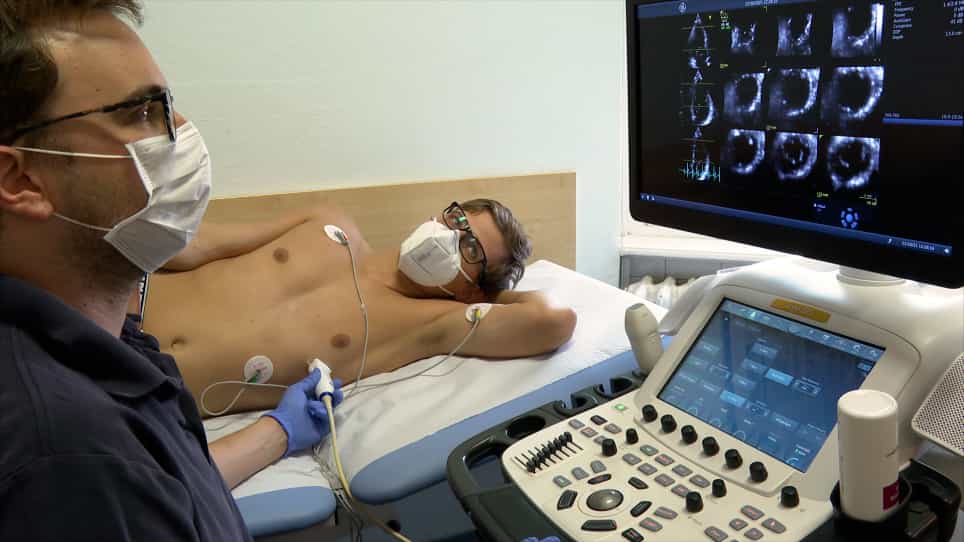

Evaluation of Left Ventricular Structure and Function using 3D Echocardiography
Published on: October 28, 2020
A Comparison of 2- and 3-Dimensional Echocardiographic Measurement of the Mitral Valve Leaflet Lengths
Madison I Goldberger1, Andrew Maslow2, Matthew Maslow3
1Department of Anesthesiology, Scarborough Health Network, Toronto, Canada.

Objectives:
Accurate echocardiographic assessment of mitral valve (MV) anatomy and function is essential for guiding therapeutic decision making in patients with mitral regurgitation. This is particularly critical for transcatheter mitral edge-to-edge repair, in which open surgical inspection is not feasible and procedural success is heavily dependent on periprocedural echocardiographic imaging. Measurements on the order of millimeters determine procedure feasibility and risk of complications. The authors hypothesized that 3-dimensional (3D) imaging with multiplanar reconstruction (MPR) would improve quantitative assessment of the MV leaflet lengths.
Design And Setting:
A retrospective analysis of patients scheduled for elective cardiac surgery with adequate transesophageal echocardiographic 2-dimensional (2D) mid-esophageal views and full-volume 3D datasets was performed at a single institution.
Participants:
Seventy-five adult patients participated in this study.
Interventions:
Two- and three-dimensional diastolic leaflet lengths of the middle segment of the anterior leaflet (A2), anterior-lateral scallop of the posterior leaflet (P1), middle scallop of the posterior leaflet (P2), and posterior-medial scallop of the posterior leaflet (P3) were measured and compared using Bland-Altman and Pearson correlation statistics. Interobserver variability was evaluated in a subset of 15 patients.
Measurements And Main Results:
Correlations between 2D and 3D imaging were moderate (r = 0.41-0.74, p < 0.0001 for all). While the mean biases (differences) between 2D and 3D measures of A2 and P2 were small (0.03 and -0.07 cm, respectively), the coefficients of variation (CoVs) ranged from 19.4% to 23.7% for A2 and from 41.4% to 44.3% for P2. The mean biases between 2D and 3D measures of P1 and P3 were 0.05 and 0.04 cm, respectively, with CoVs of 59.9% and 49.6%, respectively. Interobserver variability analysis showed that 3D MPR measures of A2 (CoV, 7.3%) and P2 (CoV, 17.3%) were significantly lower (p = 0.004 and p = 0.02, respectively) than 2D measures from the mid-esophageal 4-/5-chamber and mid-esophageal long-axis windows of A2 (20.4% and 38.2%, respectively) and P2 (43.6% and 53.6%, respectively).
Conclusions:
There were significant differences between 2D and 3D measurements of diastolic mitral leaflet lengths. While this study did not define the gold-standard measurement technique, it showed that 3D MPR with 3D feedback for precise leaflet identification of A2 and P2 resulted in improved precision based on interobserver variability and significantly lower CoV. Overall, the variability reported in this study indicates the need for well-defined standardized methods of image acquisition, image interpretation, and analysis of the MV.

Related Concept Videos
 01:23
Mitral Stenosis II: Clinical features and Diagnostic Tests
 01:27
Mitral Valve Prolapse I: Introduction
 01:25
Mitral Regurgitation III: Medical Management
 01:23
Mitral Regurgitation II: Clinical Features and Diagnostic Tests