Related Experiment Video
Updated: Aug 6, 2026
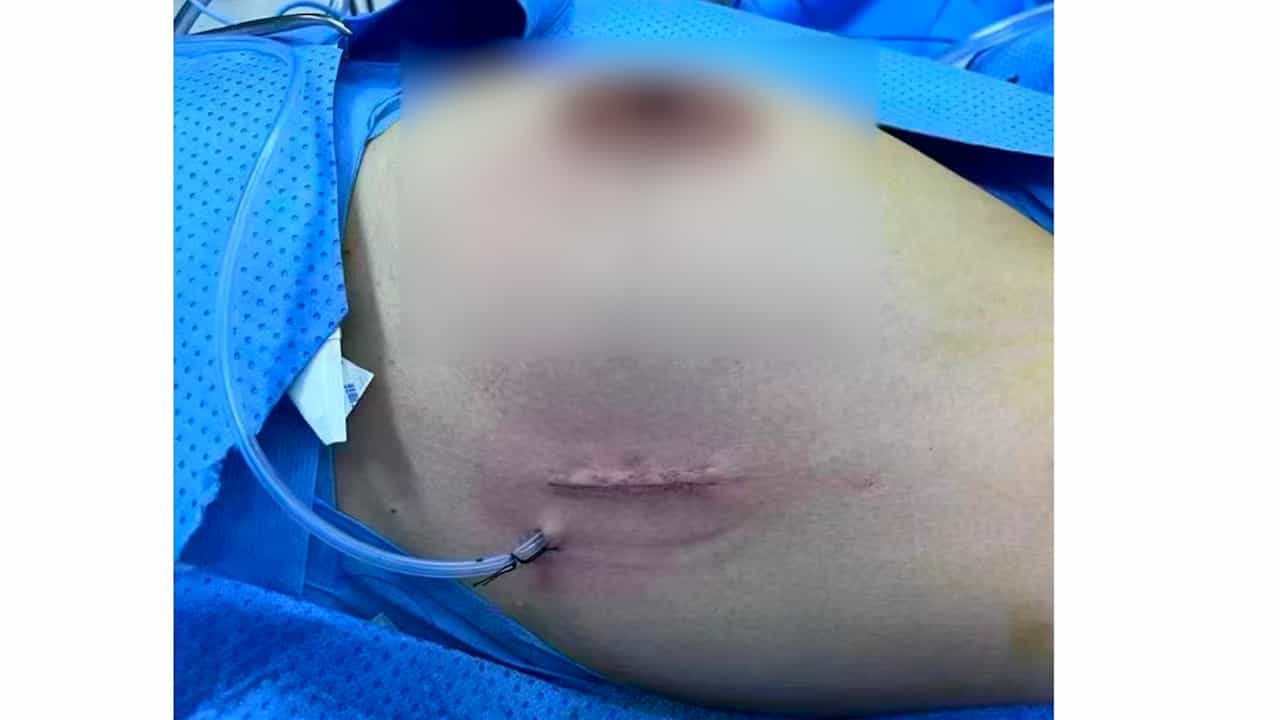

Single-port Non-liposuction Endoscopic Axillary Lymph Node Dissection in Breast Cancer Surgery
Published on: April 3, 2026
Tumors >2 cm in node-negative, HER2-positive breast cancer: comparing neoadjuvant dual-targeted versus adjuvant
Xiaoduo Li1, Kexuan Feng1, Junjie Liu1
1Department of Breast Surgery, The First Affiliated Hospital of Xi'an Jiaotong University, Xi'an, China.

Background:
The optimal systemic treatment for node-negative, human epidermal growth factor receptor 2 (HER2)-positive breast cancer with tumors >2 cm remains unclear. De-escalation is commonly used for smaller tumors, but evidence supporting the neoadjuvant dual-targeted pathway in high tumor burden disease is limited.
Objectives:
To compare pathological response and exploratory disease-free survival (DFS) between the neoadjuvant dual-targeted and adjuvant single-targeted treatment pathways, focusing on tumors >2 cm.
Design:
Retrospective, single-center cohort study.
Methods:
We identified 518 consecutive patients treated from 2015 to 2023 at a tertiary academic center. In a guideline-recommended cohort (N = 426), patients managed via the neoadjuvant dual-targeted pathway were compared with those managed via the adjuvant single-targeted pathway. Propensity scores were estimated using logistic regression and applied via overlap weighting to balance covariates. DFS was assessed using overlap-weighted Cox regression, including a tumor-size interaction (⩽2 vs >2 cm). Sensitivity analyses addressed calendar-time confounding, truncation at 24 months with bootstrapped risk differences, and surgery-date landmark analysis. Reporting followed Strengthening the Reporting of Observational Studies in Epidemiology guidelines.
Results:
Overlap weighting achieved good balance (all standardized mean differences <0.10). In the guideline-recommended cohort (18 DFS events), the neoadjuvant dual-targeted pathway was not significantly associated with DFS (hazard ratio (HR) 0.26; 95% confidence interval (CI): 0.04-1.55; p = 0.138), and the size-by-treatment interaction was not significant (p = 0.123). In tumors >2 cm (N = 247), the neoadjuvant dual-targeted pathway was associated with a pathological complete response rate of 56.9% (58/102) and an exploratory DFS signal (HR 0.08; 95% CI: 0.01-0.59). At 24 months, 0 versus 5 DFS events resulted in an absolute risk difference of 7.0% (95% CI: 1.1%-14.0%). Sensitivity analyses yielded consistent results, though estimates for tumors ⩽2 cm were imprecise.
Conclusion:
In this exploratory real-world cohort, the neoadjuvant dual-targeted treatment pathway for node-negative, HER2-positive breast cancer with tumors >2 cm was associated with high pathological response rates and an exploratory DFS signal, though sparse events and observational biases limit survival conclusions. Size-informed, risk-adapted strategies are needed. Trial registration: Not applicable.
