Related Experiment Video
Updated: Aug 6, 2026
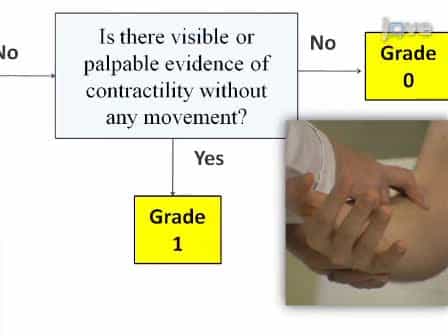

Manual Muscle Testing: A Method of Measuring Extremity Muscle Strength Applied to Critically Ill Patients
Published on: April 12, 2011
Evaluation of respiratory status in patients with myopathy
Behnaz Ansari1, Somayeh Sadeghi2, Narges Sobhan3
1Department of Neurology, School of Medicine, Neurosciences Research Center, Al-Zahra Hospital, Isfahan University of Medical Sciences, Isfahan, Iran.

Abstract:
Myopathic diseases can lead to significant respiratory disorders due to the involvement of skeletal muscles, including respiratory muscles. These disorders not only affect the quality of life of patients, but are also one of the main causes of mortality in this group. This study aimed to evaluate pulmonary function and its associated factors in patients with myopathy. This is a prospective cross-sectional study that was performed in 2020-2021 on 44 patients with myopathy. The participant's demographic information and features of disease, including age, sex, type of disease, age of onset and duration of disease, and mobility status of the patient (using Walker or wheelchair) were collected by a checklist. The slow inspiratory vital capacity (VC) and FEV1 were obtained. Data analysis was performed with SPSS version 24 software using t-test, Mann-Whitney, Pearson, and Spearman correlation tests. The sitting and lying FVC were significantly higher in patients who had no drug usage (P = 0.007 and P = 0.005, respectively), no sputum (0.003 and 0.002, respectively), no dysphagia (P = 0.002 and P = 0.001, respectively), and no coughs while eating (P = 0.022 and P = 0.006). There were significant inverse relationships between age and sitting FVC (r = -0.638) and lying FVC (r = -0.497), and age had a significant direct relationship with changes in the FVC (r = 0.652) (P < 0.001 for all). Furthermore, we observed a significantly inverse relationship between age of disease onset and sitting FVC (r = -0.491, P = 0.001) and significantly direct relationship between age of disease onset and lying FVC (r = 0.447, P = 0.002) and FVC changes (r = 0.371, P = 0.013). Assessments of respiratory functions, especially through spirometry in both sitting and supine positions, and attention to clinical symptoms such as dysphagia and cough, are of great clinical importance in the management of myopathy patients. These assessments can help in the early diagnosis of respiratory failure and timely interventions.
More Related Videos
 09:37
Evaluation of Respiratory Muscle Activation Using Respiratory Motor Control Assessment (RMCA) in Individuals with Chronic Spinal Cord Injury
Published on: July 19, 2013
 09:24
Repeated Measurement of Respiratory Muscle Activity and Ventilation in Mouse Models of Neuromuscular Disease
Published on: April 17, 2017
Related Concept Videos
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration can...
 01:23
Assessment of Respiration
Subjective Assessment: Nurses interview the patient to gather information directly during the subjective assessment. It includes questions about the individual's medical history, medications, and symptoms, focusing on past respiratory conditions like asthma or COPD,...
 01:15
Myasthenia Gravis: Diagnostic Tests
The edrophonium test is a diagnostic tool for myasthenia gravis. It involves...
 01:30
Respiratory System Abnormal Finding I: Inspection and Percussion
Inspection Findings
During an inspection, several findings may suggest the presence of respiratory distress or disease. Pursed-lip breathing, where exhalation is slowed by...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement: