Related Experiment Video
Updated: Aug 6, 2026
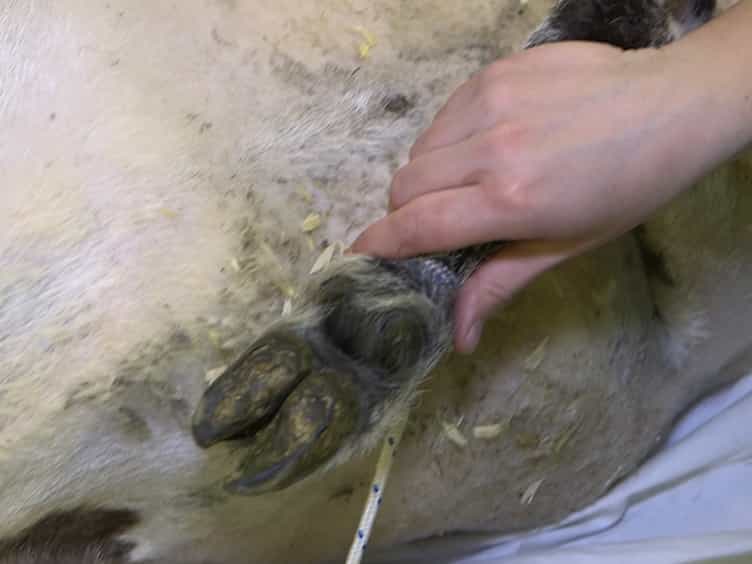

Transvaginal Mesh Insertion in the Ovine Model
Published on: July 27, 2017
From implant to explant: urinary morbidity in women undergoing mesh removal
Z Zainal Bahren1, C Haudebert2, E Fong3
1Taranaki Base Hospital, New Plymouth, New Zealand. zzai007@aucklanduni.ac.nz.

Background:
Pelvic mesh implants are commonly used in female urology for the treatment of stress urinary incontinence and pelvic organ prolapse. However complications can be substantial and a number of the patients in this cohort proceed to mesh explantation. We evaluated urinary morbidity after pelvic mesh removal within New Zealand's National Mesh Service.
Methods:
Retrospective review of women undergoing pelvic mesh removal between March 2009 and December 2024 by the National Mesh Service. Primary outcomes were patient-reported urinary symptoms using validated instruments: Pelvic Floor Distress Inventory [PFDI] and International Consultation on Incontinence Questionnaire-Short Form [ICIQ-SF]. Secondary outcomes included clinician-reported symptoms at last follow-up, reintervention for incontinence, and complications (Clavien-Dindo).
Results:
Of 345 patients (median age 58 years; median 105.3 months from insertion to removal), pain was the commonest indication for explantation, followed by bladder outlet obstruction/lower urinary tract symptoms. Among 184 with urodynamics, 32% met criteria for likely/definite outlet obstruction. Robotic assistance was used in 97 cases. Eight patients (2.3%) developed Grade III complications. Mean follow-up was 27.2 months. Post-removal, clinician-reported persistence of SUI, pain, and overactive bladder was seen in 30-40%, dyspareunia in 20%, recurrent urinary tract infection in 9%, and obstructive voiding in 12%. Overall, 25% needed concurrent procedure during pelvic mesh removal and 48% required ≥ 1 subsequent incontinence procedure. 6 patients ultimately underwent cystectomy. In 83 patients with paired PFDI, mean total scores improved from 168.4 to 149.6 (p < 0.05) with concordant subscale improvements. ICIQ-SF severity categories showed minimal overall shift.
Conclusions:
Urinary morbidity after pelvic mesh removal is common and frequently persists despite explantation, with high reintervention rates indicating chronicity. Findings support robust pre-operative counselling, multidisciplinary care, and prospective studies to define predictors and optimise surgical pathways.

