Extended Forehead Flap With Lowered Pivot Point
Related Experiment Video
Updated: Aug 6, 2026
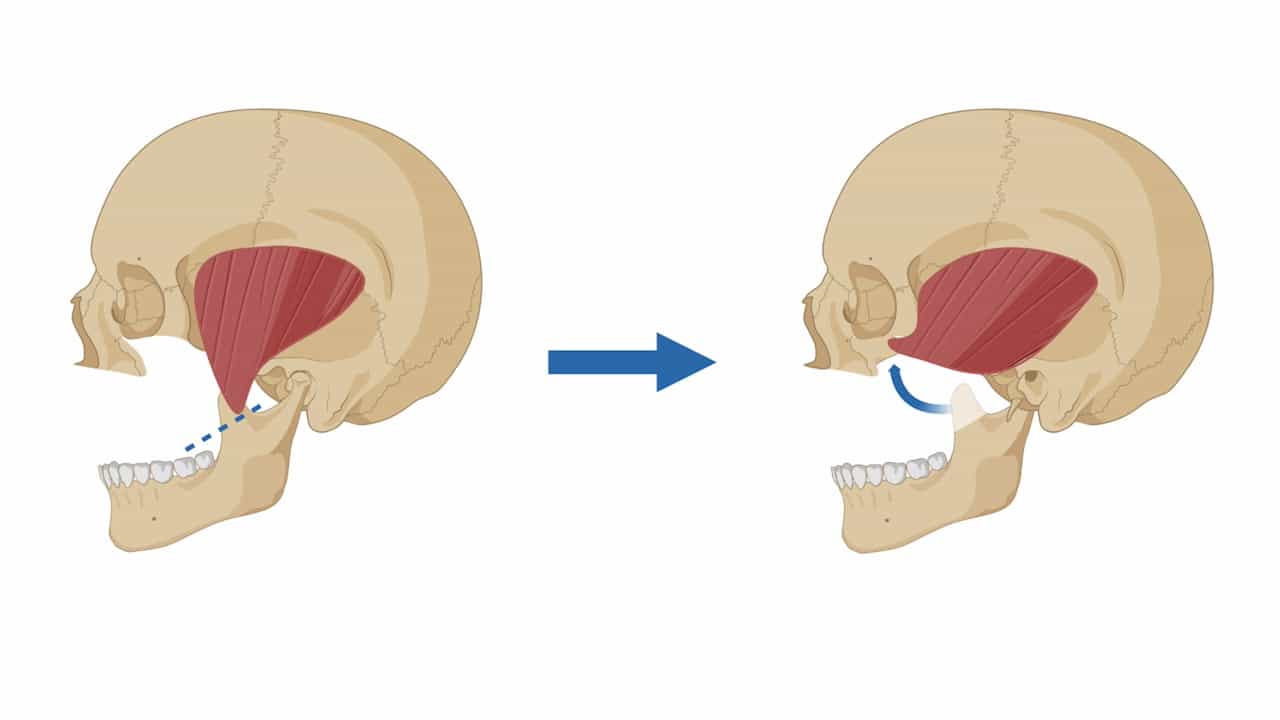
Coronoid-Temporalis Pedicled Flap for Orbital Floor Defect Reconstruction
Published on: December 5, 2025
Ho Hyung Lee1, An Gyu Jung1, Matias Cancino Abarca2
1Department of Plastic and Reconstructive Surgery, University of Ulsan College of Medicine, Asan Medical Center, Seoul, Korea.

Background:
When the paramedian forehead flap pivot is positioned at or just above the eyebrow, extensive defects may require cephalic extension toward the hairline, increasing donor-site scar burden. We evaluated whether inferior translation of the pivot below the medial eyebrow provides measurable geometric benefit without increasing complications.
Methods:
A single-surgeon retrospective review was performed of consecutive patients undergoing multi-subunit nasal reconstruction with a supratrochlear-based paramedian forehead flap (December 2016 to August 2023). Patients were grouped into a conventional cohort (pivot at or just above the eyebrow without brow transection) and a lowered-pivot cohort (pivot lowered to the midpoint between the eyebrow and medial canthus). Standardized photographs were analyzed using scale-free ratios to calculate shortening fraction (SF=c/a) and proportional forehead-scar reduction [2c/(B-A)]. Complications were compared between techniques; within the lowered-pivot cohort, exploratory analyses assessed associations between SF and complications.
Results:
Thirty patients met the inclusion criteria (conventional, n=16; lowered pivot, n=14). In the lowered-pivot cohort, mean SF was 0.156±0.025 and mean proportional forehead-scar reduction was 0.432±0.106 [2c/(B-A)]. Complication rates did not differ significantly between groups, including unintended hair-bearing transfer (43.8% vs. 28.6%, P =0.466), partial distal necrosis (6.3% vs. 7.1%, P =1.000), and donor-site scarring (62.5% vs. 35.7%, P =0.272) in the conventional versus lowered-pivot cohorts, respectively. Within the lowered-pivot cohort, SF was not associated with hair-bearing transfer ( P =0.354), partial distal necrosis ( P =0.532), or donor-site scarring ( P =0.638) on exploratory analysis.
Conclusions:
Notably, lowering the pivot point by a given distance reduces the required cephalic donor incision by approximately twice that distance in the proposed geometric model, representing a substantial reduction in donor-site scar burden. Inferior translation of the pivot below the eyebrow provides measurable geometric benefit while maintaining a similar complication profile in this cohort. This modification may be useful when additional reach is needed, and tissue expansion is not planned.
