Related Experiment Video
Updated: Aug 6, 2026
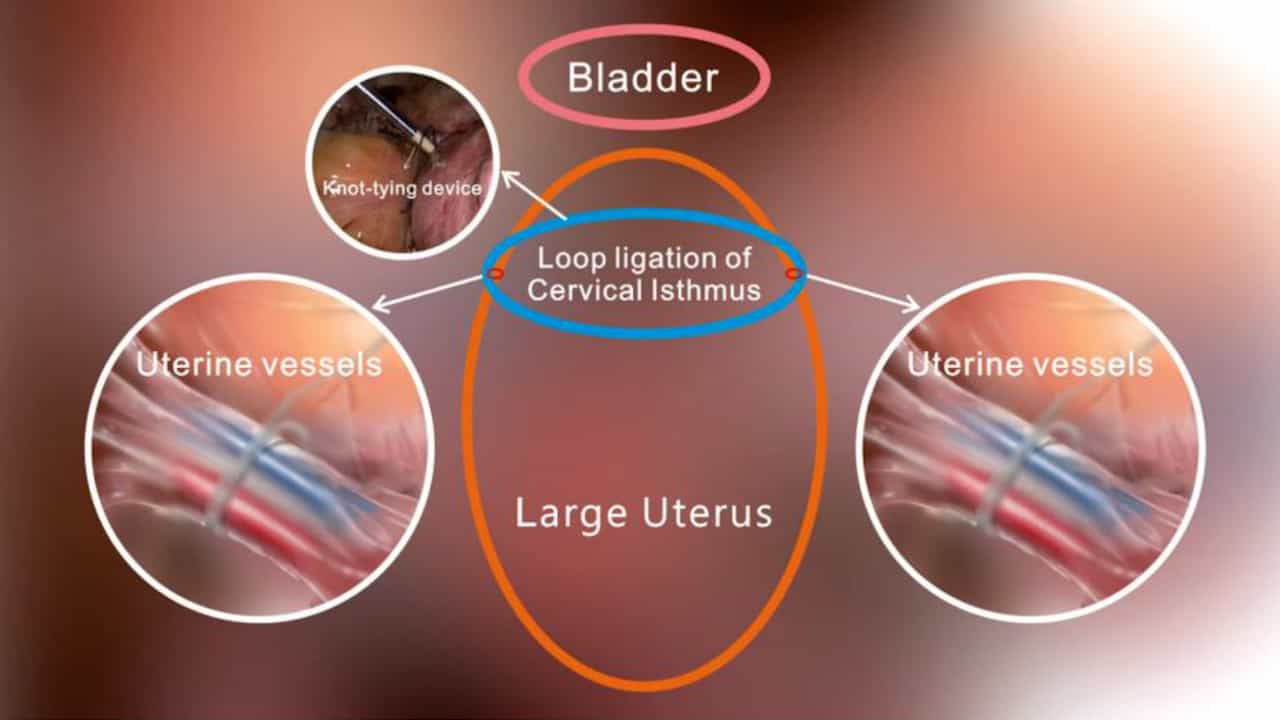

Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
Closing the Gap: A Decade of Integrating Minimally Invasive Hysterectomy in an Urban Safety-Net Hospital
Natalie Cohen1, Emily Lin1, Katherine Smith1
1University of Texas Southwestern (Drs. Cohen, Lin, Smith, Latham, McIntire), Dallas, Texas.

Study Objective:
To evaluate how the 10-year integration of minimally invasive hysterectomy (MIH) at a safety-net hospital impacted surgical approach, perioperative outcomes, and equity of MIH access across racial groups in an underserved patient population.
Design:
Observational-retrospective chart review.
Setting:
A single, university-affiliated urban safety-net hospital. The institution serves as a primary teaching site for one of the largest Obstetrics and Gynecology residency programs in the United States and provides care to a predominantly underinsured patient population.
Patients Or Participants:
A total of 3004 patients undergoing hysterectomy for benign indications between 2010 and 2020.
Interventions:
Implementation of minimally invasive surgical practices as well as the establishment of a Complex Benign Gynecology fellowship program at an urban safety-net hospital.
Measurements And Primary Results:
Over the 10-year implementation period, the proportion of laparoscopic hysterectomies increased from 9% to 46% (p < .05), while abdominal hysterectomies decreased from 68% to 27% (p < .05). In this time, the proportion of perioperative complications (Clavien-Dindo grades 1 and 2) decreased from 45.4% in 2010 to 26.8% in 2020 (p < .05). Grade 3 and 4 complications were consistently rare (<3%). Operating times did not significantly change over time; however, the median blood loss per surgery decreased from 300 to 200 mL, and the median hospital stay was reduced by 50%, from 61 to 30 hours (p < .001). The transition to MIH was associated with significantly increased diagnoses of adenomyosis and endometriosis (p < 0.001).
Conclusion:
The systematic implementation of MIH in a safety-net setting is feasible and effective, associated with a decrease in complication rates and hospital stays. The shift to minimally invasive techniques additionally improved the diagnoses of endometriosis and adenomyosis, which are often associated with significant diagnostic delays. These findings demonstrate that increased access to minimally invasive surgery is essential to quality care in safety-net populations.
More Related Videos
 05:46
Introduction of Intracapsular Rotary-cut Procedures (IRCP): A Modified Hysteromyomectomy Procedures Facilitating Fertility Preservation
Published on: January 17, 2019
 07:48
Intraoperative Video Consultation Following Bile Duct Transection Facilitates Direct OR Transfer for Robotic Hepaticojejunostomy at Tertiary Center
Published on: January 9, 2026