Related Experiment Video
Updated: Aug 5, 2026
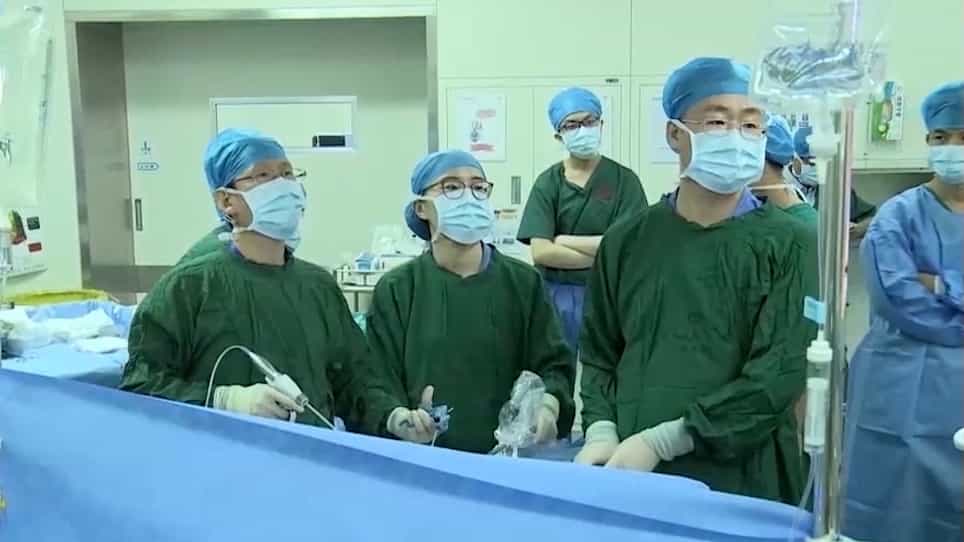

Laparoscopy-endoscopy Cooperative Surgery for the Treatment of Gastric Gastrointestinal Stromal Tumors
Published on: February 19, 2022
Extrauterine Low-Grade Endometrial Stromal Sarcoma: A Case Report and Review of the Literature
Jie-Yu Li1, Chiu-Hsuan Cheng2,3, Dah-Ching Ding1,4
1Department of Obstetrics and Gynecology, Hualien Tzu Chi Hospital, Buddhist Tzu Chi Medical Foundation, Tzu Chi University, Hualien 970, Taiwan.

Abstract:
Background and Clinical Significance: The primary occurrence of low-grade endometrial stromal sarcoma (LG-ESS) at extrauterine sites, termed extrauterine ESS (EESS), is exceedingly rare. Case Presentation: A 49-year-old female, gravida 2 para 2 (all deliveries by cesarean section), presented with a 1-month history of epigastric and left upper quadrant abdominal pain. Abdominal computed tomography revealed a lobulated mass, measuring 4.6 cm, in the left upper quadrant with focal attachment to the splenic flexure of the colon. She underwent a laparoscopic partial gastrectomy and colectomy at a referral institution. Surgical pathology identified a 6.0 × 5.0 × 4.0 cm lobulated tumor involving the stomach with colonic invasion, diagnosed as LG-ESS (pT3N0). Immunohistochemistry showed a CD10-reactive lesion. The patient was referred to our institution for definitive gynecological surgery. After prophylactic ureteral double-J catheter insertion, she underwent laparoendoscopic single-site (LESS) total hysterectomy with bilateral salpingo-oophorectomy. The final histopathological examination of the hysterectomy specimen revealed intramural leiomyomas and benign ovarian cysts, with no evidence of ESS within the uterine corpus or adnexa. These findings confirmed a true primary EESS of nonuterine origin, consistent with AJCC stage 3 disease. The patient recovered uneventfully and was discharged during outpatient follow-up. Conclusions: This case represents one of the very few reported instances of primary LG-EESS involving the stomach and colon, simultaneously managed with a staged multidisciplinary surgical approach, including gastrointestinal resection followed by LESS hysterectomy and bilateral salpingo-oophorectomy.
