Related Experiment Videos
An Enigmatic Case of Rectal Bleeding in a Young Woman-A Forgotten Intrauterine Device, Perforation and Rectal
Libby Or Madar1,2, Ariel Polonsky1,2, Ilan Bruchim1,2
1Department of Obstetrics and Gynecology, Hillel Yaffe Medical Center, Hadera 3820302, Israel.

Background: Perforation associated with intrauterine devices (IUDs) occurs in approximately 1 in 1000 insertions and may be either partial or complete. Perforation may be primary, occurring during device insertion, or secondary, developing after the device has remained in situ for more than eight weeks. Typical symptoms of IUD perforation include chronic pain and intestinal obstruction. Rarely, the device is found either completely within the rectal lumen or partially embedded in the rectal wall with partial intraluminal extension. Removal of the device may require colonoscopy, laparoscopy, or a combination of both. Case: A 45-year-old woman was referred for evaluation of intermittent rectal bleeding. Initial outpatient evaluation included contrast-enhanced computed tomography (CT), which demonstrated two intrauterine devices: one appropriately positioned within the uterine cavity and another located within the rectouterine pouch. A multidisciplinary discussion involving gastroenterologists, gynecologists, and colorectal surgeons was subsequently conducted. Under general anesthesia, laparoscopy was initiated. Upon entering the abdominal cavity, a free IUD string was visualized embedded within the pelvic peritoneum. Using simultaneous colonoscopic guidance with transillumination, a targeted peritoneal incision was made overlying the IUD. The arms were removed laparoscopically. Subsequent colonoscopy removed the remaining segment of the IUD traversing the rectal wall. Conclusions: Although uterine perforation and migration of intrauterine devices are uncommon, they may result in severe and potentially life-threatening complications. Early diagnosis, careful documentation, routine follow-up, and timely removal of misplaced devices remain essential to minimizing morbidity and preventing adverse outcomes.
Background: Perforation associated with intrauterine devices (IUDs) occurs in approximately 1 in 1000 insertions and may be either partial or complete. Perforation may be primary, occurring during device insertion, or secondary, developing after the device has remained in situ for more than eight weeks. Typical symptoms of IUD perforation include chronic pain and intestinal obstruction. Rarely, the device is found either completely within the rectal lumen or partially embedded in the rectal wall with partial intraluminal extension. Removal of the device may require colonoscopy, laparoscopy, or a combination of both. Case: A 45-year-old woman was referred for evaluation of intermittent rectal bleeding. Initial outpatient evaluation included contrast-enhanced computed tomography (CT), which demonstrated two intrauterine devices: one appropriately positioned within the uterine cavity and another located within the rectouterine pouch. A multidisciplinary discussion involving gastroenterologists, gynecologists, and colorectal surgeons was subsequently conducted. Under general anesthesia, laparoscopy was initiated. Upon entering the abdominal cavity, a free IUD string was visualized embedded within the pelvic peritoneum. Using simultaneous colonoscopic guidance with transillumination, a targeted peritoneal incision was made overlying the IUD. The arms were removed laparoscopically. Subsequent colonoscopy removed the remaining segment of the IUD traversing the rectal wall. Conclusions: Although uterine perforation and migration of intrauterine devices are uncommon, they may result in severe and potentially life-threatening complications. Early diagnosis, careful documentation, routine follow-up, and timely removal of misplaced devices remain essential to minimizing morbidity and preventing adverse outcomes.
Related Concept Videos
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus.
 01:22
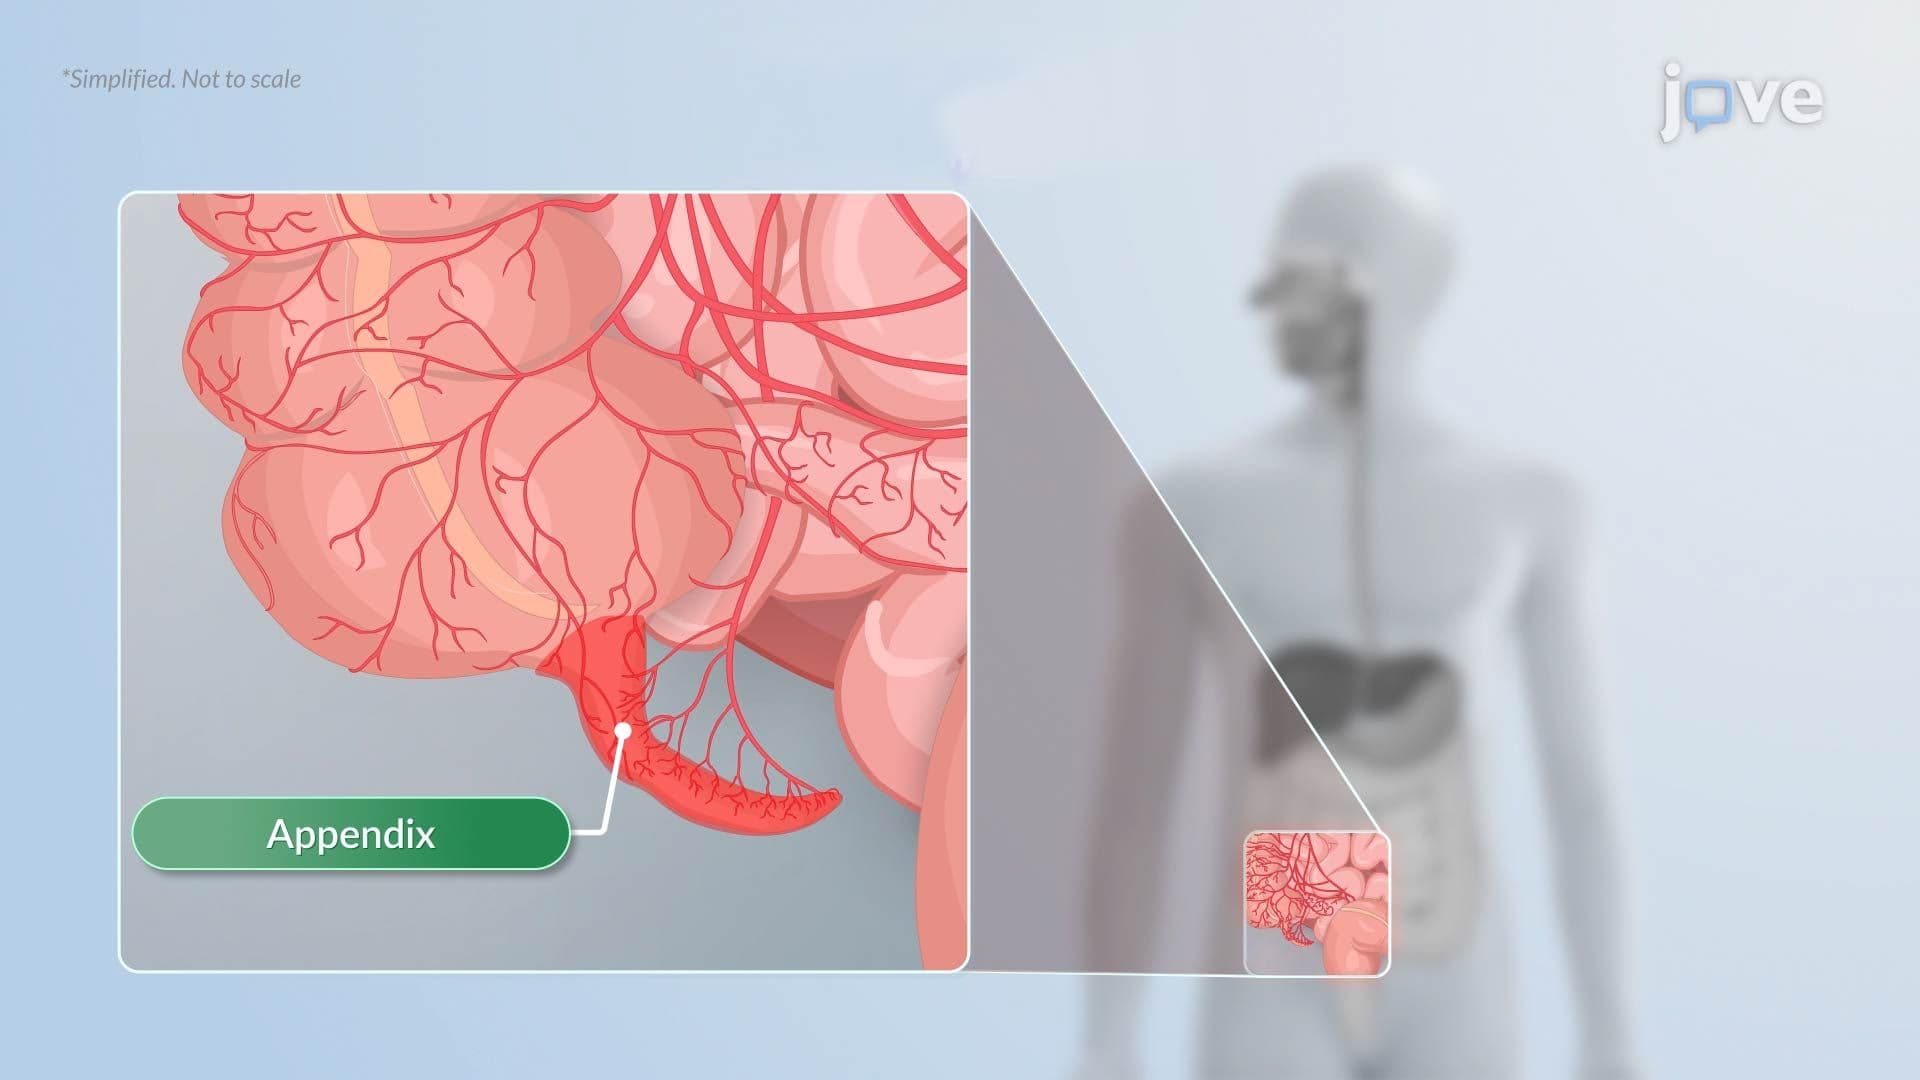
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...
 01:25
Assessment of the Rectum and Anus
Rectal Inspection
Begin by inspecting the perianal and anal areas for color, texture, rashes,...
 01:29
Intestinal Obstruction I: Introduction
 01:19
Appendicitis