Related Experiment Video
Updated: Aug 5, 2026
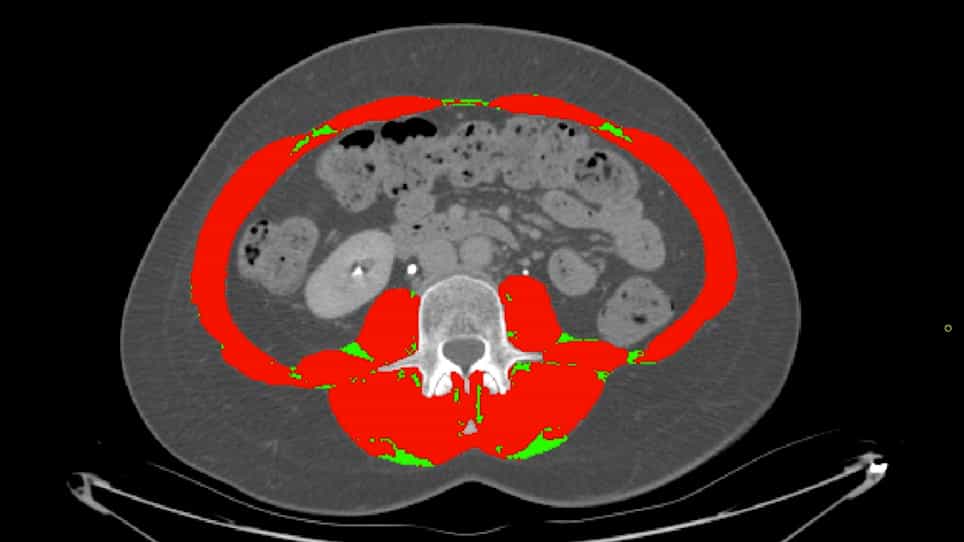

Segmentation and Linear Measurement for Body Composition Analysis using Slice-O-Matic and Horos
Published on: March 21, 2021
A clinical prediction model for low psoas muscle radiodensity in adults with severe obesity: development and internal
Eunhye Seo1, Mi Kyung Kim2, Suh Youngsung3
1Department of Nursing, College of Nursing, Keimyung University, Daegu, Republic of Korea.

Introduction:
Low psoas muscle radiodensity (PMD) on computed tomography (CT) indicates impaired muscle quality and is widely used as an operational marker of myosteatosis in individuals with obesity. In this study, we aimed to develop and internally validate a clinically accessible prediction model for low PMD in adults with severe obesity.
Methods:
This retrospective study included 150 adults with severe obesity, defined as body mass index (BMI) ≥ 35 kg/m2, who underwent CT evaluation as candidates for metabolic and bariatric surgery at our university hospital between January 2019 and May 2025. PMD was quantified on CT, and low PMD was defined as the lowest quartile [cutoff: ≤40.8 Hounsfield units (HU)]. A prediction model incorporating age, BMI, serum albumin, and bioelectrical impedance analysis-derived phase angle (PhA) was developed. Model performance was assessed using discrimination and accuracy metrics, with internal validation by bootstrapping.
Results:
The mean age, BMI, and PMD were 37.0 ± 10.6 years, 40.30 ± 8.05 kg/m2, and 45.90 ± 8.76 HU, respectively. PhA provided incremental explanatory value for PMD (ΔR 2 = 0.048, p = 0.001). In multivariable logistic regression analysis, age and BMI were independently associated with low PMD, whereas albumin and PhA were not significantly associated with low PMD; however, their incremental contribution was assessed based on predictive performance. The integrated model demonstrated improved discrimination compared with the age-BMI model [area under the curve (AUC) = 0.841 vs. 0.829]. At an optimal cutoff of 0.38, the sensitivity was 67.5%, specificity was 85.5%, and optimism-corrected AUC was 0.821.
Discussion:
This clinically accessible model demonstrated good discrimination and high specificity, supporting clinical risk stratification in settings where CT is limited.