Related Experiment Video
Updated: Aug 5, 2026
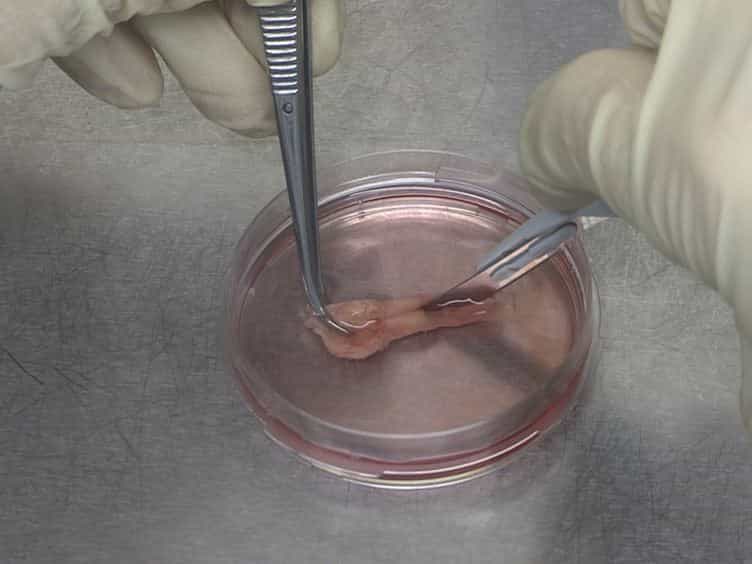
A Human Ex Vivo Atherosclerotic Plaque Model to Study Lesion Biology
Published on: May 6, 2014
Understanding intraplaque hemorrhage: From pathogenesis to clinical impact in atherosclerosis
Atsushi Sakamoto1, Sho Torii2, Hiroyoshi Mori3
1Division of Cardiology, Internal Medicine III, Hamamatsu University School of Medicine, Shizuoka, Japan; CVPath Institute, Gaithersburg, MD, USA.

Atherosclerotic cardiovascular disease remains the leading cause of morbidity and mortality worldwide. Accumulating pathological evidence indicates that rapid plaque progression is driven not only by recurrent subclinical plaque rupture with healing but also by intraplaque hemorrhage (IPH), which can occur independently of overt luminal thrombosis. IPH is no longer regarded as a passive process that merely enlarges plaque volume through deposition of erythrocyte-derived lipids, hemoglobin, and iron. Instead, contemporary pathological studies have revealed that IPH initiates a cascade of molecular and cellular responses that actively promote plaque destabilization. Within hemorrhagic plaques, erythrocyte lysis generates oxidative stress and cholesterol crystallization, accelerating necrotic core expansion and inflammatory signaling. In parallel, hemoglobin-haptoglobin complex uptake by CD163+ macrophages induces a distinct macrophage phenotype characterized by vascular endothelial growth factor and pro-inflammatory cytokines secretion, increased microvascular permeability, and propagation of intraplaque angiogenesis. These macrophage-driven processes amplify endothelial dysfunction, promote proapoptotic endothelial-to-mesenchymal transition, impair fibrous-cap integrity, and paradoxically suppress stabilizing calcification, thereby creating a microenvironment highly susceptible to rupture. Importantly, these IPH-driven cellular responses do not act in isolation but converge to amplify plaque vulnerability through interconnected inflammatory, angiogenic, and structural pathways. Advances in vascular imaging have enabled in vivo detection of IPH-related plaque features, providing a translational bridge between pathological observations and clinical phenotyping. Across carotid and coronary arterial beds, imaging-detected IPH consistently correlates with accelerated lesion progression and adverse cardiovascular outcomes. Together, current evidence positions IPH as a central biological driver of plaque progression and destabilization rather than a secondary epiphenomenon. A deeper understanding of IPH-related cellular mechanisms may identify novel therapeutic targets beyond lipid lowering and improve identification of patients with intrinsically unstable atherosclerotic disease.
Atherosclerotic cardiovascular disease remains the leading cause of morbidity and mortality worldwide. Accumulating pathological evidence indicates that rapid plaque progression is driven not only by recurrent subclinical plaque rupture with healing but also by intraplaque hemorrhage (IPH), which can occur independently of overt luminal thrombosis. IPH is no longer regarded as a passive process that merely enlarges plaque volume through deposition of erythrocyte-derived lipids, hemoglobin, and iron. Instead, contemporary pathological studies have revealed that IPH initiates a cascade of molecular and cellular responses that actively promote plaque destabilization. Within hemorrhagic plaques, erythrocyte lysis generates oxidative stress and cholesterol crystallization, accelerating necrotic core expansion and inflammatory signaling. In parallel, hemoglobin-haptoglobin complex uptake by CD163+ macrophages induces a distinct macrophage phenotype characterized by vascular endothelial growth factor and pro-inflammatory cytokines secretion, increased microvascular permeability, and propagation of intraplaque angiogenesis. These macrophage-driven processes amplify endothelial dysfunction, promote proapoptotic endothelial-to-mesenchymal transition, impair fibrous-cap integrity, and paradoxically suppress stabilizing calcification, thereby creating a microenvironment highly susceptible to rupture. Importantly, these IPH-driven cellular responses do not act in isolation but converge to amplify plaque vulnerability through interconnected inflammatory, angiogenic, and structural pathways. Advances in vascular imaging have enabled in vivo detection of IPH-related plaque features, providing a translational bridge between pathological observations and clinical phenotyping. Across carotid and coronary arterial beds, imaging-detected IPH consistently correlates with accelerated lesion progression and adverse cardiovascular outcomes. Together, current evidence positions IPH as a central biological driver of plaque progression and destabilization rather than a secondary epiphenomenon. A deeper understanding of IPH-related cellular mechanisms may identify novel therapeutic targets beyond lipid lowering and improve identification of patients with intrinsically unstable atherosclerotic disease.

Related Concept Videos
 01:30
Atherosclerosis I: Introduction
 01:26
Coronary Artery Disease II: Pathophysiology
 01:29
Hemorrhagic Stroke ll: Pathophysiology
 01:17
Hemorrhagic Stroke l: Introduction
 01:30
Peripheral Artery Disease I: Introduction
 01:15
Ischemic Stroke ll: Pathophysiology