Related Experiment Video
Updated: Aug 5, 2026
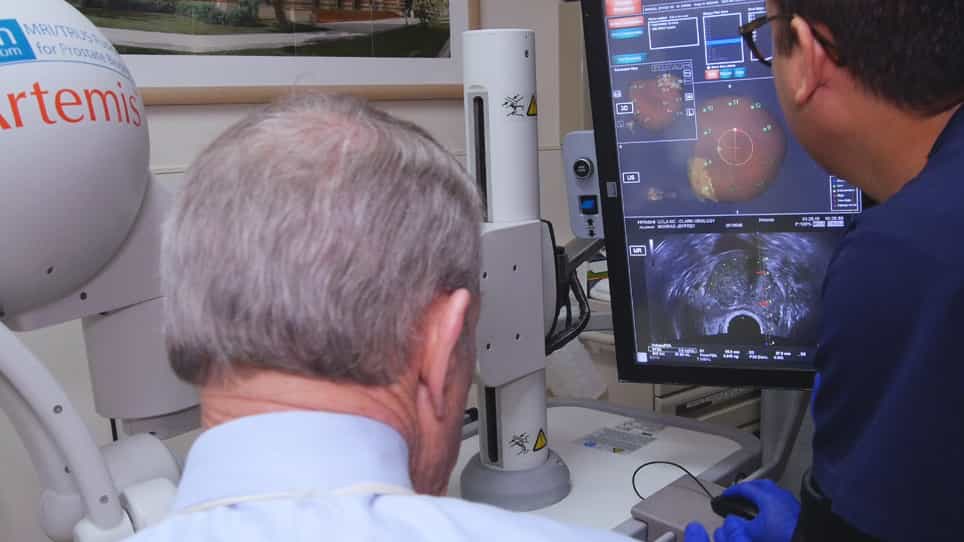

Use of MRI-ultrasound Fusion to Achieve Targeted Prostate Biopsy
Published on: April 9, 2019
Risk-adapted Omission of Systematic Cores in PI-RADS 3 Lesions Based on Prostate-specific Antigen Density, Biopsy
Bogdan Adrian Buhas1, Georges Mjaess2, Romain Diamand2
1Department of Urology, Groupe Hospitalier Diaconesses Croix Saint-Simon, Paris, France.

Background:
Prostate Imaging Reporting and Data System (PI-RADS) category 3 lesions represent an intermediate-risk group for which the additional diagnostic value of systematic biopsy (SBx) after multiparametric magnetic resonance imaging (mpMRI)-targeted biopsy (TBx) remains uncertain.
Objective:
To quantify the absolute omission cost of a TBx-only strategy compared with overall biopsy (OBx; TBx plus SBx) and to assess whether this cost varies according to prostate-specific antigen density (PSAD), biopsy route, and targeted sampling intensity.
Design, Setting, And Participants:
This retrospective multicentre cohort study included 902 men with exclusively PI-RADS 3 lesions on prebiopsy mpMRI who underwent index software-assisted mpMRI-ultrasound fusion biopsy at six academic and high-volume centres between January 2016 and March 2023.
Intervention:
All patients underwent same-session TBx and SBx via either the transperineal (TP) or transrectal (TR) route.
Outcome Measurements And Statistical Analysis:
The primary outcome was the absolute cohort-level proportion of clinically significant prostate cancer (csPCa), defined as International Society of Urological Pathology (ISUP) grade group ≥2, detected by OBx but missed by TBx. Paired detection rates were compared using the McNemar test, and the omission cost was estimated with exact confidence intervals (CIs). An exploratory 5% margin was used to contextualise the performance of TBx alone. Factors associated with TBx failure were evaluated using multivariable Firth penalised logistic regression. A sensitivity analysis defined csPCa as ISUP grade group ≥3.
Results And Limitations:
TBx detected csPCa in 181 of 902 men (20%), whereas OBx detected csPCa in 240 (27%). TBx alone missed 59 cases, corresponding to an absolute omission cost of 6.5% (95% CI 5.0-8.4), which exceeded the prespecified exploratory 5% benchmark. When csPCa was defined as ISUP grade group ≥3, the omission cost decreased to 2.8% (25/902; 95% CI 1.8-4.1). The lowest omission cost was observed among men undergoing TP biopsy with PSAD <0.10 ng/ml/cm3 (0.8%, 1/126; 95% CI 0.02-4.3). Each additional targeted core was independently associated with lower odds of TBx failure (adjusted odds ratio 0.69, 95% CI 0.54-0.86). Limitations include the retrospective design, centre-level heterogeneity in mpMRI interpretation and biopsy practices, nonrandom biopsy-route selection, the use of same-session combined biopsy rather than whole-mount pathology as the reference standard, and the absence of core-by-core spatial mapping.
Conclusions:
TBx alone should not be considered a universal substitute for OBx in men with PI-RADS 3 lesions when csPCa is defined as ISUP grade group ≥2. The lower omission cost observed when a stricter threshold for significant disease was applied, and in selected men with low PSAD undergoing TP biopsy, supports prospective evaluation of risk-adapted biopsy deintensification. However, these exploratory findings do not justify the routine omission of SBx.

