Related Experiment Video
Updated: Aug 5, 2026

Deep Neuromuscular Blockade Leads to a Larger Intraabdominal Volume During Laparoscopy
Published on: June 25, 2013
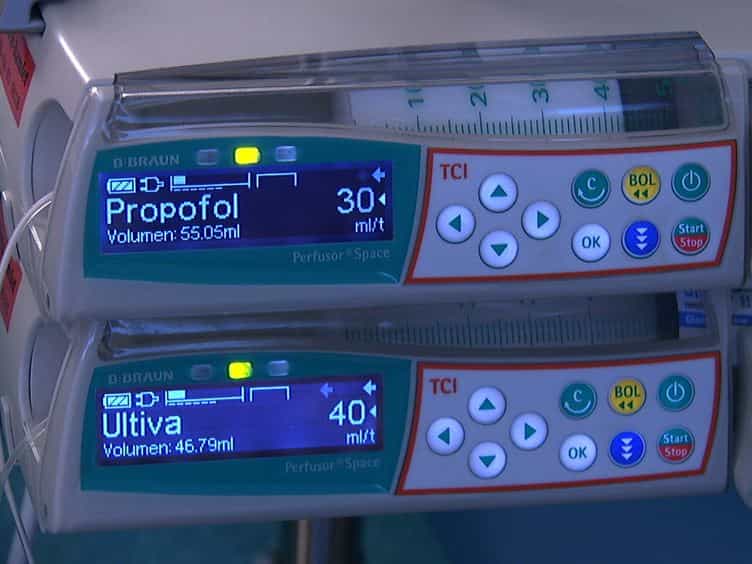
Clinical observation of opioid-sparing anesthesia combined with QLB in patients undergoing gynecological laparoscopic
Qian Ge1, Guoxu Liu2, Fan Yang1
1Department of Anesthesiology, Dalian Third People's Hospital, Dalian, Liaoning, China.

Background:
Laparoscopic surgery has become the mainstream approach for gynecological procedures. However, postoperative pain, particularly visceral pain, remains a major obstacle to achieving enhanced recovery after surgery. Therefore, this study aimed to observe the clinical effects of opioid-sparing anesthesia combined with a quadratus lumborum block (QLB) in patients undergoing gynecological laparoscopic surgery to provide a reference for clinical practice.
Methods:
A total of 80 female patients (aged 18 to 65 years, body mass index 18 to 28 kg/m2, American Society of Anesthesiologists I-II) scheduled for elective gynecological laparoscopic surgery under general anesthesia were enrolled and randomly assigned to 2 groups (n = 40 each): the control group (Group C) and the treatment group (Group T). All patients received general anesthesia. In Group T, a bilateral QLB was additionally performed under ultrasound guidance after the induction of general anesthesia. The following parameters were recorded for both groups: general demographic data and perioperative parameters; total intraoperative remifentanil consumption; postoperative analgesic pump consumption at 0 to 24 hours and 24 to 48 hours; the number of effective presses and total presses of the analgesic pump during 0 to 24 hours and 24 to 48 hours postoperatively; numerical rating scale (NRS) scores at rest and during movement at 2 hours, 6 hours, 12 hours, 24 hours, and 48 hours postoperatively; the rescue analgesia rate within 48 hours postoperatively; and the incidence of adverse reactions (hypotension, respiratory depression, postoperative nausea and vomiting [PONV], somnolence).
Results:
Compared with Group C, patients in Group T had significantly reduced the following parameters: total intraoperative remifentanil consumption (P < .05); analgesic pump consumption at 0 to 24 hours and 24 to 48 hours postoperatively (P < .05); the number of effective presses and total presses of the analgesic pump during 0 to 24 hours and 24 to 48 hours postoperatively (P < .05); resting NRS scores at 12 hours, 24 hours, and 48 hours postoperatively (P < .05); and movement NRS scores at 6 hours, 12 hours, 24 hours, and 48 hours postoperatively (P < .05). Furthermore, the rescue analgesia rate within 48 hours postoperatively was significantly lower in Group T compared to Group C (P < .05). Regarding adverse reactions, the incidence of PONV in Group T was considerably lower than that in Group C (P < .05).
Conclusion:
For gynecological patients undergoing laparoscopic surgery, the application of opioid-sparing anesthesia combined with a QLB provides effective analgesia, reduces intraoperative opioid consumption, prolongs the duration of postoperative analgesia, lowers the incidence of PONV, and promotes enhanced postoperative recovery.
Related Concept Videos
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:11
Local Anesthetics: Clinical Application as Spinal Anesthesia
 01:29
Local Anesthetics: Clinical Application as Epidural Anesthesia
Since epidural anesthetics can be infused through an epidural catheter, all types of drugs, including short-acting ones, can be administered. Chloroprocaine and lidocaine are examples of short and long-duration anesthetics, respectively. Bupivacaine...