Related Experiment Video
Updated: Aug 7, 2026
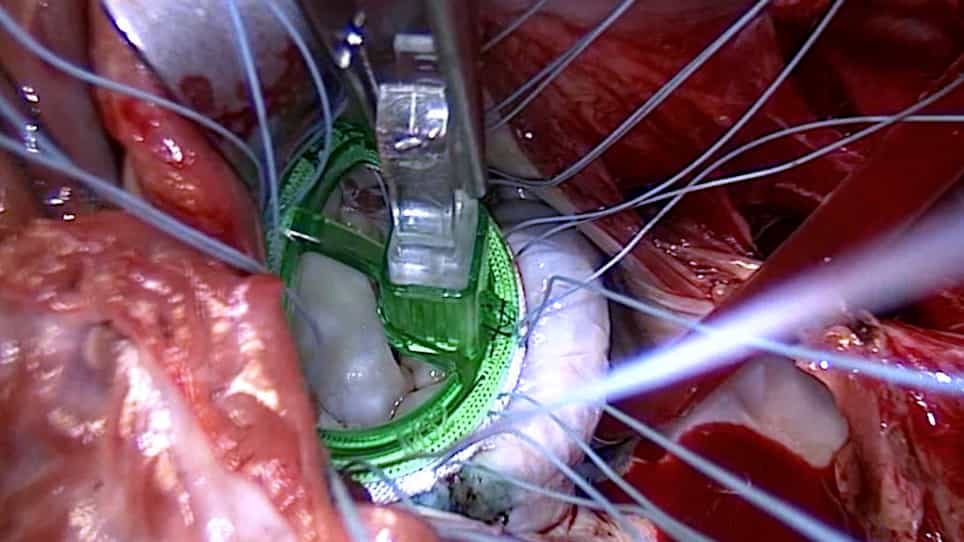
Cox-Maze IV Procedure Concomitant with Valvular Surgery In Situs Inversus Dextrocardia: A Single-Center Experience in China
Published on: February 11, 2022
Valve-sparing surgery for right-sided endocarditis presenting as a giant right atrial mass in a hemodialysis patient
David Bellido-Yarlequé1, Roberto Baltodano-Arellano2, Rossi Ramos-Isidro1
1Cardiac Surgery Unit, Guillermo Almenara Irigoyen National Hospital, Lima, Peru.

Tricuspid valve infective endocarditis (TVIE) is an uncommon form of right-sided endocarditis, typically associated with intravenous drug use or intravascular devices. Diagnosis is often delayed in immunocompromised patients, particularly those undergoing chronic hemodialysis (HD). We describe a 51-year-old woman with systemic lupus erythematosus (SLE), diabetes, and end-stage renal disease (ESRD) on chronic HD via a tunneled central venous catheter (TCVC). She presented with generalized weakness, hypotensive episodes during HD, and persistent fever. Blood cultures grew Staphylococcus aureus, and chest computed tomography (CT) revealed bilateral cavitary nodules consistent with septic pulmonary emboli. Transesophageal echocardiography (TEE) identified a 5 × 2.3-cm mobile and digitiform vegetation attached to the tricuspid valve, extending into the right atrium and superior vena cava (SVC). Despite targeted antibiotics, the infection persisted. Intraoperative findings revealed a 7-cm fibrous mass with a 3-cm calcified base adherent to the tricuspid valve, extending into the right atrium and causing near-total occlusion of the SVC. The mass was excised, and the native valve was successfully preserved. The postoperative course was uneventful. This case highlights the diagnostic and therapeutic complexity of TVIE in immunosuppressed dialysis patients. Surgical intervention was indicated due to persistent bacteremia, embolic complications, and large vegetations, in line with current European Society of Cardiology (ESC) guidelines. Notably, the native valve was preserved despite extensive intracardiac involvement, representing a favorable surgical outcome. Clinicians should maintain a high index of suspicion for right-sided endocarditis in dialysis patients presenting with respiratory or embolic symptoms.
Tricuspid valve infective endocarditis (TVIE) is an uncommon form of right-sided endocarditis, typically associated with intravenous drug use or intravascular devices. Diagnosis is often delayed in immunocompromised patients, particularly those undergoing chronic hemodialysis (HD). We describe a 51-year-old woman with systemic lupus erythematosus (SLE), diabetes, and end-stage renal disease (ESRD) on chronic HD via a tunneled central venous catheter (TCVC). She presented with generalized weakness, hypotensive episodes during HD, and persistent fever. Blood cultures grew Staphylococcus aureus, and chest computed tomography (CT) revealed bilateral cavitary nodules consistent with septic pulmonary emboli. Transesophageal echocardiography (TEE) identified a 5 × 2.3-cm mobile and digitiform vegetation attached to the tricuspid valve, extending into the right atrium and superior vena cava (SVC). Despite targeted antibiotics, the infection persisted. Intraoperative findings revealed a 7-cm fibrous mass with a 3-cm calcified base adherent to the tricuspid valve, extending into the right atrium and causing near-total occlusion of the SVC. The mass was excised, and the native valve was successfully preserved. The postoperative course was uneventful. This case highlights the diagnostic and therapeutic complexity of TVIE in immunosuppressed dialysis patients. Surgical intervention was indicated due to persistent bacteremia, embolic complications, and large vegetations, in line with current European Society of Cardiology (ESC) guidelines. Notably, the native valve was preserved despite extensive intracardiac involvement, representing a favorable surgical outcome. Clinicians should maintain a high index of suspicion for right-sided endocarditis in dialysis patients presenting with respiratory or embolic symptoms.
Supplementary Information:
The online version contains supplementary material available at 10.1007/s12055-026-02203-x.


Related Concept Videos
 01:21
Cardiac Catheterization II: Right Heart Catheterization
 01:26
Mitral Stenosis III: Medical Management
 01:22
Mitral Stenosis I: Introduction
 01:25
Aortic Regurgitation III: Medical Management
 01:23
Mitral Stenosis II: Clinical features and Diagnostic Tests
 01:24
Cardiac Catheterization III: Left Heart Catheterization