Related Experiment Video
Updated: Aug 11, 2026
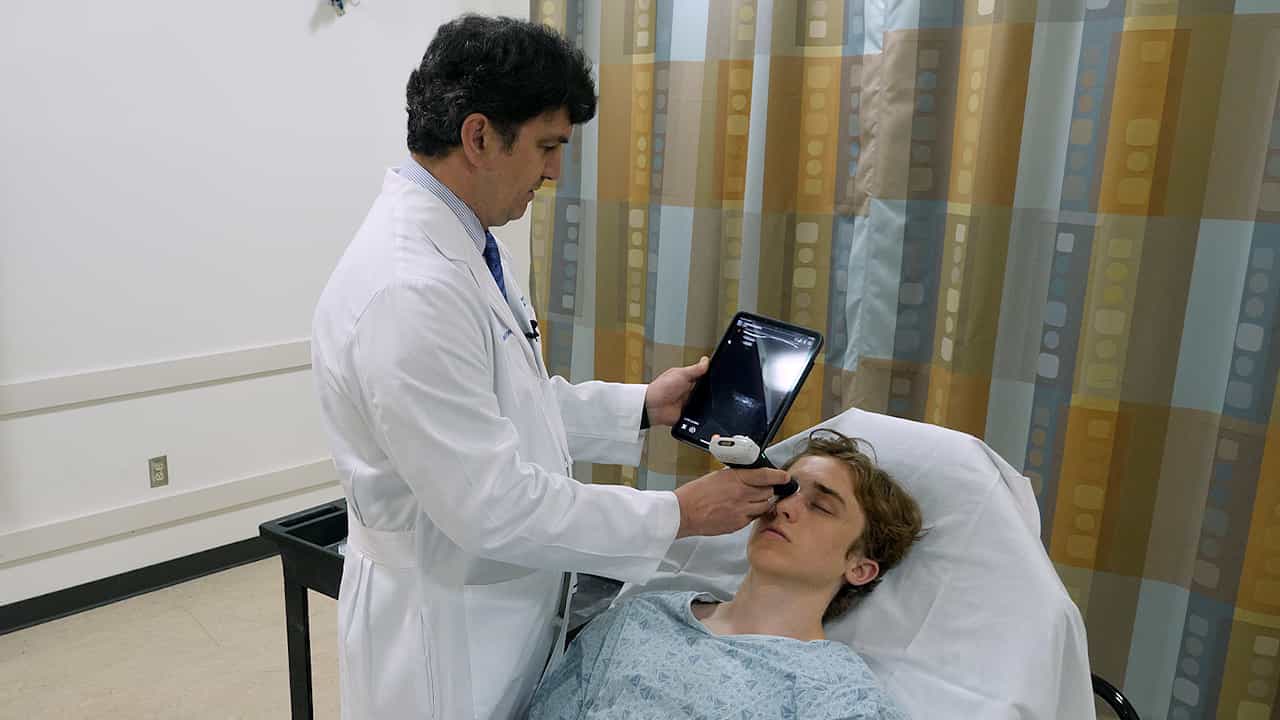

Optic Nerve Sheath Point of Care Ultrasound: Image Acquisition
Published on: August 18, 2023
Prognostic Value of Ultrasonographic Optic Nerve Sheath Diameter in Patients with Sepsis in the Intensive Care Unit:
Kamuran Uluç1, Ahmet Oğuzhan Küçük2
1Department of Intensive Care, Muş State Hospital, Muş, Turkey.

Background:
Sepsis is a life-threatening condition characterized by organ dysfunction and may involve the central nervous system through blood-brain barrier disruption and increased intracranial pressure. Ultrasonographic optic nerve sheath diameter (ONSD) is a non-invasive surrogate marker of intracranial pressure. This study aimed to evaluate the prognostic value of ONSD for mortality prediction and its association with disease severity in patients with sepsis admitted to the intensive care unit (ICU).
Materials And Methods:
This prospective observational study included 110 adult patients diagnosed with sepsis according to Sepsis-3 criteria and admitted to a tertiary ICU between June 2024 and March 2025. ONSD was measured at ICU admission using standardized ultrasonographic techniques. Demographic data, clinical scores (SOFA, APACHE II, GCS, and CCI), laboratory parameters, and outcomes were recorded. Patients were followed until ICU discharge or death, and survival time was defined as the interval from ICU admission to death or censoring at discharge. Cox proportional hazards regression and receiver operating characteristic (ROC) analyses were performed.
Results:
Thirty-five patients (32%) were non-survivors and 75 (68%) were survivors. ONSD was significantly higher in non-survivors than survivors [5.33 (4.95-5.76) mm vs 4.81 (4.67-4.93) mm; p=0.001]. Non-survivors also had higher SOFA and APACHE II scores, lactate, CRP, and procalcitonin levels, and lower albumin levels and PaO2/FiO2 ratios (all p=0.001). In univariate analysis, ONSD was associated with mortality; however, multivariate Cox regression identified SOFA (HR: 1.165; p=0.044), albumin (HR: 0.470; p=0.012), and lactate (HR: 3.324; p=0.006) as independent predictors. ONSD showed good discriminatory performance (AUC: 0.855; cut-off: 5.0 mm), correlated with severity and inflammatory parameters, and ONSD ≥5 mm was associated with shorter survival (p=0.001).
Conclusion:
ONSD may serve as a rapid, bedside, non-invasive complementary marker for early risk stratification when interpreted with established clinical scores and laboratory parameters.