Related Experiment Video
Updated: Sep 22, 2026
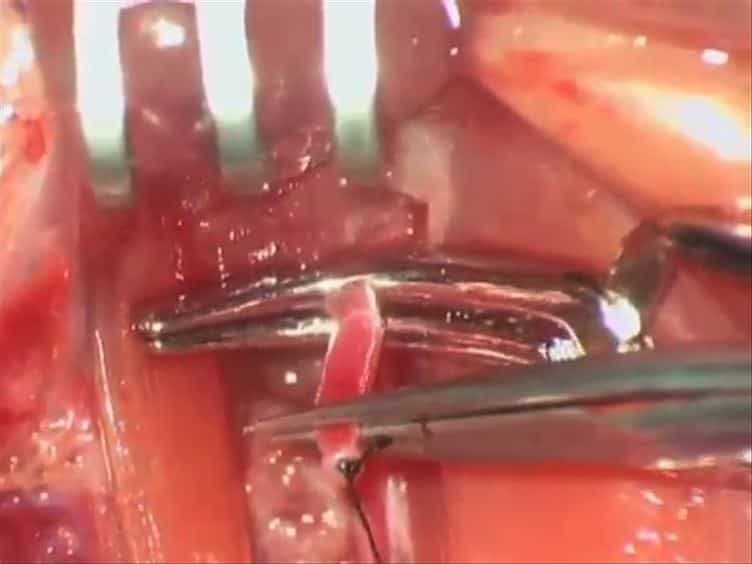

Training a Sophisticated Microsurgical Technique: Interposition of External Jugular Vein Graft in the Common Carotid Artery in Rats
Published on: November 11, 2012
Restoring Cerebral Venous Outflow: Right Internal Jugular to Subclavian Vein Bypass After Ligation in Thoracic Outlet
Dushan Miladinovic1, Luca Borruso1, Eshan Affan2
1Department of Vascular Surgery, Royal Prince Alfred Hospital, Sydney, NSW, Australia.

Abstract:
BackgroundIntracranial venous hypertension (IVH) is an underrecognised cause of persistent craniofacial symptoms, often presenting with nonspecific features such as pressure-type headaches, pulsatile tinnitus, and visual disturbances. This case illustrates a complex diagnostic dilemma in which symptoms classically attributed to Eagle Syndrome masked another vascular cause of intracranial venous hypertension. The patient provided informed consent for treatment and for the use of his clinical information in this case report.Case SummaryA 59-year-old woman presented with refractory craniofacial symptoms initially attributed to bilateral Eagle Syndrome. Despite bilateral stylodectomy, internal jugular vein (IJV) decompression, C1 transverse process resection, and right occipital sinus stenting, her symptoms persisted. During right-sided intervention for Eagle Syndrome, the right IJV was found to have been previously ligated at the clavicle during venous thoracic outlet syndrome surgery. Venous manometry demonstrated elevated pressures within the right IJV (32 mmHg) and torcula (29 mmHg), supporting IVH secondary to impaired venous outflow. Definitive treatment consisted of a right IJV-subclavian vein (SCV) bypass using a triple-panel great saphenous vein (GSV) graft to achieve an adequate conduit diameter. The postoperative course was complicated by early graft thrombosis and neck hematoma, requiring urgent hybrid open and endovascular reintervention. This included suction thrombectomy, angioplasty, sequential stenting of the bypass using bare-metal, covered, and dedicated venous stents, and open repair of a graft tear with bovine pericardial patch angioplasty. Following reintervention, the bypass remained patent on follow-up imaging, with complete resolution of headaches, pulsatile tinnitus, and visual symptoms.ConclusionThis case highlights the importance of comprehensive venous evaluation in patients with persistent craniofacial symptoms, particularly following thoracic outlet interventions. It also demonstrates the feasibility of triple-panel GSV grafting for central venous reconstruction and the value of a hybrid surgical-endovascular approach in managing complex venous complications.

Related Concept Videos
 01:19
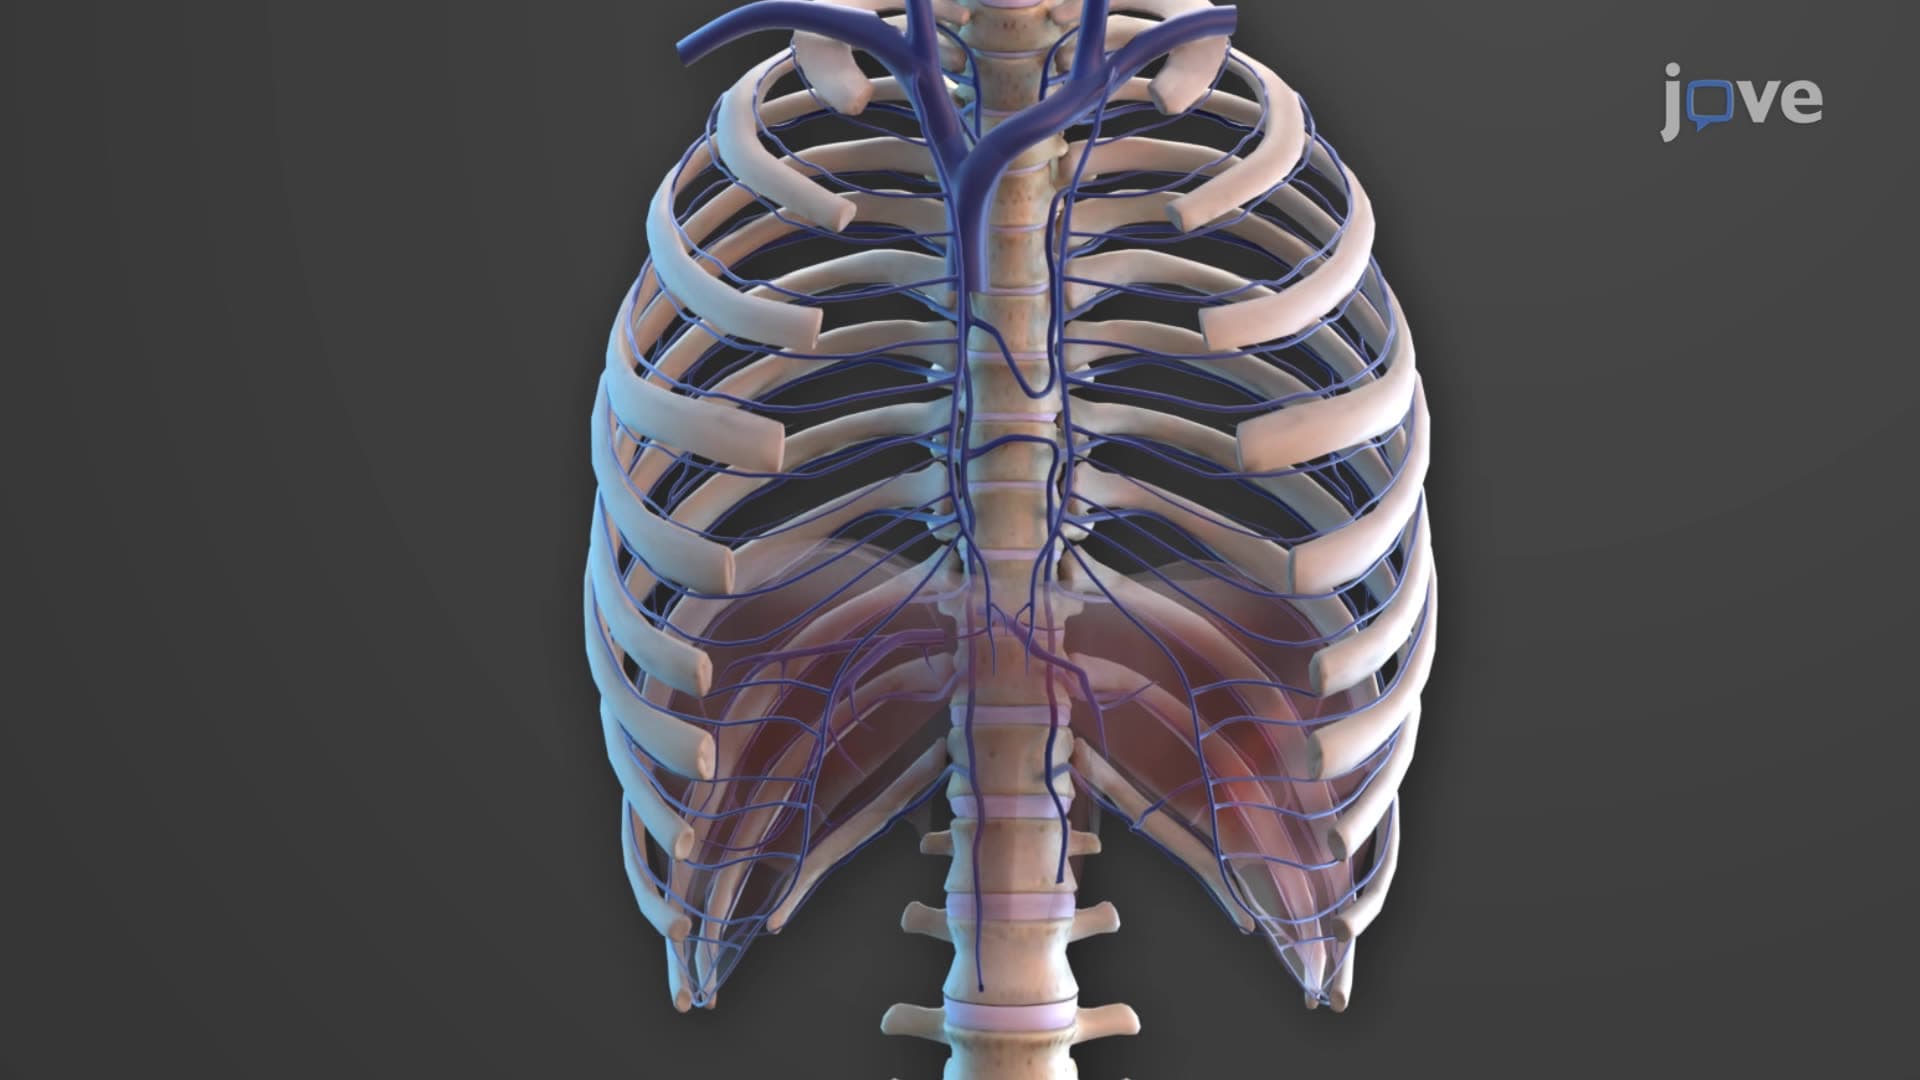
Veins of Thorax
The azygos vein, positioned just right of the midline and anterior to the vertebral column, begins at the junction of the right ascending lumbar and subcostal veins, terminating in the superior vena cava. This vein drains blood from the right side of the thoracic wall, thoracic viscera, and posterior abdominal wall.
The...
 01:19
Veins of Head and Neck
On the other hand, the vertebral veins, unlike their arterial counterparts, are not primarily responsible for brain drainage. Instead, they drain the cervical vertebrae, spinal cord, and some small...
 01:16
Lymphatic Vessels and Lymph Transport
This one-way system allows fluids, solutes, and even pathogens to enter but prevents their return to the intercellular spaces.
 01:29
Venous Thrombosis III: Interprofessional Care