Related Experiment Video
Updated: Aug 12, 2026
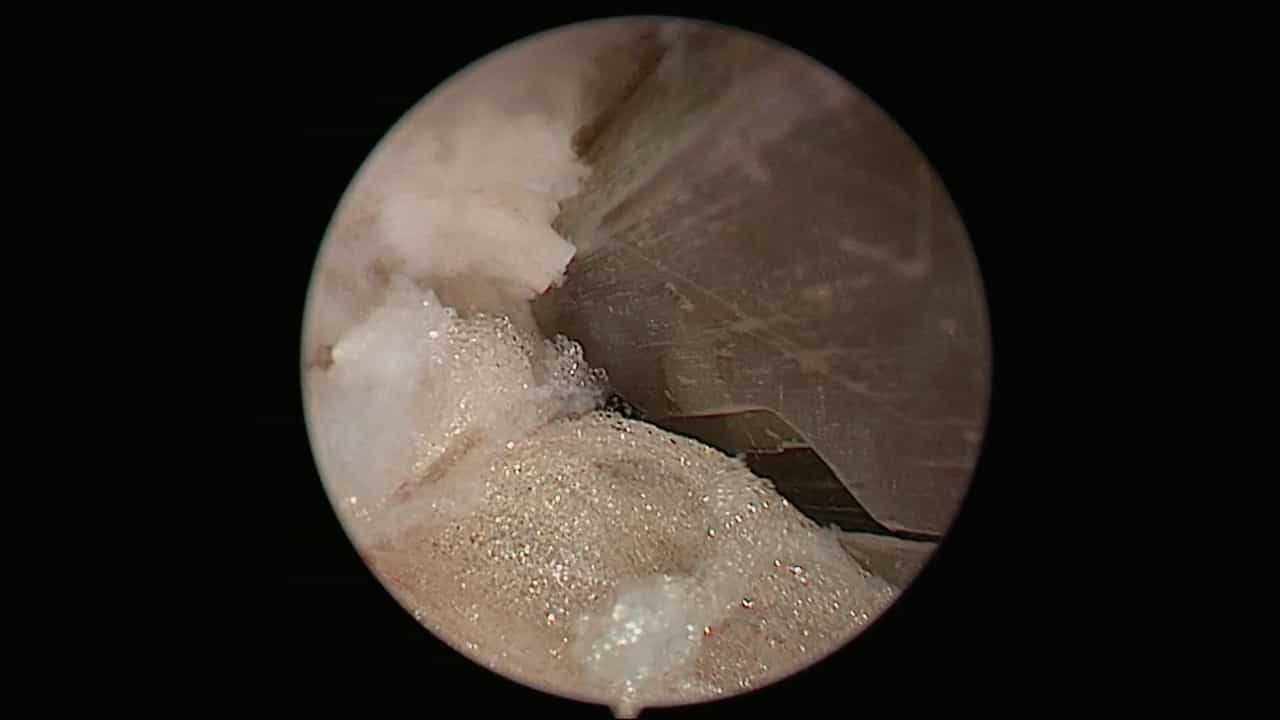
The Third Channel-Assisted Unilateral Biportal Endoscopic Technique for Lumbar Spinal Stenosis Combined with Contralateral Disc Herniation
Published on: November 17, 2023
Development and validation of a clinical predictive model for the risk of recurrence after unilateral biportal
Zhen Yi1, Changhe Liao2, Ting Wu2,3
1Department of Traditional Chinese Medicine, Foshan No. 5 People's Hospital, Foshan, Guangdong.

Background:
To identify the independent risk factors for postoperative recurrence following unilateral biportal endoscopic discectomy (UBED) for lumbar disc herniation (LDH), and to develop and validate a recurrence risk prediction model.
Objective:
To analyze the risk factors contributing to postoperative recurrence in patients with LDH treated by UBED, and to construct and validate a predictive nomogram for recurrence risk after UBED.
Methods:
A total of 257 patients with single-level LDH who underwent UBED were retrospectively enrolled, among whom 24 presented postoperative recurrence, corresponding to a recurrence rate of 9.34%. The cohort was split into a training set (n = 179) and a validation set (n = 78) at a 7:3 ratio. Thirty clinical and radiological parameters were collected. Least Absolute Shrinkage and Selection Operator (LASSO) regression combined with multivariate logistic regression was applied to screen independent risk factors, and a nomogram prediction model was subsequently established. Model performance was assessed via receiver operating characteristic (ROC) curves, Hosmer-Lemeshow (H-L) test, calibration curves, and decision curve analysis (DCA).
Results:
Twelve independent risk factors for postoperative recurrence were identified. The area under the ROC curve (AUC) reached 0.976 in the training set and 0.953 in the validation set. The P values of the H-L test were both >0.05 in the two datasets, indicating favorable model calibration. The model yielded significant clinical net benefit within threshold probabilities of 0-0.92 (training set) and 0-0.89 (validation set).
Conclusions:
The established nomogram incorporating 12 clinical and radiological variables exhibits satisfactory discrimination and calibration for predicting recurrence after UBED. It serves as a quantitative tool for rapid identification of patients at high recurrence risk in clinical practice. Nevertheless, limitations including single-center retrospective design, relatively small sample size, and an events-per-variable (EPV) ratio of approximately 2:1 (far below the recommended threshold) introduce potential overfitting and limited generalizability. This model is only applicable for preliminary screening of high-risk individuals and preoperative patient counseling, rather than acting as the sole basis for clinical decision-making. Multicenter, large-sample prospective cohort studies are warranted for further external validation and model refinement in the future.