Related Experiment Video
Updated: Aug 14, 2026
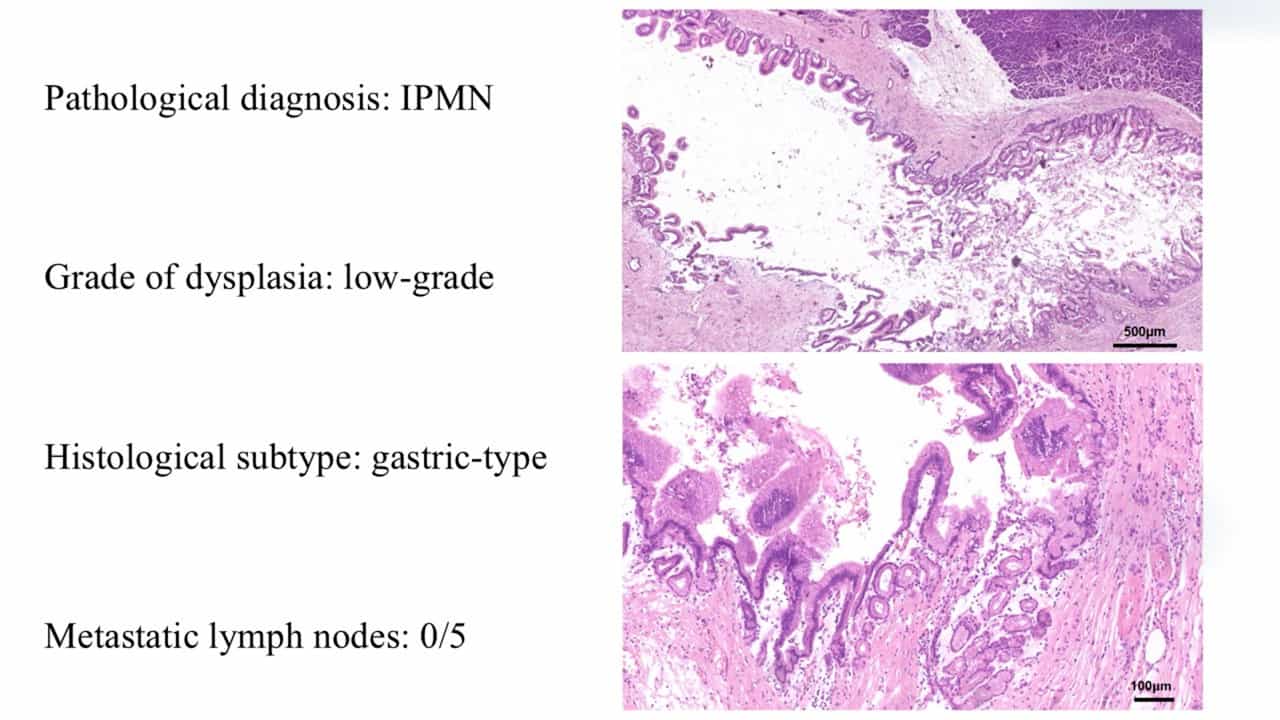

Robotic Duodenum-preserving Total Pancreatic Head Resection for Intraductal Papillary Mucinous Neoplasms
Published on: April 17, 2026
Pancreatic Collision Tumor Composed of Solid Pseudopapillary Neoplasm and Well-Differentiated Neuroendocrine Tumor:
Jose Valentin Lopez1, Nian Jiang1, David Cartwright1
1Department of Laboratory Medicine and Pathology, University of Minnesota, Minneapolis, USA.

Abstract:
Collision tumors are uncommon neoplasms composed of two histologically distinct tumor populations occurring within the same anatomic site while maintaining separate boundaries. Pancreatic collision tumors composed of solid pseudopapillary neoplasm (SPN) and well-differentiated pancreatic neuroendocrine tumor (PanNET) are rare and may be diagnostically challenging because these entities can show overlapping morphologic and immunophenotypic features and may radiographically present as a single lesion. A 41-year-old woman presented with left upper quadrant abdominal pain and was found to have a pancreatic head mass. Fine-needle aspiration favored SPN, and the patient underwent extended pancreaticoduodenectomy. Histologic examination demonstrated a 3.7 cm SPN and an adjacent 0.6 cm World Health Organization grade 1 PanNET, separated by an abrupt interface without appreciable intermingling. Immunohistochemistry showed nuclear β-catenin and cyclin D1 expression in the SPN, while the PanNET showed diffuse chromogranin and INSM1 expression with retained membranous E-cadherin. Synaptophysin was positive in both tumors, highlighting a diagnostic pitfall. Eighteen lymph nodes were negative for metastatic disease, and both tumors were confined to the pancreas. This case represents the fourth reported pancreatic SPN-WDNET collision tumor and highlights important diagnostic and classification challenges in pancreatic neoplasms that demonstrate dual differentiation. Because SPNs may exhibit partial neuroendocrine differentiation, neuroendocrine marker positivity alone should not be used to establish a diagnosis of WDNET in the setting of SPN. Instead, accurate classification requires careful integration of histomorphology and complementary immunophenotypic findings.