Related Experiment Video
Updated: Aug 15, 2026
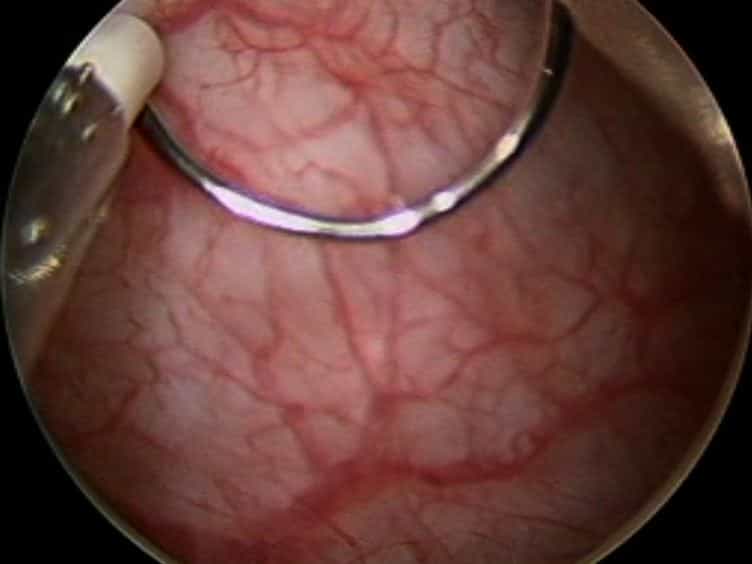
Probe-based Confocal Laser Endomicroscopy of the Urinary Tract: The Technique
Published on: January 10, 2013
Immediate intraoperative detrusor muscle status at primary transurethral resection of bladder tumour: a prospective,
Martin J Connor1,2,3, Archana Gopalakrishnan1, Nikhil Mayor1
1Division of Surgery, Department of Surgery and Cancer, Faculty of Medicine, Imperial College London, London, UK.

Objectives:
To evaluate ex vivo fluorescence confocal microscopy (FCM) for immediate detrusor muscle (DM) assessment during primary transurethral resection of bladder tumour (TURBT).
Patients And Methods:
This prospective, blinded, paired-cohort feasibility study enrolled consecutive patients undergoing primary TURBT for suspected non-muscle-invasive bladder cancer between September 2024 and September 2025 (IB1-LaserComplete study; International Standard Randomised Controlled Trial Number Register [ISRCTN]16114765). Ex vivo FCM generates immediate high-resolution digital images of fresh tissue, enabling immediate DM assessment. Intraoperative ex vivo FCM imaging of en face tumour base specimens was performed using the Histolog® scanner (SamanTree Medical SA, Lausanne, Switzerland). DM status was reported by a blinded uro-pathologist and urologist. Formalin-fixed histopathology served as the reference standard. The primary outcome was technical feasibility, defined as acquisition of an interpretable FCM image. Secondary outcomes included exploratory diagnostic performance, inter-observer agreement and time to confirmation of DM status.
Results:
A total of 34 patients were recruited and 30 had evaluable paired specimens. DM was absent in 13% (four of 30). FCM was sufficient for determining DM status in all patients (100%; 30 of 30). Sensitivity, specificity, positive predictive value, negative predictive value (NPV) were 42% (95% confidence interval [CI] 26-61%), 100% (95% CI 51-100%), 100% (95% CI 74-100%), and 21% (95% CI 9-43%), respectively. Inter-observer agreement between the uro-pathologist and urologist was high at 83% (κ = 0.72, 95% CI 0.47-0.97). The median (interquartile range) time to confirm DM status was 5.4 (4.95-5.39) min vs 11 (7-13.8) days using standard histopathology.
Conclusion:
Fluorescence confocal microscopy is feasible for rapid intraoperative imaging of TURBT specimens and demonstrates excellent specificity for detection of DM. However, its low sensitivity and NPV preclude use as a stand-alone tool to exclude DM intraoperatively. Based on these findings, FCM should not guide intraoperative decision making outside research settings.

