Related Experiment Video
Updated: Aug 21, 2026
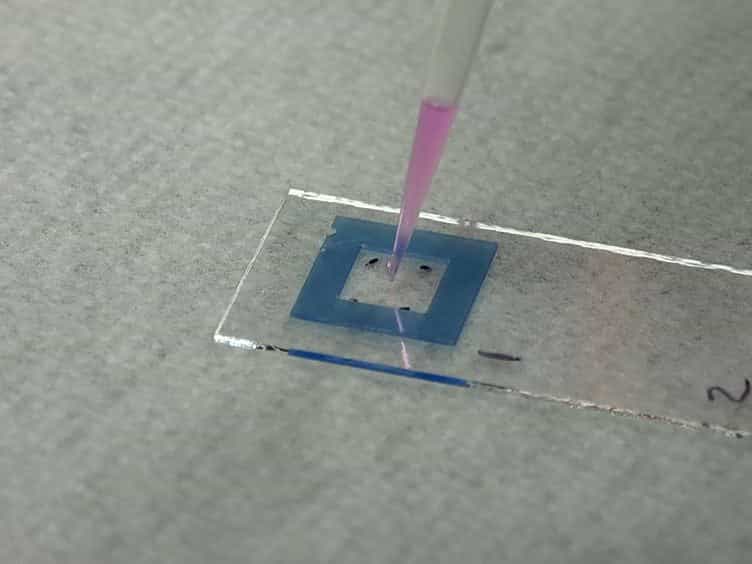

Demonstrating a Multi-drug Resistant Mycobacterium tuberculosis Amplification Microarray
Published on: April 25, 2014
Drug-resistant tuberculosis and pulmonary co-infections in immunocompromised patients: from multi-omics to precision
Ahong Wang1, Hanizaier Reheman1, Xiangtao Chen1
1Department of Respiratory and Critical Care Medicine, Kashi Prefecture Second People's Hospital, Kashi, Xinjiang, China.

Abstract:
Drug-resistant tuberculosis remains a major global health threat, with an estimated 400,000 people developing rifampicin-resistant/multidrug-resistant tuberculosis (RR/MDR-TB) worldwide in 2023, according to the WHO Global Tuberculosis Report 2024. Immunocompromised populations, including people living with HIV, transplant recipients, patients receiving immunosuppressive therapies, and individuals with chronic metabolic diseases, are at particularly high risk of severe disease and pulmonary co-infections, resulting in delayed diagnosis, increased treatment complexity, and poor clinical outcomes. Despite advances in therapeutics, management remains constrained by fragmented diagnostic pathways, limited pathogen resolution, antimicrobial toxicity, and clinically significant drug-drug interactions. Recent progress in multi-omics technologies is reshaping understanding of host-pathogen dynamics in tuberculosis and co-infection states. Whole-genome sequencing enables rapid resistance prediction and transmission tracking, whereas transcriptomic, proteomic, metabolomic, and single-cell approaches are identifying biomarkers of disease severity, immune dysregulation, treatment response, and relapse risk. Parallel advances in metagenomic diagnostics and artificial intelligence-assisted imaging offer opportunities for earlier detection of mixed infections and improved clinical triage. Therapeutic paradigms are also evolving. Shorter all-oral regimens, individualized dosing strategies, therapeutic drug monitoring, and integrated antimicrobial stewardship are improving outcomes for resistant tuberculosis. Adjunctive approaches, including host-directed therapies, immunomodulation, inhaled drug delivery systems, and data-guided precision prescribing, may further enhance efficacy while reducing toxicity in vulnerable patients with co-infections. However, implementation remains uneven, and prospective evidence in immunocompromised populations is limited. Recent advances in multi-omics technologies including whole-genome sequencing, metagenomics, transcriptomics, proteomics, metabolomics, single-cell omics, and artificial intelligence-assisted diagnostics are transforming the diagnosis, biological stratification, and clinical management of DR-TB. In parallel, precision therapeutic approaches, including individualized regimen selection, therapeutic drug monitoring, host-directed therapies, and data-guided clinical decision-making, are enabling more personalized treatment strategies. This review integrates these advances into a precision medicine framework and discusses their clinical application, current limitations, and future directions for improving outcomes in immunocompromised patients with DR-TB and pulmonary co-infections.

Related Concept Videos
 01:28
Pulmonary Tuberculosis V
Latent tuberculosis infection occurs when TB bacteria are present in a person's body, but are not causing illness or symptoms. It is not contagious, and preventive treatment is crucial to avoid the progression...
 01:29
Pulmonary Tuberculosis I
Causative Organism
The primary infectious agent causing tuberculosis is Mycobacterium tuberculosis, a slow-growing, acid-fast, aerobic rod that exhibits sensitivity to heat and ultraviolet light. Instances of Mycobacterium bovis and Mycobacterium avium contributing to the development of TB infection are rare.
Mode of...
 01:26
Pulmonary Tuberculosis IV
Several diagnostic approaches are used to detect TB. The conventional method is the Tuberculin Skin Test (TST), also known as the Mantoux test. However, this method has...
 01:23
Tuberculosis
 02:56
Treatment Resistant Cancers
 01:28
Pulmonary Tuberculosis II
Here is a detailed explanation of its pathophysiology:
Transmission: The process begins when a person inhales droplet nuclei containing M. tuberculosis. These are typically released into the air when an individual with pulmonary or...