Related Experiment Video
Updated: Aug 22, 2026
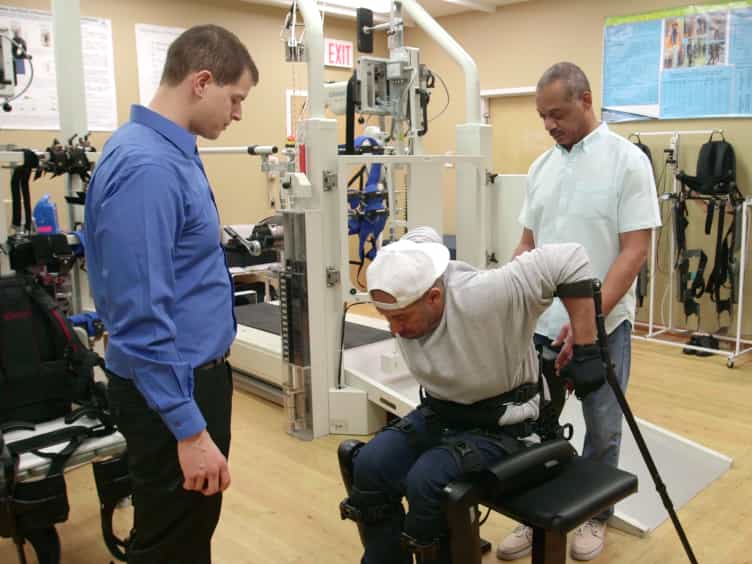

Training Persons with Spinal Cord Injury to Ambulate Using a Powered Exoskeleton
Published on: June 16, 2016
A Grade-Specific Clinical Prediction Rule for Independent Walking After Traumatic Spinal Cord Injury
Xinfang Li1, Fei Hao1, Yiping Xiong1
1School of Engineering Medicine, Beijing Advanced Innovation Centre for Biomedical Engineering, Beihang University, Beijing, China.

Objective:
To identify significant predictors of individual American Spinal Injury Association Impairment Scale (AIS) grades and develop a clinical prediction rule with differentiated prognoses for patients with different spinal cord injury (SCI) grades.
Design:
Age, sex, American Spinal Injury Association, and FIM scores were selected as predictive variables to predict independent walking 1 year after SCI. Optimal variable combinations for individual AIS classifications were screened, and various machine learning models were established.
Setting:
Analysis of the National Spinal Cord Injury Statistical Centre dataset.
Participants:
A total of 2607 participants with traumatic SCI were included in the final analysis (N=2607).
Interventions:
Not applicable.
Main Outcome Measures:
Self-reported ability to walk both indoors and outdoors.
Results:
Optimal variable combinations differed significantly across different AIS grades. For AIS A, C, and D, significant predictors were concentrated in motor and sensory scores at lumbosacral levels, with age also validated as a key predictor. However, for AIS B, key predictors were concentrated in the lower thoracic segments, with pinprick sensation being predominant. After modeling with optimal variable combinations, accuracy, F1 score, and area under the receiver operating characteristic curve value were significantly improved, especially for AIS B. Increasing model complexity improved prediction performance across all AIS grades, although the optimal model differed by grade. We therefore developed an ensemble model integrating random forest, artificial neural network, and multitask learning, which performed at least as well as any individual base model across all metrics. In addition, incorporating discharge variables, such as American Spinal Injury Association and FIM scores, significantly reduced the predictive discrepancy between AIS B+C and AIS A+D.
Conclusions:
The optimal-variable ensemble model we proposed significantly improved prediction performance for all AIS grades, especially for AIS B and C. Incorporating discharge variables significantly reduced predictive discrepancy among different grades. This grade-specific clinical prediction rule holds great significance for individualized rehabilitation and precision medicine in SCI recovery.

