Related Experiment Video
Updated: Aug 24, 2026
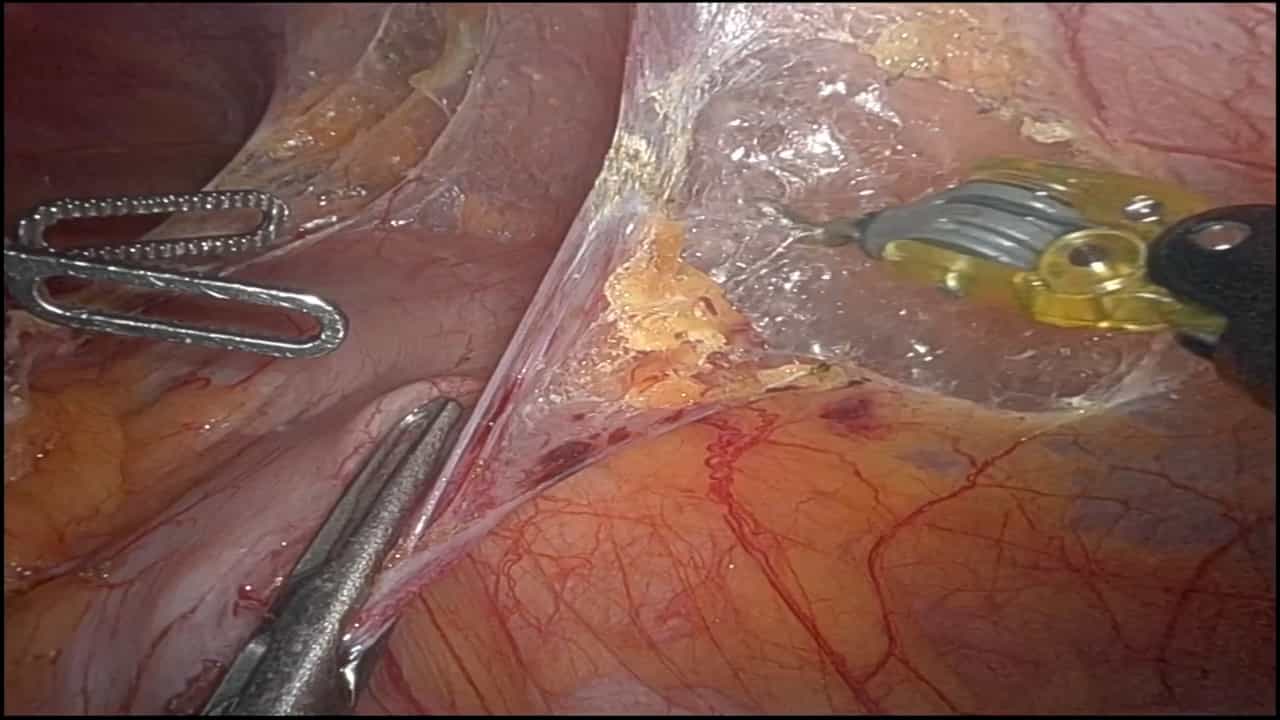

Robot-assisted Partial Splenectomy
Published on: January 2, 2026
Minimally Invasive Splenectomy for Recurrent Gynecologic Cancer and Long-Term Outcomes
Evrim Erdemoglu1, Hanna J Schaeffeler2, Paul M Magtibay3
1Department of Medical and Surgical Gynecology (Drs. Erdemoglu, Magtibay, Magrina, and Butler), Mayo Clinic, Phoenix, Arizona; Division of Gynecologic Oncology (Dr. Erdemoglu), Department of Obstetrics and Gynecology, Suleyman Demirel University, Isparta, Turkey.

Study Objective:
To evaluate the surgical safety, feasibility, and long-term oncologic outcomes of minimally invasive (MIS) splenectomy in patients with isolated or oligometastatic recurrence of gynecologic malignancies.
Design:
Retrospective single-institution cohort study (AAGL Classification of Evidence: II-3).
Setting:
Tertiary academic referral center (Mayo Clinic, AZ).
Patients:
Ten consecutive women with platinum-sensitive recurrent gynecologic cancer (6 ovarian, 2 endometrial, 2 cervical) involving the spleen or left upper quadrant. Eight patients had pathologically confirmed recurrent gynecologic malignancy; in 2, pathology revealed nongynecologic disease (necrotizing granuloma; B-cell lymphoma). The primary oncologic analysis was restricted to the 8 confirmed cases.
Interventions:
MIS splenectomy (laparoscopic, n = 6; robotic, n = 4) for secondary or tertiary cytoreduction, with concomitant procedures when needed for complete resection.
Measurements And Main Results:
All procedures were completed minimally invasively without conversion. Median operative time was 202 minutes (IQR 196.5-211.5; range 108-325) and median estimated blood loss was 50 mL (IQR 50-125; range 20-450). No intraoperative complications occurred. Postoperative complications were limited to Clavien-Dindo grade I to II; median Comprehensive Complication Index was 11.2. Median hospital stay was 42 hours (IQR 25.5-72.25). R0 resection was achieved in 10/10 patients (100%). In the primary analysis (n = 8), at a median follow-up of 53.8 months after splenectomy, 1 patient developed recurrence at 78.5 months and no patient had died; 5-year overall survival and 5-year disease-free survival were both 100% (exact 95% CI 39.8%-100%). Survival estimates should be interpreted cautiously given the small sample size.
Conclusion:
In this highly selected cohort treated at a tertiary referral center, MIS splenectomy appeared technically feasible and short-term safe and was associated with favorable observed oncologic outcomes. These findings support feasibility but do not establish causal oncologic efficacy.