Related Experiment Video
Updated: Aug 27, 2026
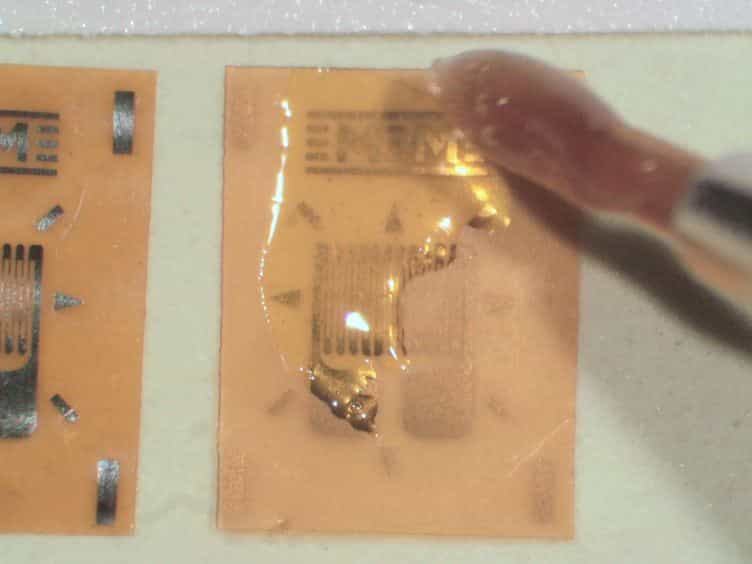

Fabrication and Implantation of Miniature Dual-element Strain Gages for Measuring In Vivo Gastrointestinal Contractions in Rodents.
Published on: September 18, 2014
Associations between body surface gastric mapping parameters and response to gastric peroral endoscopic myotomy for
Homira Ayubi1, Chris Varghese2, Mabel Tanne1
1King's College Hospital, London, United Kingdom.

Background And Aims:
Gastric per oral endoscopic myotomy (GPOEM) is a promising therapy for refractory gastroparesis, but patient selection remains challenging. We evaluated body surface gastric mapping (BSGM) phenotypes to predict treatment response.
Methods:
Patients were recruited at King's College Hospital (Nov 2022-July 2025). BSGM comprised 30 min fasting, standardized nutrient drink with oatmeal bar (482 kcal), and 4 h postprandial recording. Success was defined as ≥1 point reduction in Gastroparesis Cardinal Symptom Index or complete symptom resolution at follow-up.
Results:
Among 30 patients that completed follow-up (median 7.1 months, IQR 4.3-10.1; 77% female; median age 38.5, IQR 30-52), 53% responded to GPOEM, including all patients with dysrhythmic or continuous phenotypes. Higher gastric frequencies predicted non-response (adjusted odds ratio 0.01, 95% confidence interval 0.00-0.39, p=0.03).
Conclusions:
Clinical response to GPOEM varied by BSGM phenotype, offering a novel tool to aid patient selection.
Related Concept Videos
 01:11
Pyloric Obstruction
 01:16
Gastric Motility
Peristaltic Waves and Chyme Formation
Upon food entry, the stomach initiates...
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube through...
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:20
Gastrointestinal Motility Disorders
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.