Withholding Oral Anticoagulation at Discharge and Post-Discharge Stroke and Bleeding Vulnerability in a Predominantly Older Cohort Hospitalized With Acute Heart Failure and Atrial Fibrillation
Related Experiment Video
Updated: Aug 27, 2026
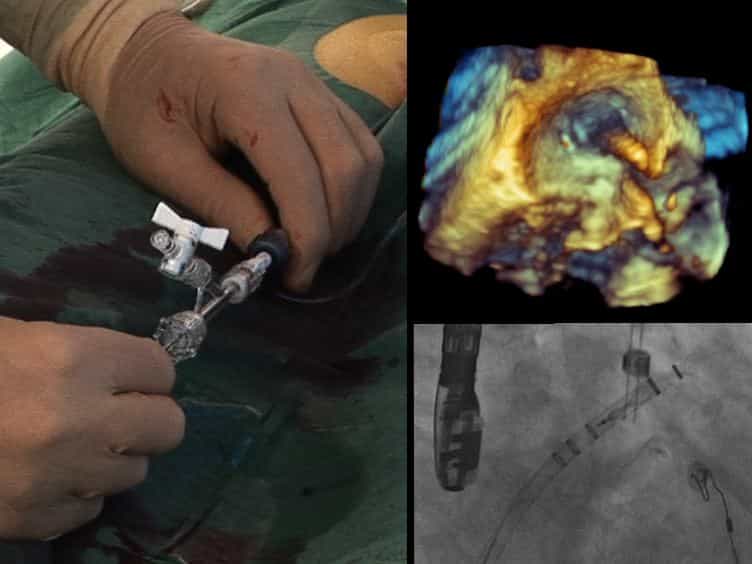
Catheter Ablation in Combination With Left Atrial Appendage Closure for Atrial Fibrillation
Published on: February 26, 2013
Jumpei Yamamoto1,2, Keijiro Nakamura1, Hiromasa Hayama2
1Division of Cardiovascular Medicine, Toho University Medical Center Ohashi Hospital, Tokyo, Japan.

Aim:
In older adults hospitalized with acute heart failure and atrial fibrillation, bleeding concern often drives withholding of oral anticoagulation at discharge. Whether withholding marks a genuinely lower bleeding-risk phenotype or residual clinical vulnerability is uncertain. We examined its association with post-discharge ischemic stroke, major bleeding, and death in a predominantly older cohort.
Methods:
We analyzed a registry of patients hospitalized with acute heart failure and atrial fibrillation. In a discharge-based analysis of patients discharged alive and free of stroke or major bleeding at discharge, we used stabilized inverse-probability-of-treatment weighting for discharge anticoagulation. Ischemic stroke and major bleeding were modeled with weighted Fine-Gray competing-risk regression (death as competing event) and death with weighted Cox regression, contrasting no anticoagulant versus anticoagulant. Age-restricted analyses (≥ 75, ≥ 80 years) and absolute risks were prespecified.
Results:
Among 560 patients (no anticoagulant 72, anticoagulant 488; mean age 78 years), withholding was associated with higher ischemic stroke (subdistribution hazard ratio 3.14, 95% confidence interval [CI] 1.26-7.81) and did not identify a lower bleeding-risk phenotype, with numerically higher major bleeding overall (1.98, 0.95-4.14) that reached significance among patients aged ≥ 80 years (2.41, 1.05-5.54). No significant association with death was observed (hazard ratio 1.34, 0.70-2.55). Three-year cumulative incidences of bleeding were 25.6% (no anticoagulant) versus 13.4% (anticoagulant).
Conclusion:
Discharge anticoagulation withholding did not identify a lower post-discharge bleeding-risk phenotype but marked residual thromboembolic vulnerability, with a higher bleeding-risk trajectory, particularly among patients aged ≥ 80 years, supporting structured post-discharge anticoagulation reassessment in older adults.
Related Concept Videos
 01:29
Venous Thrombosis III: Interprofessional Care
 01:18
Anticoagulant Drugs: Vitamin K Antagonists and Direct Oral Anticoagulants
Warfarin, a prominent vitamin K antagonist family member, exerts its effect by inhibiting the enzyme VKORC1 (vitamin K epoxide reductase complex 1). By hindering this enzyme, warfarin...
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins
 01:30
Venous Thrombosis IV: Nursing Management
 01:28
Acute Coronary Syndrome IV: Interprofessional Care
 01:23
Atherosclerosis IV: Nursing Management