Related Experiment Video
Updated: Aug 29, 2026
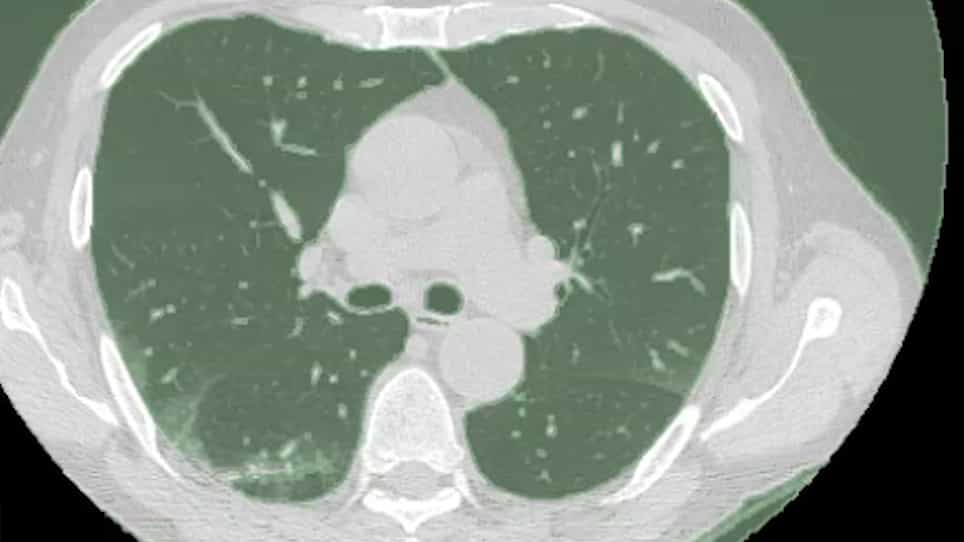

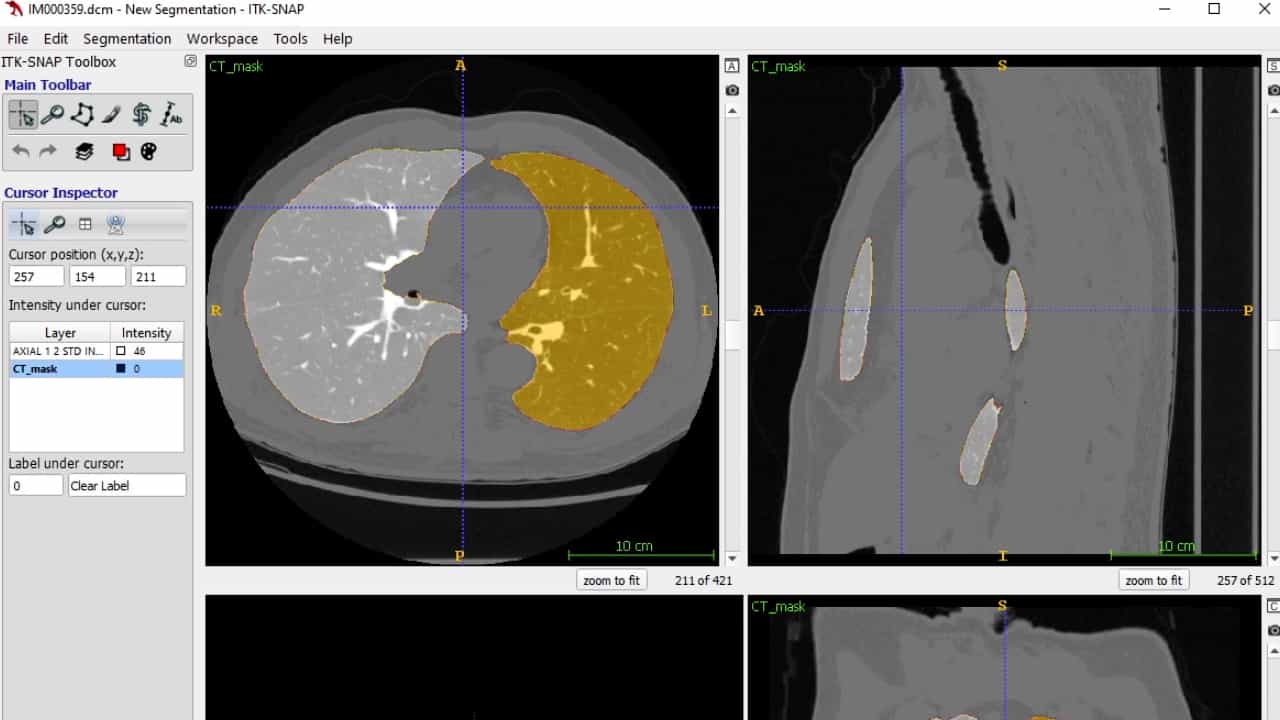
Lung CT Segmentation to Identify Consolidations and Ground Glass Areas for Quantitative Assesment of SARS-CoV Pneumonia
Published on: December 19, 2020
Automated 3D chest CT muscle segmentation-derived model development and explanation in discrimination of normal,
Yi Wang1,2, Weihao Zhai1,3,4, Qian Zhou1
1Department of Radiology, Second Affiliated Hospital of Naval Medical University, Shanghai, China.

Objectives:
To develop and validate an automated 3D chest CT muscle segmentation model using an exploratory normalization method to discriminate normal, preserved ratio impaired spirometry (PRISm), and chronic obstructive pulmonary disease (COPD) subjects.
Materials And Methods:
In this retrospective study, we used TotalSegmentator to acquire 3D pectoral muscle (PM) and erector spinae muscle (ESM) volumes from chest CT, normalizing them to height and vertebral bone volume, respectively. 2D quantitative parameters were acquired and normalized. The support vector machine models were developed based on normalized 3D and 2D muscle parameters, respectively, with ten-fold cross-validation. Receiver operating characteristic curves were used to analyze the discriminative performance of models, and the SHapley Additive exPlanations algorithm was used to quantify the importance of each parameter.
Results:
1660 subjects (616 normal, 646 PRISm, 398 COPD) (median age, 66 years [IQR: 60-72 years]; 1014 males) were included and divided into training set (n = 1162), test set (n = 498). In the test set, the 3D model (macro-average AUC, 0.735; micro-average AUC, 0.733) outperformed the 2D model (macro-average AUC, 0.646; micro-average AUC, 0.665), and 3D ESM density was the most relevant muscle parameter. 3D muscle density showed a decreasing trend from normal to PRISm to COPD. In COPD, females exhibited decreased density (difference range: -14.48 to -7.79; p < 0.001), while males had a more significant decrease in volume, especially pectoralis major volume index (difference: -11.18; 95% CI -15.57, -5.08; p < 0.001).
Conclusions:
The 3D muscle parameter model demonstrated higher discriminative performance than the 2D model for discriminating normal, PRISm, and COPD subjects.
Key Points:
Question The discriminative performance of 3D CT-based muscle quantification in subjects with impaired pulmonary function remains unclear. Findings 3D muscle analysis achieved superior discrimination of normal, PRISm, and COPD subjects, with density-related parameters showing consistent group differences, particularly ESM density. Critical relevance By comparison with conventional 2D assessment, 3D CT-based muscle quantification showed better discrimination of normal, PRISm, and COPD, which might advance the personalized precision and comprehensive assessment, including muscle alteration for subjects with impaired pulmonary function.