Related Experiment Video
Updated: Sep 2, 2026


Utilizing a 3D Printed Laparoscopic Nissen Fundoplication Model to Shorten a Resident's Learning Curve
Published on: August 15, 2025
Hand-specific speed and accuracy optimization during early endoscopic forceps training: a comparative study of
Go Kamimura1, Koki Maeda1, Masaya Aoki2
1Department of General Thoracic Surgery, Kagoshima University Graduate School of Medical and Dental Sciences, 8-35-1 Sakuragaoka, Kagoshima, 890-8520, Japan.

Background:
In endoscopic surgery, safe performance depends on functionally distinct roles of the dominant and non-dominant hands. However, skill acquisition is often evaluated using uniform, time-based metrics, which may obscure hand-specific learning patterns-particularly improvements in non-dominant-hand stability and accuracy.
Objective:
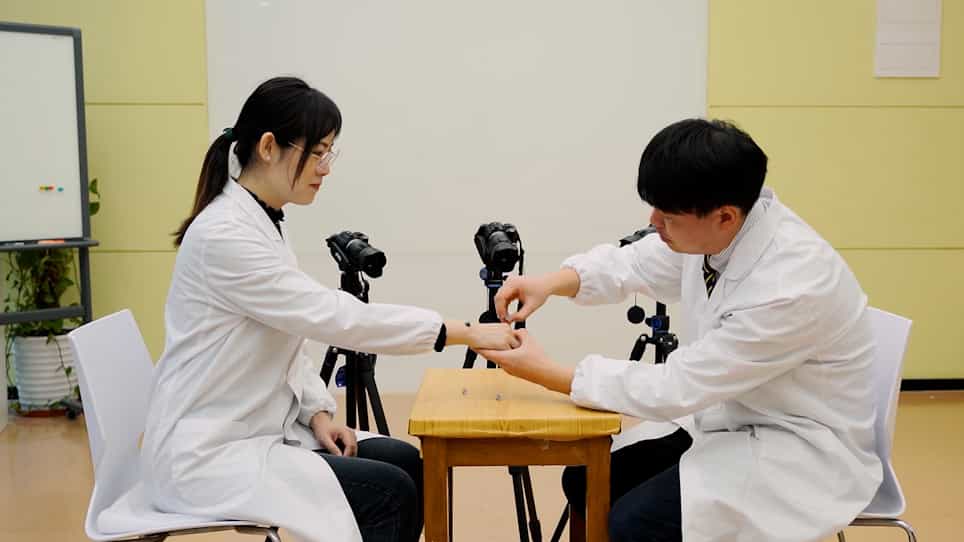
To compare dominant- and non-dominant-hand learning patterns during a two-week endoscopic forceps training program between medical students with and without surgical career aspiration, focusing on speed-accuracy trade-offs and learning-direction transitions.
Methods:
Fourth-year medical students completed a standardized dry-lab forceps transfer task over two weeks. Participants were stratified by surgical aspiration (aspirants vs non-aspirants). For each hand, weekly mean completion time and error rate were calculated. Each student-week was classified into one of four speed-accuracy profiles using fixed pooled-median cutoffs, and Week 1→Week 2 transitions were summarized using 4×4 transition tables. Group differences were further examined using ANCOVA for mean time and weighted regression for error-rate change.
Results:
Among surgical aspirants, dominant-hand performance improved mainly in speed: Week 2 mean time was shorter than in non-aspirants (mean difference -15.1 s, 95% CI -19.4 to -10.8; p<0.001). In contrast, non-dominant-hand improvement was mainly in accuracy: Week 2 error rate was lower in surgical aspirants (mean difference -0.15, 95% CI -0.19 to -0.11; p<0.001) and the reduction in error rate (Δ error rate, Week 2-Week 1) was greater (mean difference -0.11, 95% CI -0.14 to -0.08; p<0.001). Four-category transition analyses showed a prominent shift toward lower-error profiles for the non-dominant hand in surgical aspirants. These patterns persisted after adjustment for total hand-specific practice volume and age.
Conclusions:
Among novice medical students, early performance during this two-week dry-laboratory forceps task showed hand-specific patterns: dominant-hand improvement was expressed mainly through speed, whereas non-dominant-hand improvement was expressed mainly through accuracy. These task-specific findings require validation in surgical trainees, higher-fidelity tasks, and longer-term follow-up.