Related Experiment Video For MRI-fusion biopsy
Updated: Sep 3, 2026
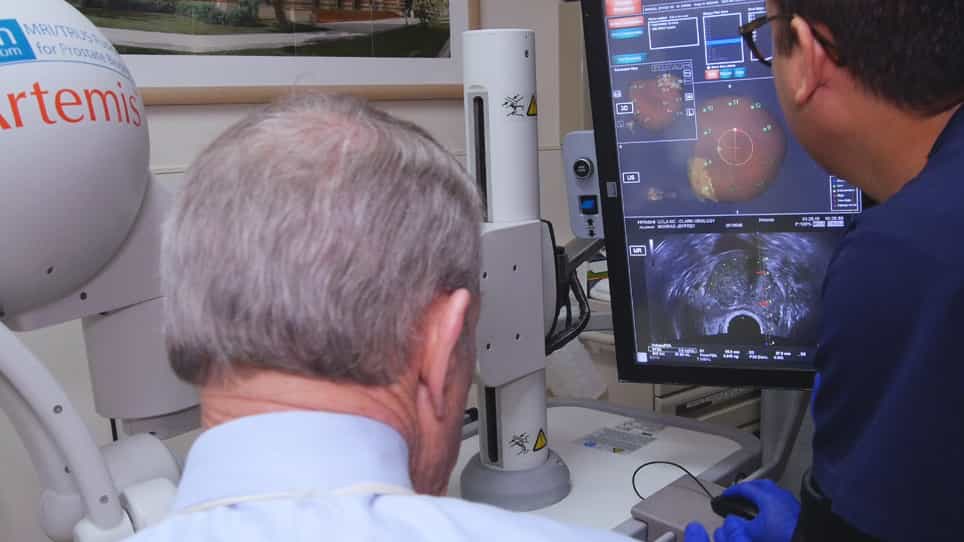

Use of MRI-ultrasound Fusion to Achieve Targeted Prostate Biopsy
Published on: April 9, 2019
Impact of Systematic Biopsy Core Number on Clinically Significant Prostate Cancer Detection and Complications in
Chung Yi Liu1,2, Ying-Hsu Chang1,2, Yu-Hsiang Lin1,3
1College of Medicine, Chang Gung University, Taoyuan, Taiwan.

Background:
This study evaluated the impact of varying systematic biopsy (SB) core numbers on the detection rates of prostate cancer (PCa) and clinically significant PCa (csPCa) in men with magnetic resonance imaging (MRI)-suspicious lesions undergoing MRI-ultrasound fusion biopsy; and to assess biopsy-related complications.
Methods:
This retrospective, non-randomized cohort study included 356 patients who underwent multi-parametric MRI followed by MRI-ultrasound fusion targeted biopsy (TB) combined with SB for suspected PCa (Prostate Imaging Reporting and Data System score ≥ 3). Patients were divided into two groups based on the number of SB cores received: ≤ 6 SB cores (n = 200) and > 6 SB cores (n = 156). Primary outcomes were overall PCa and csPCa (Gleason Grade Group ≥ 2) detection rates. Secondary outcomes included the added diagnostic value of SB for csPCa, SB upgrading rates, and post-biopsy complications.
Results:
No significant difference was observed in the overall PCa detection rate between the ≤ 6 cores and > 6 cores groups (58.0% vs 50.0%, P = 0.081) or in the overall csPCa detection rate (42.5% vs 37.2%, P = 0.182). The added diagnostic value of SB for csPCa detection (3.0% vs 3.8%, P = 0.439) and SB upgrading rate (7.0% vs 9.6%, P = 0.241) were comparable between the groups. However, the complication rate was significantly lower in the group receiving ≤ 6 SB cores compared to that receiving the > 6 SB cores (15.5% vs 26.3%, P = 0.009). Subgroup analysis indicated that SB provided significantly higher added value for csPCa detection in older patients (≥ 67 years; 5.3% vs 1.6%, P = 0.049). Multivariable logistic regression demonstrated that receiving >6 SB cores was not significantly associated with increased detection of csPCa.
Conclusion:
These findings seem support optimizing and potentially reducing the systematic component of combined biopsy. Further prospective studies are warranted to confirm these results and refine personalized biopsy protocols.


