Related Experiment Video
Updated: Sep 12, 2026
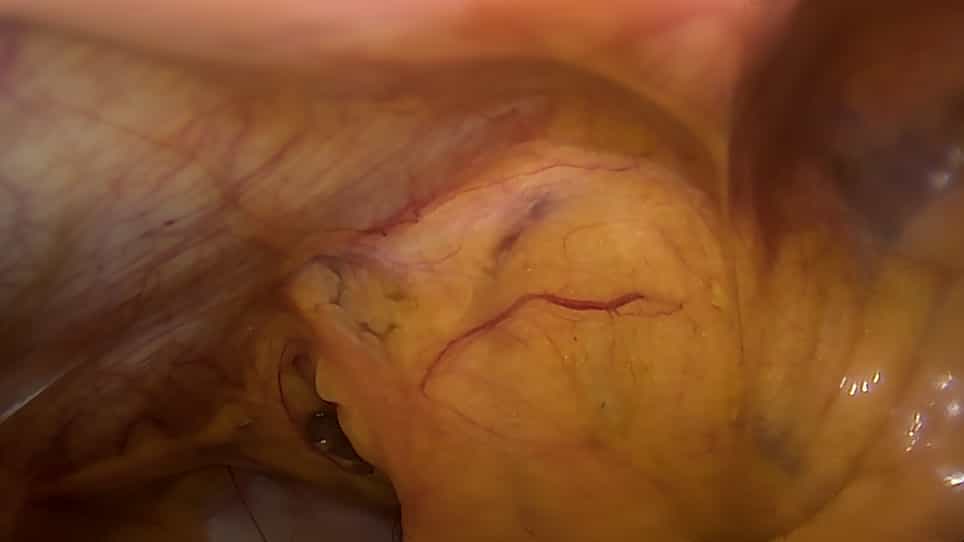

Laparoscopic Common Bile Duct Exploration in Patients with a Previous History of Biliary Tract Surgery
Published on: February 10, 2023
Preoperative predictors of difficult laparoscopic cholecystectomy after percutaneous transhepatic gallbladder
Chaoyi Zhou1, Zeliang Xia1, Liang Chu1
1Department of General Surgery, The Second Affiliated Hospital of Bengbu Medical University, Bengbu, Anhui, China.

Background:
Percutaneous Transhepatic Gallbladder Drainage (PTGBD) serves as a bridge therapy for moderate-to-severe cholecystitis. However, Laparoscopic Cholecystectomy (LC) after PTGBD is frequently complicated by chronic inflammation and fibrosis. Currently, predictive tools for difficult surgery in this population are limited, and none have integrated multidimensional parameters including novel imaging metrics and psychological assessments.
Methods:
We retrospectively analyzed 150 patients who underwent LC after PTGBD between September 2018 and May 2025. After excluding 43 patients (22 with missing data, 21 with combined procedures), 107 were included. Using univariate and multivariate logistic regression, we developed a nomogram incorporating five-dimensional preoperative parameters: 1) Baseline clinical characteristics, 2) CT imaging features, 3) PTGBD-related surgical parameters, 4) Laboratory indicators, and 5) Psychological assessments. Difficult surgery was defined by Tokyo Guidelines (TG18) criteria: operative time > 110 min, blood loss > 150 mL, or conversion to open surgery (including subtotal cholecystectomy or fundus-first technique).
Results:
Multivariate analysis identified four independent predictors: elevated C-reactive protein (CRP > 8.2 mg/L; OR = 4.21, p = 0.011), pericholecystic fluid (OR = 60.93, p < 0.001), gallbladder-duodenal adhesion index (GDAI > 0.7; OR = 4.00, p = 0.015), and increased Calot's triangle CT attenuation (HU > 30; OR = 5.82, p < 0.001). The nomogram demonstrated excellent discrimination (AUC = 0.903), significantly outperforming individual predictors (p < 0.001).
Conclusions:
The model enables precise risk stratification, which could potentially guide clinical decisions and improve surgical outcomes.
