Related Experiment Video
Updated: Sep 11, 2026
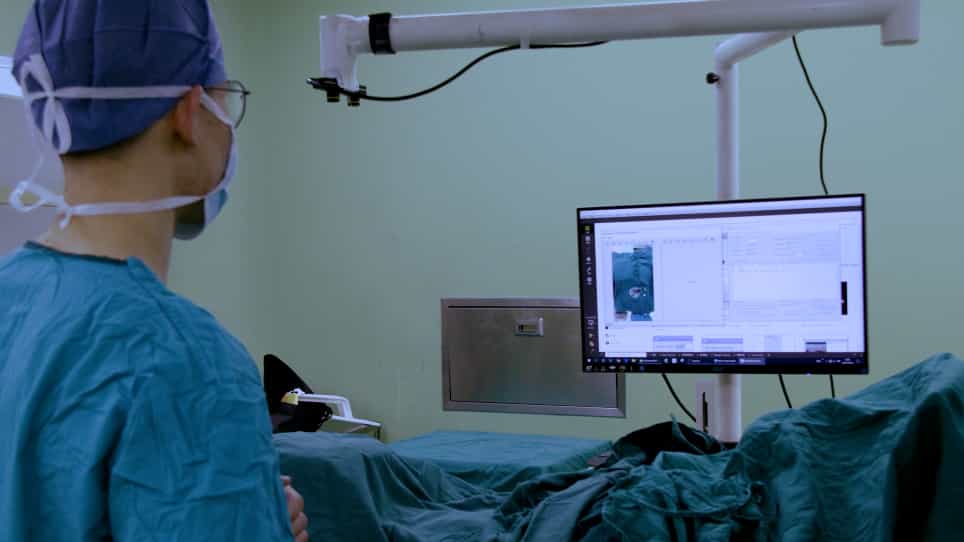

Augmented Reality Navigation-Guided Core Decompression for Osteonecrosis of Femoral Head
Published on: April 12, 2022
Comparative evaluation of mixed reality, CTA-based digital guide, and hand-held Doppler for anterolateral thigh
1Department of Oral and Maxillofacial Surgery, Peking University School and Hospital of Stomatology & National Center of Stomatology & National Clinical Research Center for Oral Diseases & National Engineering Research Center of Oral Biomaterials and Digital Medical Devices, Beijing, People's Republic of China.

Abstract:
Accurate perforator localization is critical for safe and efficient harvest of the anterolateral thigh perforator flap (ALTF) in head and neck reconstruction. This study evaluated the feasibility and accuracy of computed tomography angiography (CTA) with integrated mixed reality (CTA-MR) for perforator localization compared with hand-held Doppler ultrasound (HHD) and CTA-based digital guides (CTA-guide). Twelve patients requiring ALTF reconstruction following oral and maxillofacial tumour resection were enrolled. Each patient underwent preoperative perforator mapping using HHD, CTA-guide, and CTA-MR. The intraoperatively confirmed fascial emergence point of each perforator was used as the reference standard. Localization accuracy, sensitivity, distance error, preparation and localization times, and postoperative outcomes were analysed. Thirty-two perforators were confirmed intraoperatively. The accuracy of perforator localization was 75.7% for HHD, 85.3% for CTA-guide, and 91.2% for CTA-MR; sensitivity was 87.5%, 90.6%, and 96.9%, respectively. Localization error differed significantly among the three methods (linear mixed-effects model, P < 0.001). The estimated marginal mean localization error was 11.56 ± 0.94 mm for HHD (95% confidence interval (CI) 9.69-13.42), 8.01 ± 0.92 mm for CTA-guide (95% CI 6.18-9.84), and 5.82 ± 0.89 mm for CTA-MR (95% CI 4.05-7.59). CTA-MR required less preparation time than guide fabrication but a longer intraoperative localization time than guide placement. All flaps survived; no donor site complications were observed. CTA-MR appears to be a feasible method for ALTF perforator localization and demonstrated favourable localization performance in this exploratory cohort. Further studies are needed to confirm its clinical utility and potential advantages over established localization techniques.

