Related Experiment Video
Updated: Sep 11, 2026

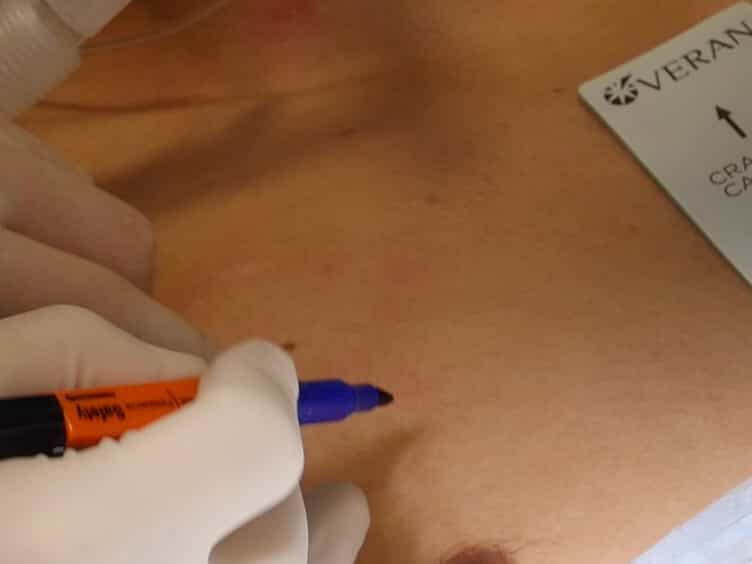
Electromagnetic Navigation Transthoracic Nodule Localization for Minimally Invasive Thoracic Surgery
Published on: May 4, 2022
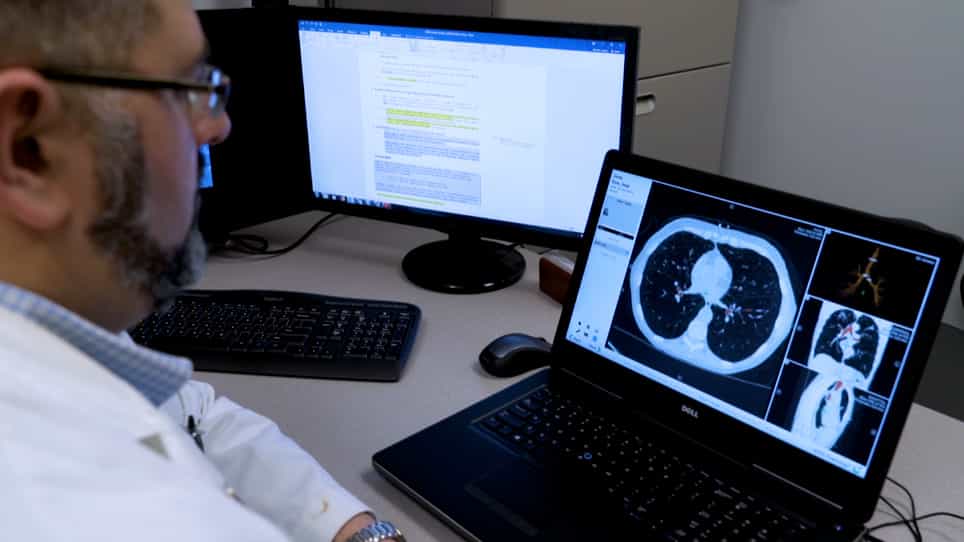
Mobile cone-beam computed tomography combined with electromagnetic navigation bronchoscopy for the diagnosis of
Lin Ye1,2,3, Siyuan Hong1,2,3, Xiaoxuan Zheng1,2,3
1Department of Respiratory Endoscopy, Shanghai Chest Hospital, Shanghai Jiao Tong University School of Medicine, Shanghai, China.

Background:
Electromagnetic navigation bronchoscopy (ENB) is widely used for diagnosing peripheral pulmonary nodules (PPNs), but its diagnostic yield remains variable. Mobile cone-beam computed tomography (mCBCT) enables intraprocedural assessment of the tool-lesion relationship and navigation correction; however, prospective data on its incremental clinical value remain limited.
Research Question:
Clinical value of mCBCT-guided navigation correction on the tool-lesion relationship and diagnostic yield during ENB for PPNs.
Study Design And Methods:
This prospective, single-centre, single-arm trial evaluated the diagnostic performance of mCBCT-assisted ENB for PPNs and the incremental clinical value of mCBCT-guided navigation correction. Intraoperative mCBCT assessed the tool-lesion relationship and guided correction before sampling. The primary endpoint was overall diagnostic yield after mCBCT assessment and adjustment. The key secondary endpoint was the tool-in-lesion improvement rate.
Results:
A total of 108 patients were enrolled. Median nodule size was 21.0 (IQR, 17.0-25.0) mm, and a CT 'bronchus sign' was present in 77.8%. Nodules were peripheral (47.2%), intermediate (33.3%), or central (19.4%) and solid (83.3%), mixed ground-glass opacities (13.9%), or pure ground-glass opacities (2.8%). The overall diagnostic yield was 79.6% (86/108). Navigation correction was required in 42.6% (46/108). Following mCBCT-guided navigation correction, the tool-in-lesion rate increased from 54.6% (59/108) to 87.0% (94/108), an absolute improvement of 32.4%. Procedure-related atelectasis was identified by mCBCT in 8 (7.4%) patients. No serious adverse events occurred.
Conclusion:
mCBCT-guided navigation correction improved the tool-lesion relationship and provided incremental clinical value beyond conventional ENB, particularly for smaller lesions and those without a CT bronchus sign, while maintaining an acceptable safety profile.