Related Experiment Video
Updated: Sep 12, 2026


Non-Invasive Compression-Induced Anterior Cruciate Ligament (ACL) Injury and In Vivo Imaging of Protease Activity in Mice
Published on: September 29, 2023
A Narrow Medial Femoral Condyle Width Is Associated With Anteromedial Rotatory Instability After Anterior Cruciate
Shengkun Wu1, Ruoxi Zhang1, Yu Liu1
1The Third Hospital of Hebei Medical University Shijiazhuang Hebei Province, China.

Purpose:
To identify bone morphological risk factors and injury patterns of medial structural injuries in patients with anteromedial rotatory instability (AMRI) after anterior cruciate ligament (ACL) injury.
Methods:
This comparative study analyzed patients' data between August 2024 and June 2025. ACL-deficient patients with combined injury of ligaments other than the medial collateral ligament or knee fracture were excluded. Patients aged 16 to 55 who were diagnosed with ACL rupture on magnetic resonance imaging and Kellgren-Lawrence grade < II on radiograph were included. All ACL injury patients were divided into 2 groups based on physical examination under anesthesia: 58 patients with a positive anterior drawer and Slocum test under anesthesia served as the AMRI group; 25 patients with a positive anterior drawer test but negative Slocum test under anesthesia served as the isolated ACL injury group (nonanteromedial rotatory instability [NAMRI] group). Preoperative magnetic resonance imaging was used to characterize bone morphological factors, including lateral femoral condyle ratio, medial femoral condyle width (MFCW), notch width, notch width index, coronal tibial slope, medial tibial depth, medial tibial posterior slope, and lateral tibial posterior slope. Medial structural injuries (superficial medial collateral ligament, deep medial collateral ligament [dMCL], and anteromedial retinaculum [AMR]) were assessed via ultrasound and magnetic resonance imaging. All patients did not experience postoperative infections or other surgical complications during at least 3 months of follow-up. During data analysis, t-tests were used to compare the differences between the mean values of various factors, 1-way analysis of variance was used to test the influence of each factor, and receiver operating characteristic (ROC) curves were used to test the predictive performance of MFCW.
Results:
The comparative study included 141 patients who were divided into 3 groups: AMRI (n = 58), ACL-injured patients without AMRI (NAMRI, n = 25), and isolated meniscus tear patients (control, n = 58). The AMRI group exhibited significantly smaller MFCW (AMRI: 6.72 ± 0.55 vs control: 7.35 ± 0.51, P < .001) and notch width (AMRI: 1.79 ± 0.29 vs control: 2.01 ± 0.37, P = .001), whereas significantly larger lateral femoral condyle ratio (AMRI: 0.672 ± 0.039 vs control: 0.644 ± 0.043, P = .001), medial tibial depth (AMRI: 0.36 ± 0.07 vs control: 0.31 ± 0.06, P < .001), and lateral tibial posterior slope (AMRI: 8.5 ± 2.6 vs control: 6.4 ± 2.9, P < .001) relative to the control group. The NAMRI group also showed significant differences, including larger lateral femoral condyle ratio (NAMRI: 0.668 ± 0.035 vs control: 0.644 ± 0.043, P = .048), lateral tibial posterior slope (NAMRI: 8.1 ± 2.3 vs control: 6.4 ± 2.9, P = .027), and medial tibial depth (NAMRI: 0.36 ± 0.08 vs control: 0.31 ± 0.06, P = .004) and smaller MFCW (NAMRI: 7.03 ± 0.37 vs control: 7.35 ± 0.51, P = .018), notch width (NAMRI: 1.73 ± 0.24 vs control: 2.01 ± 0.37, P = .001), and notch width index (NAMRI: 0.248 ± 0.035 vs control: 0.273 ± 0.044, P = .018) when compared with the control group. Critically, the AMRI group exhibited a smaller MFCW (NAMRI: 7.03 ± 0.37 vs AMRI: 6.72 ± 0.55, P = .033) relative to the NAMRI group, which represented a key factor in controlling anteromedial rotatory stability. Ultrasonography revealed a high prevalence of dMCL (89.7%) and AMR (63.8%) injuries in the AMRI group, and the combined injury of dMCL and AMR had the most frequent injury pattern. In addition, the ROC curve showed that MFCW showed a higher area under the ROC curve value in AMRI when compared with the control and NAMRI groups, respectively (area under the ROC curve: 0.791 AMRI vs control; 0.655 AMRI vs NAMRI).
Conclusions:
A smaller MFCW is associated with AMRI in patients with dMCL and AMR injuries compared with NAMRI patients. The injury pattern in AMRI is predominantly characterized by combined lesions of the ACL and dMCL + AMR.
Level Of Evidence:
Level IV, retrospective comparative case series.
Related Concept Videos
 01:16
Bones of the Lower Limb: Femur and Patella
 01:23
Knee Joint
A total of seven ligaments support the knee joint. The patellar ligament, which is also attached to the quadriceps femoris group...
 01:23
Muscles that Move the Leg
Anterior Compartment
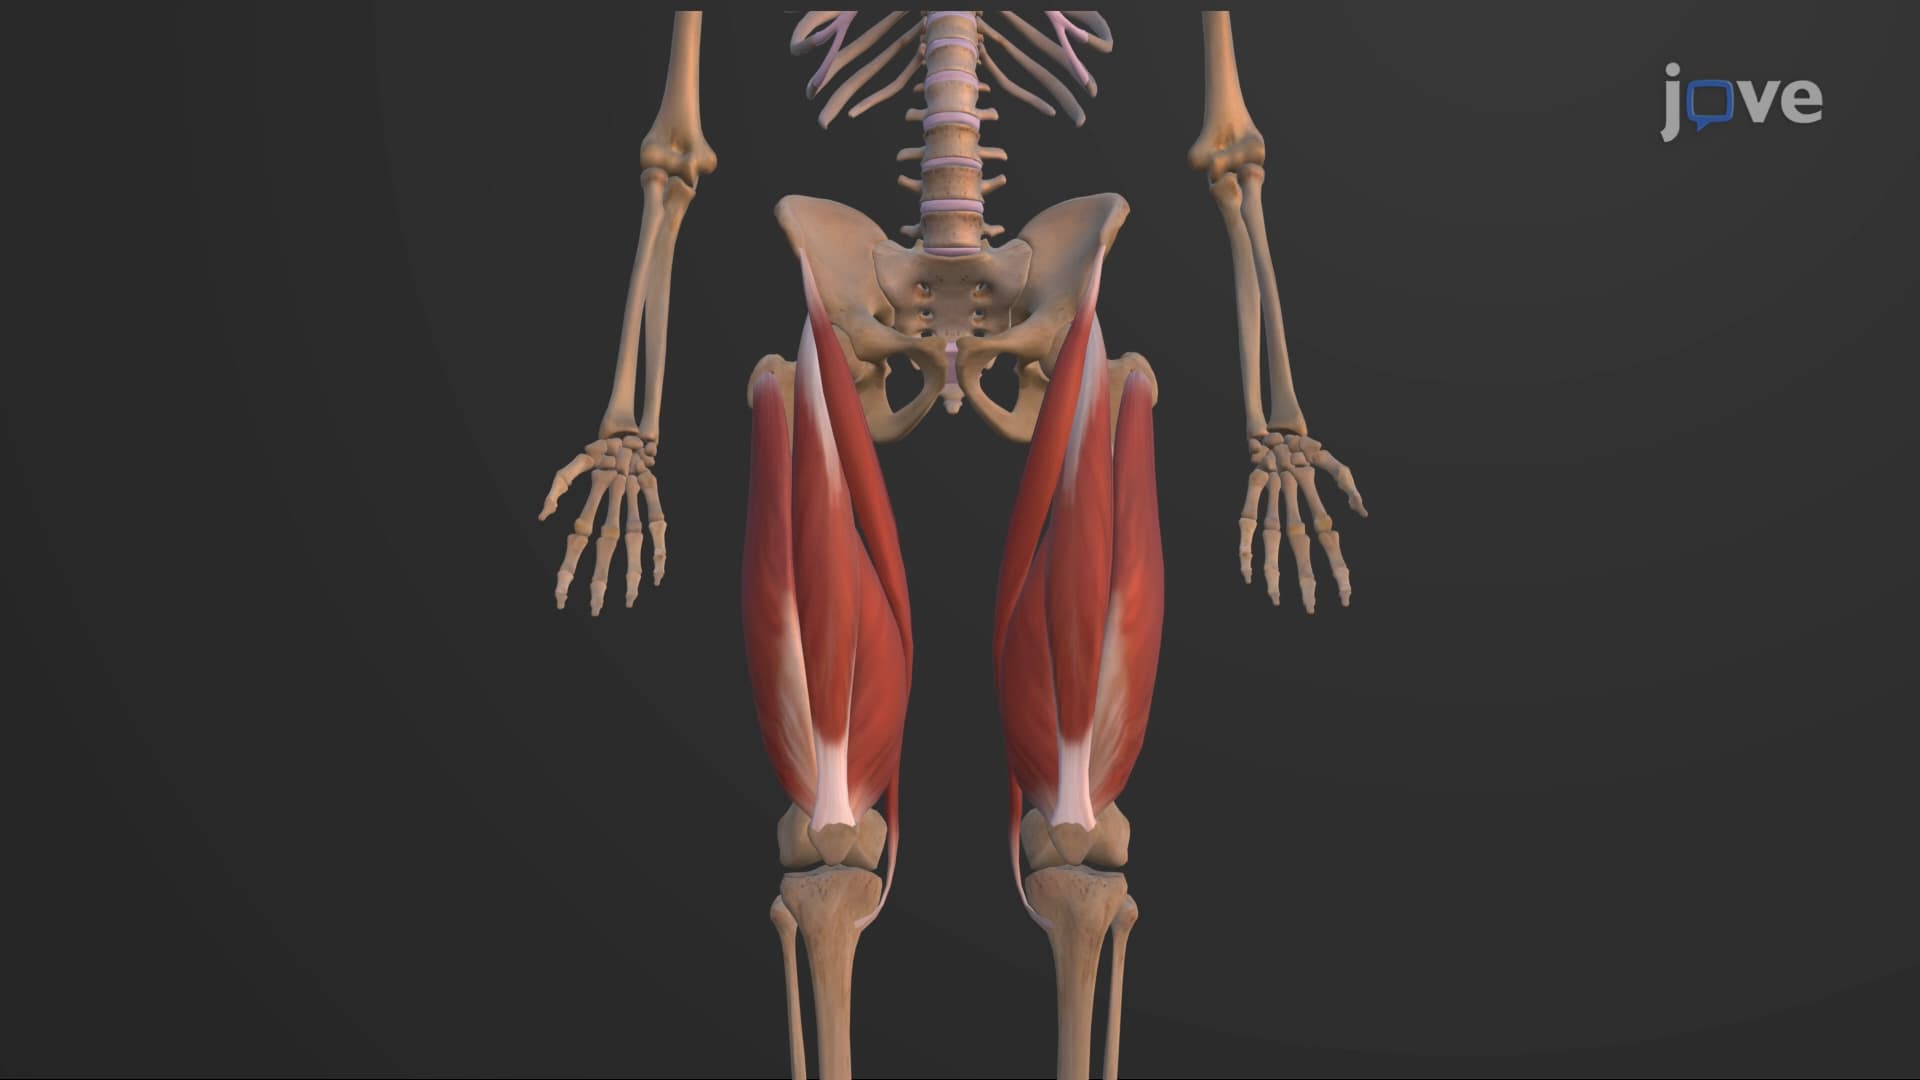
The quadriceps femoris, the most visible muscle of the anterior compartment, is integral for leg extension and thigh flexion. It is formed by merging four distinct muscles — the vastus lateralis, vastus medialis, vastus intermedius, and rectus femoris. The quadriceps tendon, a shared tendon of the four quadriceps muscles, is affixed to...
 01:10
Ankle Joint