Related Experiment Video
Updated: Sep 14, 2026
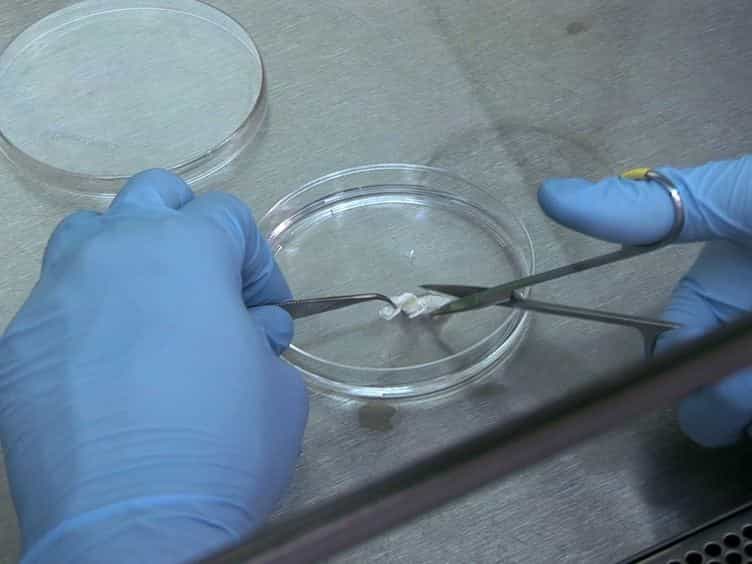

Surgical Retrieval, Isolation and In vitro Expansion of Human Anterior Cruciate Ligament-derived Cells for Tissue Engineering Applications
Published on: April 30, 2014
Anteromedial Femoral Tunnel Placement Reduces Graft Failure Risk Without Affecting Rotational Stability in Anatomic
Haitham Kamel Haroun1, Amr Mohamed Abdelhady1, Mohamed Abdallah Obied1
1Orthopedic Department Faculty of Medicine Ain Shams University Cairo Egypt.

Purpose:
To compare clinical outcomes and graft failure between anatomical femoral tunnel (FT) placement at the central and anteromedial bundle (AMB) positions.
Methods:
A systematic review was performed according to the Preferred Reporting Items for Systematic Reviews and Meta-Analyses guidelines. A search of PubMed, Cochrane, and Web of Science in November 2024 identified studies comparing AMB and central FT placement in anatomical single-bundle anterior cruciate ligament reconstruction. The risk of bias was assessed using the Risk Of Bias in Non-randomized Studies of Interventions tool. A qualitative synthesis was performed and presented graphically.
Results:
Six studies with 841 patients (444 AMB FT, 397 central FT) were included. Weighted mean follow-up was 34.8 and 40.7 months for the AMB and central groups, respectively. Overall risk of bias was serious in 4 studies and moderate in 2. AMB FT placement was associated with a significantly lower risk of graft failure (74%-77% reduction) in 2 studies. However, concerns in risk of bias and consistency decreased the certainty in this finding. Evidence for patient-reported outcomes and anterior stability was mixed and of uncertain clinical importance. Although some studies reported statistically significant benefits for AMB FT placement (differences of <7 points for patient-reported outcomes and <1 mm for anterior stability), others found no significant difference. Rotational laxity showed a nonsignificant difference between groups in all studies.
Conclusions:
The current evidence is limited by methodological flaws and risk of bias. It suggests that AM FT placement might be associated with a lower risk of graft failure compared with central placement. The AM position might achieve better patient-reported outcomes and anterior stability, although the difference is not clinically significant. No evidence of a difference was found regarding rotational stability.
Level Of Evidence:
Level III, systematic review of Level II and III studies.