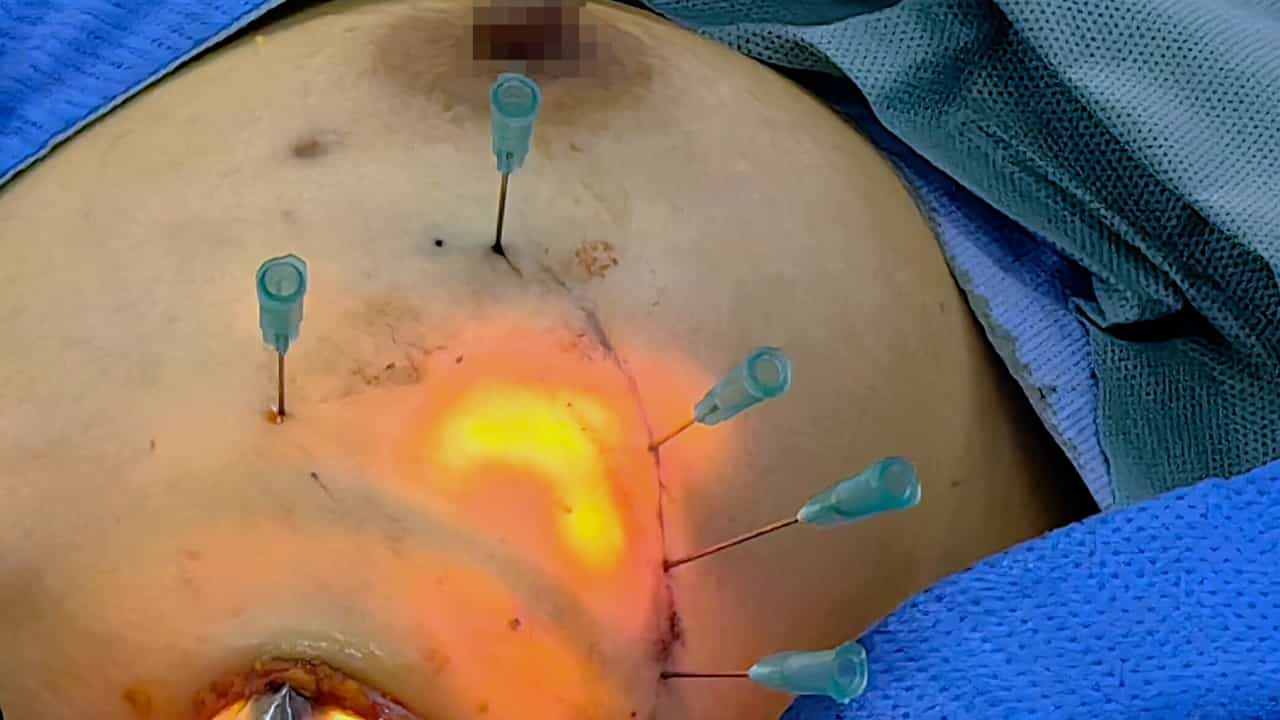
Related Experiment Video
Updated: Sep 13, 2026

Endoscopic Bilateral Nipple-sparing Mastectomy via a Single Axillary Incision with Immediate Pre-pectoral Implant-based Breast Reconstruction
Published on: May 17, 2024
Robotic nipple-sparing mastectomy after periareolar incision: a surgical technical approach to subareolar dissection
Toshikatsu Nitta1, Jun Okuno2, Kosei Kimura1,3
1Division of Surgery, Breast Center, Medico Shunju Shiroyama Hospital, Osaka, Japan.

Abstract:
Nipple-sparing mastectomy (NSM) after a prior periareolar incision is technically demanding because fibrosis, altered tissue planes, and possible vascular compromise around the nipple-areola complex (NAC) may increase the difficulty of subareolar dissection. Although robotic nipple-sparing mastectomy (R-NSM) has been reported as a minimally invasive option, its specific role in re-operative subareolar fields remains uncertain. This surgical technical report describes R-NSM performed with the da Vinci Xi system in a 51-year-old woman who previously underwent diagnostic lumpectomy through a periareolar incision for atypical ductal hyperplasia, followed by an indication for additional resection after ductal carcinoma in situ with microinvasion was identified. A 3.5-cm mid-axillary incision was used for access with a GelPOINT Mini platform. The key technical elements were lateral access without reopening the periareolar incision, low-pressure CO2 insufflation, hydrodissection, maintenance of uniform flap thickness, limited use of bipolar energy, and cold scissors dissection immediately beneath the NAC under magnified three-dimensional visualization. The retroareolar margin was confirmed intraoperatively by frozen section. The total operative time was 248 min, and console time was 71 min. No intraoperative complications occurred. The postoperative course was uneventful, the patient was discharged on postoperative day 7, no nipple or skin necrosis was observed, and final surgical margins were negative. This case suggests that R-NSM may facilitate controlled subareolar dissection in selected patients with prior periareolar surgery. However, this single-case report does not demonstrate superiority over open or endoscopic approaches, and the absence of objective perfusion assessment precludes conclusions regarding NAC vascular preservation.