Related Experiment Video
Updated: Sep 14, 2026
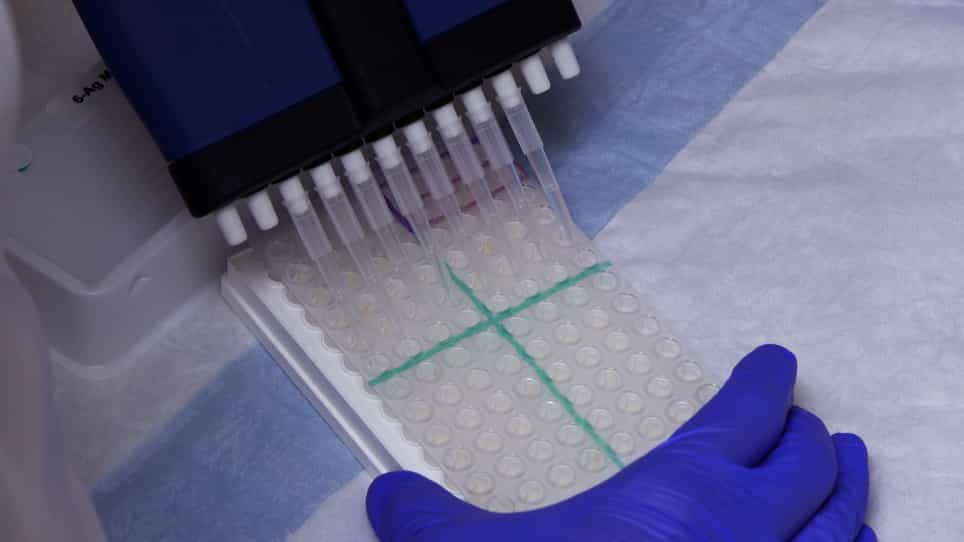

A High-Throughput Multiplexed Screening for Type 1 Diabetes, Celiac Diseases, and COVID-19
Published on: July 5, 2022
From ADA positivity to clinical decision: a context-of-use framework for reflex testing, sampling frequency and
Ahmad Z Al Meslamani1, Anan S Jarab2, Husam El Sharu3
1College of Pharmacy, Al Ain University, Abu Dhabi, United Arab Emirates.

Abstract:
The clinical meaning of anti-drug antibody (ADA) positivity in biologic development, depends on context rather than incidence alone. This narrative review synthesizes regulatory guidance, consensus recommendations, bioanalytical literature, and selected clinical evidence published from January 2015 to mid-May 2026. It proposes a context-of-use framework for immunogenicity assessment. ADA testing should be designed around decisions it is expected to support, including pharmacokinetics/, pharmacodynamics (PK/PD) interpretation, efficacy, safety, labeling, dose selection, treatment interruption, and development progression. Product, patient, trial, and assay inform high-, moderate-, and low-consequence settings. Baseline, on-treatment, post-treatment, and event-based sampling times tailored to the compound's half-life, the drug's assay tolerance, exposure-response time windows, and safety risk. Confirmed ADA should reflex to titer, neutralizing antibody, domain-specific, cross-reactivity, or isotype tests. If there are archived samples, supervision, and established criteria for restarting testing, stopping or de-escalating testing may be considered after adequate exposure, suitable assays, and no apparent signal associated with ADA.

