Related Experiment Video
Updated: Sep 16, 2026
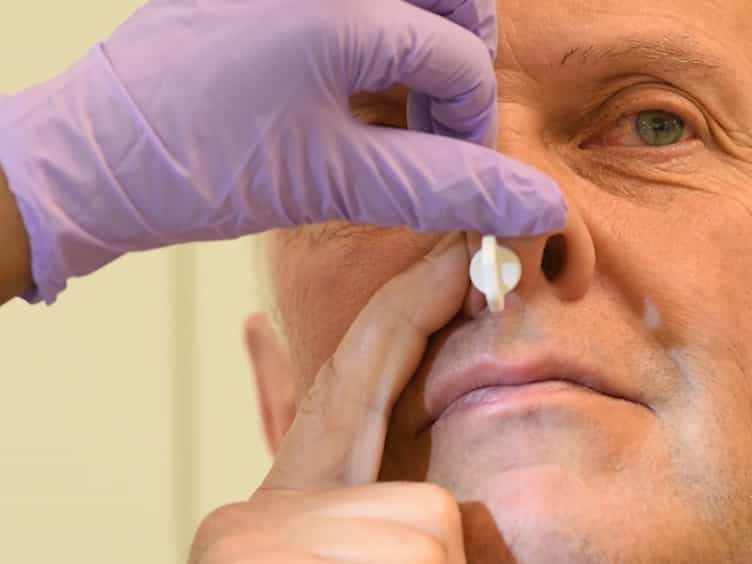

Absorption of Nasal and Bronchial Fluids: Precision Sampling of the Human Respiratory Mucosa and Laboratory Processing of Samples
Published on: January 21, 2018
Understanding Nasal Polyposis: The Roles of Ion Channels, Inflammation, Ionocytes, and Prostaglandin E2-The I3PGE2
César Picado1,2, Jordi Roca-Ferrer2,3
1Faculty of Medicine and Health Sciences, University of Barcelona, 08036 Barcelona, Spain.

Abstract:
Nasal polyposis is a multifactorial disorder arising from complex interactions among cellular, molecular, and inflammatory mechanisms. The Cystic Fibrosis Transmembrane Conductance Regulator (CFTR) and other ion channels are essential for epithelial ion transport, mucosal hydration, and barrier integrity in the nasal airway. Prostaglandin E2 (PGE2) acts not only as an inflammatory mediator but also as a regulator of ion exchange through CFTR-dependent and CFTR-independent pathways. Ionocytes, specialized epithelial cells that regulate ion balance and fluid secretion in the respiratory tract, are closely associated with CFTR function. Both eosinophilic and non-eosinophilic inflammation may alter ionocyte abundance and function, thereby reducing normal CFTR activity. Chronic rhinosinusitis with nasal polyps (CRSwNP) is also characterized by diminished PGE2 production. The I3PGE2 hypothesis proposes that CRSwNP results from the combined effects of ion channel dysfunction, persistent inflammation, altered ionocyte number and function, and impaired PGE2 synthesis. Together, these abnormalities disrupt nasal physiology and promote polyp formation. We hypothesize that corticosteroids and biologic therapies may improve CRSwNP by reducing inflammation, restoring ion channel activity, improving ionocyte function, and recovering PGE2 production. These effects enhance hydration and mucociliary clearance, limit mucus accumulation, restore epithelial homeostasis and mucosal host defense, and ultimately contribute to the reduction or resolution of nasal polyps.
Related Concept Videos
 01:24
Pathophysiology of Peptic Ulcer Disease: Mucosal Defense Factors
 01:22
Pathophysiology of Peptic Ulcer Disease: Injurious Factors
In the antrum region, G cells secrete the gastrin hormone that binds to gastrin-cholecystokinin-B (CCK2) receptors on parietal and enterochromaffin-like (ECL) cells in the fundic glands. Simultaneously, the vagus nerve releases acetylcholine, which binds to M3...
 01:17
Gastritis-II: Pathophysiology
In acute gastritis, the gastric mucosa becomes swollen and red and undergoes superficial erosion. Superficial ulceration may lead to bleeding.
In chronic gastritis, persistent or repeated insults lead to chronic inflammatory changes and, eventually, thinning or atrophy of the gastric tissue.
Gastritis can stem from various causes, each...
 01:24
Peptic Ulcer Disease II: Pathophysiology
 01:28
Peptic Ulcer Disease II: Pathophysiology
Damaging agents such as Helicobacter pylori, gastric acid, pepsin, and nonsteroidal anti-inflammatory drugs (NSAIDs) can weaken the mucosal defense, allowing hydrogen ions to infiltrate back and harm epithelial cells.
 01:20
Drugs for Peptic Ulcer Disease: Prostaglandin Analogs as Mucosal Protective Agents
Non-steroidal anti-inflammatory drugs (NSAIDs) can induce peptic ulcers by inhibiting cyclooxygenase, decreasing...