Related Experiment Video
Updated: Sep 17, 2026


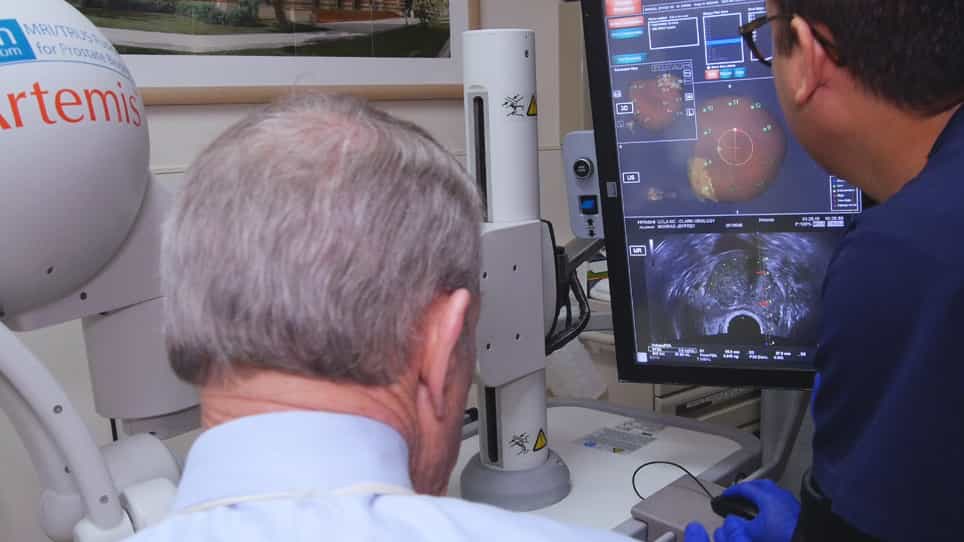
A Cognitive Fusion-guided Prostate Biopsy Using Multiparametric Magnetic Resonance Imaging and Transrectal Ultrasound
Published on: March 21, 2025
Diagnostic performance of AI-powered prostate MRI against biopsy ground truth: quasi-continuous risk scoring versus
Nadine Bayerl1, Joel Appel2, Maximilian Schmidt2
1Institute of Radiology, Friedrich-Alexander-Universität Erlangen-Nürnberg and Uniklinikum Erlangen, Maximiliansplatz 3, 91054, Erlangen, Germany. nadine.bayerl@fau.de.

Background:
Multiparametric prostate MRI is central to prostate cancer (PCa) diagnostics, yet PI-RADS interpretation suffers from inter-reader variability. This study aimed to evaluate a commercial AI algorithm for cancer detection in prostate MRI against histopathology, comparing its standard PI-RADS classification with its quasi-continuous Level-of-Suspicion (LoS) score as decision variables.
Methods:
In this retrospective single-center study, 122 mpMRI examinations, each followed by systematic and/or fusion-targeted biopsy, were analyzed. Histopathology served as the reference standard for any PCa (Gleason ≥ 6) and clinically significant PCa (csPCa; Gleason ≥ 7). Diagnostic performance of the algorithm's PI-RADS and LoS outputs was assessed by ROC analysis. AUCs were compared using DeLong's test. The Youden-optimal LoS cutoff was determined, its optimism was quantified by bootstrap internal validation, and the calibration of the LoS score was assessed after logistic recalibration.
Results:
For csPCa, PI-RADS yielded an AUC of 0.833 (95% CI: 0.764-0.901), versus 0.882 (95% CI: 0.820-0.943) for the LoS score (p = 0.106). At PI-RADS ≥ 4, sensitivity was 94.7% and specificity 63.1%. The Youden-optimal LoS cutoff was 81. At this exploratory threshold, sensitivity remained 94.7% while specificity was 70.8%, with positive and negative predictive values of 74.0% and 93.9%, respectively. Bootstrap internal validation indicated modest optimism, with corrected estimates of 92.9% for sensitivity and 69.1% for specificity. After logistic recalibration, the bootstrap-corrected calibration slope was 0.98 with an intercept of -0.01.
Conclusion:
In this retrospective single-center cohort, the AI algorithm achieved high diagnostic accuracy for csPCa. Its quasi-continuous LoS score provided an operating point combining high sensitivity with numerically higher specificity than the PI-RADS ≥ 4 threshold. Neither this difference (exact McNemar p = 0.063) nor the difference in AUC between the two classifiers (p = 0.106) reached statistical significance, so the finding should be regarded as a promising trend rather than a demonstrated advantage. Prospective confirmation is required before AI-assisted standardized interpretation is integrated into prostate MRI workflows on this basis.