Related Experiment Video
Updated: Sep 18, 2026

Pedicle Screw Placement Using an Augmented Reality Head-Mounted Display in a Porcine Model
Published on: May 24, 2024
Integrating mixed reality navigation in spine surgery: experience from a national spinal injuries unit and
Dave M Moore1, Jake McDonnell2, Katherine Egan2
1National Spinal Injuries Unit, Mater Misericordiae Hospital, Dublin, Ireland. davidmmoore@rcsi.ie.

Objectives:
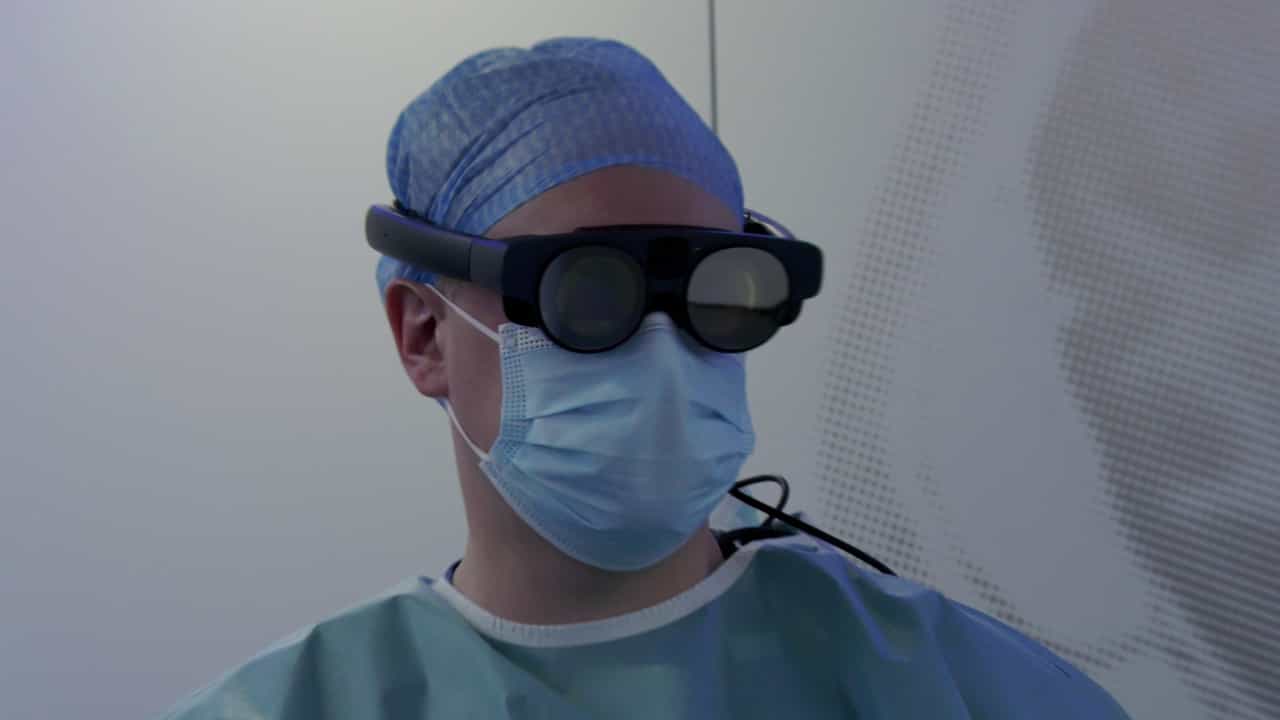
Mixed Reality (MR) navigation is an emerging technology that overlays three-dimensional anatomical reconstructions into the surgeon's operative field. This study presents the first-in-world case series describing the clinical application, workflow integration, and logistical-economic considerations of the Brainlab Spine Mixed Reality Navigation System in spinal surgery.
Setting:
National Spinal Injuries Unit, Dublin, Ireland.
Methods:
A retrospective review was performed of prospectively collected demographic and operative data from all spinal procedures using the Brainlab MR navigation platform at a national spinal injuries unit between September 2024 and March 2025. Fifteen patients (9 female, 6 male; mean Accepted manuscript age 57 years, range 18-76 years) underwent posterior spinal procedures, including trauma, degenerative, oncologic, and deformity cases. Operative approach, levels fused, use of minimally ACCEPTED MANUSCRIPT invasive techniques, setup time, and intraoperative workflow integration were documented. Postoperative imaging was reviewed for hardware placement and alignment.
Results:
The MR platform was implemented in six trauma cases, five degenerative pathologies, three oncologic resections, and one deformity correction. Four procedures (27%) used percutaneous techniques. The mean number of levels fused was 2.9 (range 1-8). All cases were posterior approaches with the patient prone. The MR system added approximately 3-5 minutes for registration, with headset re-registration required in three cases, resolved without significant delay. No intraoperative complications were attributable to MR use. Postoperative imaging confirmed correct hardware positioning and satisfactory alignment in all patients. Surgeons reported particular benefit in percutaneous stabilisations and tumour resections due to continuous 3D anatomical overlays. The 3-year cost for a dual-headset system was €59,660, with no ongoing per-case consumable costs.
Conclusion:
This initial institutional experience demonstrates the feasibility and safety of MR navigation across a diverse posterior spinal case mix. The system integrates efficiently into existing workflows, enhances spatial awareness, and may offer particular value in minimally invasive and tumour cases. Further prospective, comparative studies are required to validate clinical outcomes, cost-effectiveness, and broader adoption potential.