Related Experiment Video
Updated: Sep 19, 2026


Imaging Features of Systemic Sclerosis-Associated Interstitial Lung Disease
Published on: June 16, 2020
Bilateral Bloody Pleural Effusions With Discordant Cellular Patterns: A Case of Concurrent Parapneumonic Effusion and
Yoshitsugu Narumi1, Susumu Hoshino1, Midori Yamakawa1
1Department of Internal Medicine and Pulmonary Medicine Seikei-kai Chiba Medical Center Chiba Japan.

Abstract:
Bilateral pleural effusions typically suggest systemic aetiologies; however, concurrent distinct localised pathologies are rare. A 73-year-old man presented with fever and cough. Chest imaging revealed pneumonia and bilateral pleural effusions developed during antibiotic treatment. The right effusion was neutrophil-dominant, consistent with parapneumonic effusion, while the left was lymphocyte-dominant, suggesting Dressler syndrome triggered by pneumonia-induced systemic inflammation. Both effusions were bloody, an appearance possibly exacerbated by the concomitant use of a direct oral anticoagulant and aspirin. The left effusion recurred months later but significantly improved following ibuprofen treatment, supporting an immune-mediated aetiology. This case highlights that bilateral effusions can arise from different aetiologies and that pneumonia-induced inflammation may trigger a latent immune response related to prior cardiac surgery.
Related Concept Videos
 01:28
Pleural Effusion II: Symptoms and Management
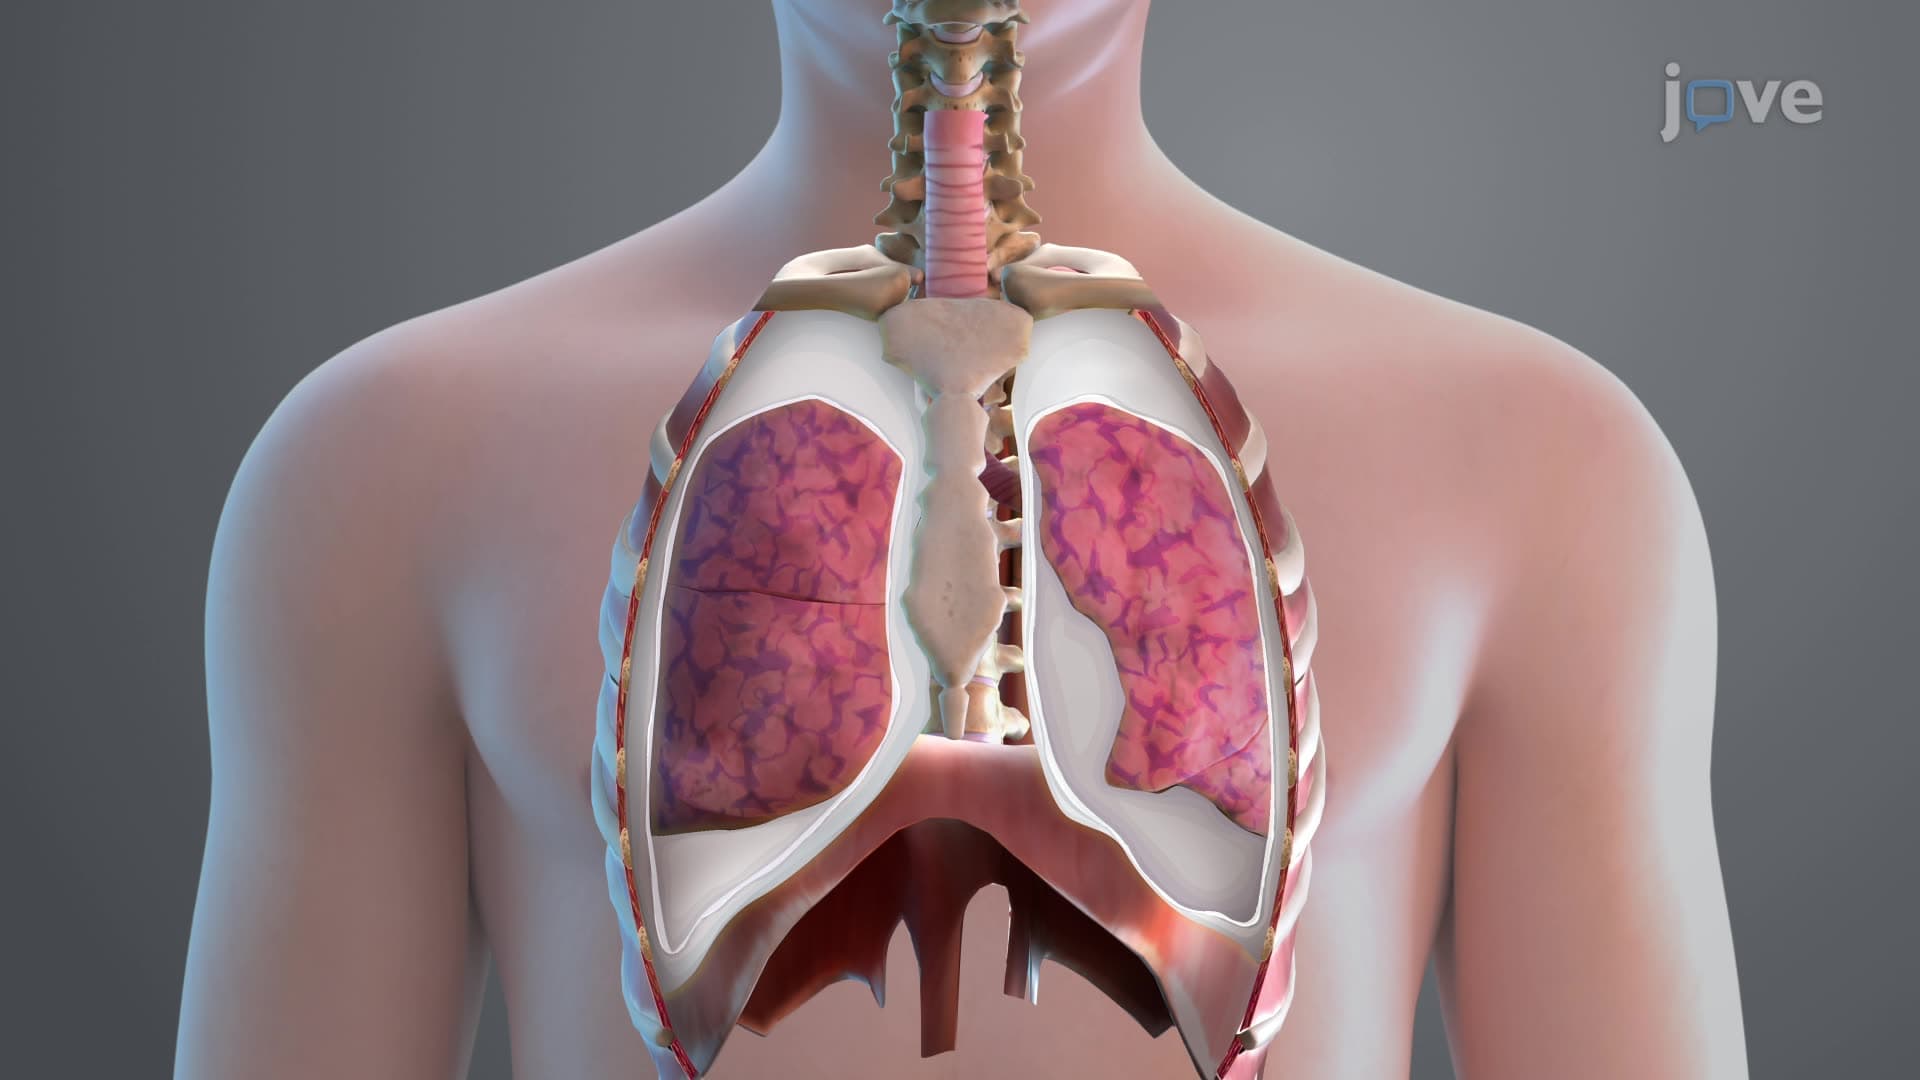
A pleural effusion is the abnormal collection of fluid between the parietal and visceral pleura layers of tissue that form the lining of the lungs and chest cavity. It can occur independently or due to surrounding parenchymal diseases, such as infection, malignancy, or inflammatory conditions.
Clinical Manifestations:
 01:25
Pleural Effusion I: Introduction
There are two main types of pleural effusion: transudative and exudative. They are differentiated using Light's criteria,...
 01:30
Pleural Disorders: Types and Brief Description
 01:13
Pleura of the Lungs
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:29
Pneumonia II: Pathophysiology