Related Experiment Video
Updated: Sep 19, 2026


A Novel Digital Platform for a Monitored Home-based Cardiac Rehabilitation Program
Published on: April 19, 2019
Exercise-based cardiac rehabilitation for coronary heart disease
Grace Dibben1, Frederique Bg de Vries2, James Faulkner3
1School of Health & Wellbeing, University of Glasgow, Glasgow, UK.

Rationale:
Coronary heart disease (CHD) is the leading cause of death globally. CHD mortality rates remain steady in low- and middle-income countries but are declining in high-income countries, meaning more people are living with CHD and need support to manage their symptoms and prognosis. Exercise-based cardiac rehabilitation (CR) aims to improve the health outcomes of people with CHD.
Objectives:
To assess the clinical and cost-effectiveness of exercise-based CR (exercise training alone or combined with psychosocial/educational interventions) compared with 'no exercise' control, on mortality, morbidity and health-related quality of life (HRQoL) in people with CHD.
Search Methods:
We updated searches from the previous Cochrane review, searching CENTRAL, MEDLINE, Embase, Web of Science, CINAHL, and two clinical trials registers in March 2026.
Eligibility Criteria:
We included randomised controlled trials (RCTs) of exercise-based CR, compared with 'no exercise' control, with follow-up of six months or longer, in adults with CHD.
Outcomes:
Primary outcomes included mortality (all-cause and cardiovascular), fatal and non-fatal myocardial infarction (MI), revascularisation (coronary artery bypass graft (CABG) and percutaneous coronary intervention (PCI)), and hospitalisation (all-cause and cardiovascular). Secondary outcomes included HRQoL and cost-effectiveness. We categorised follow-up as short-term (6 to 12 months), medium-term (> 12 to 36 months), and long-term (> 36 months).
Risk Of Bias:
We assessed risk of bias with the Cochrane Risk of bias 1 tool (RoB 1).
Synthesis Methods:
We synthesised results for each outcome using meta-analysis where possible, using random-effects models to calculate risk ratios (RR) and 95% confidence intervals (CI) for dichotomous outcomes, and mean differences (MD) for continuous outcomes. We stratified meta-analyses by follow-up duration and used univariable meta-regression to explore potential sources of between-study heterogeneity. Where meta-analysis was not possible, we narratively synthesised results. We used GRADE to assess certainty of evidence for primary outcomes at short-term follow-up (the most common time point).
Included Studies:
This review included 107 trials (26,886 adults with CHD). This update identified 22 new trials (3456 participants). Most participants were post-MI or post-revascularisation; their mean age ranged from 47 to 81 years. Although 78% of trials included women, they represented only 17% of the participants overall. Most trials were conducted in high-income settings in Europe (51/107, 48%), Asia (28/107, 26%) and North America (14/107, 13%). Twenty-six trials (11 in this update) were undertaken in low- and middle-income countries (LMICs). Overall, trial reporting was poor, although there was evidence of an improvement in quality over the last decade.
Synthesis Of Results:
Short-term follow-up (6 to 12 months) Compared to no structured exercise, exercise-based CR likely reduces all-cause mortality (RR 0.86, 95% CI 0.74 to 1.00; 30 trials, 10,391 participants; number needed to treat for an additional beneficial outcome (NNTB) 125, 95% CI 75 to ∞; moderate-certainty evidence) and may reduce cardiovascular mortality (RR 0.87, 95% CI 0.68 to 1.11; 20 trials, 7277 participants; NNTB 200, 95% CI 82 to number needed for an additional harmful outcome (NNTH) 238; moderate-certainty evidence). It results in a large reduction in MI (RR 0.72, 95% CI 0.54 to 0.95; 25 trials, 8584 participants; NNTB 71, 95% CI 47 to 435; high-certainty evidence). It makes little to no difference in risk of CABG (RR 1.00, 95% CI 0.78 to 1.28; 21 trials, 4532 participants; high-certainty evidence), and likely little to no difference in PCI (RR 0.86, 95% CI 0.65 to 1.13; 13 trials, 3465 participants; moderate-certainty evidence). It likely reduces all-cause hospital admissions (RR 0.65, 95% CI 0.51 to 0.82; 21 trials, 3868 participants; NNTB 17, 95% CI 12 to 32; moderate-certainty evidence) but we are uncertain about its effects on cardiovascular hospitalisation (RR 0.80, 95% CI 0.35 to 1.82; 6 trials, 1550 participants; low-certainty evidence), with substantial heterogeneity (I2 = 59%). We detected small-study bias for all-cause hospitalisation, but not for other outcomes. Evidence indicated clinically meaningful increases in HRQoL with exercise-based CR across several outcome domains, including SF-36 subscales (physical component, mental component, physical functioning, physical performance, general health, vitality, and social functioning scores) and EQ-5D scores up to 12 months' follow-up. Eight economic evaluation studies consistently showed exercise-based CR to be cost-effective in terms of quality-adjusted life years gained. Meta-regression showed that most study-level characteristics did not explain heterogeneity, though some variation was seen by intervention setting and study sample size. Certainty of evidence ranged from low to high. We downgraded due to imprecision (wide 95% CIs), possible publication bias, and heterogeneity across studies. We judged several studies at high risk of bias in some domains, primarily due to incomplete reporting or study-level attrition. For clinical outcomes, we considered that the impact of this risk of bias on effect estimates was limited. Around a quarter of included trials were conducted in earlier eras of cardiac care, prior to the widespread adoption of contemporary optimal medical therapy.
Authors' Conclusions:
Compared with no exercise, exercise-based CR improves outcomes for people with CHD, including significantly reduced risk of MI and hospitalisation, a likely small reduction in all-cause and cardiovascular mortality, and improved HRQoL up to 12 months' follow-up. Over longer-term follow-up (> 12-months), exercise-based CR is associated with reduced cardiovascular mortality and MI. CR for people with CHD was also shown to be cost-effective. Recent trials have increased inclusion of women, used alternative models of CR delivery (home and digitally supported) and have been undertaken in LMICs, increasing the global generalisability of findings.
Funding:
Internal sources: University of Glasgow, UK - funding support for the time of GD and RST. Radboud University Medical Centre, NL - funding support for the time of FdV, DT and NS. External sources: past NIHR Cochrane Infrastructure funding to Cochrane Heart. The views and opinions expressed therein are those of the authors and do not necessarily reflect those of the Systematic Reviews Programme, NIHR, NHS or the Department of Health and Social Care.
Registration:
Previous versions available via doi.org/10.1002/14651858.CD001800.pub4; doi.org/10.1002/14651858.CD001800.pub3; doi.org/10.1002/14651858.CD001800.pub2; doi.org/10.1002/14651858.CD001800; DOI 10.1016/j.amjmed.2004.01.009.

Related Concept Videos
 01:20
Exercise and Cardiovascular Response
Light to moderate physical activity initiates a series of interconnected responses in the body. The heart rate modestly increases in anticipation of the workout, followed by widespread vasodilation as oxygen consumption by skeletal muscles increases. This results in decreased peripheral resistance, increased capillary blood flow, and accelerated...
 01:17
Exercise and Cardiac Output
Sustained exercise increases the muscles' oxygen demand, which can be met...
 01:26
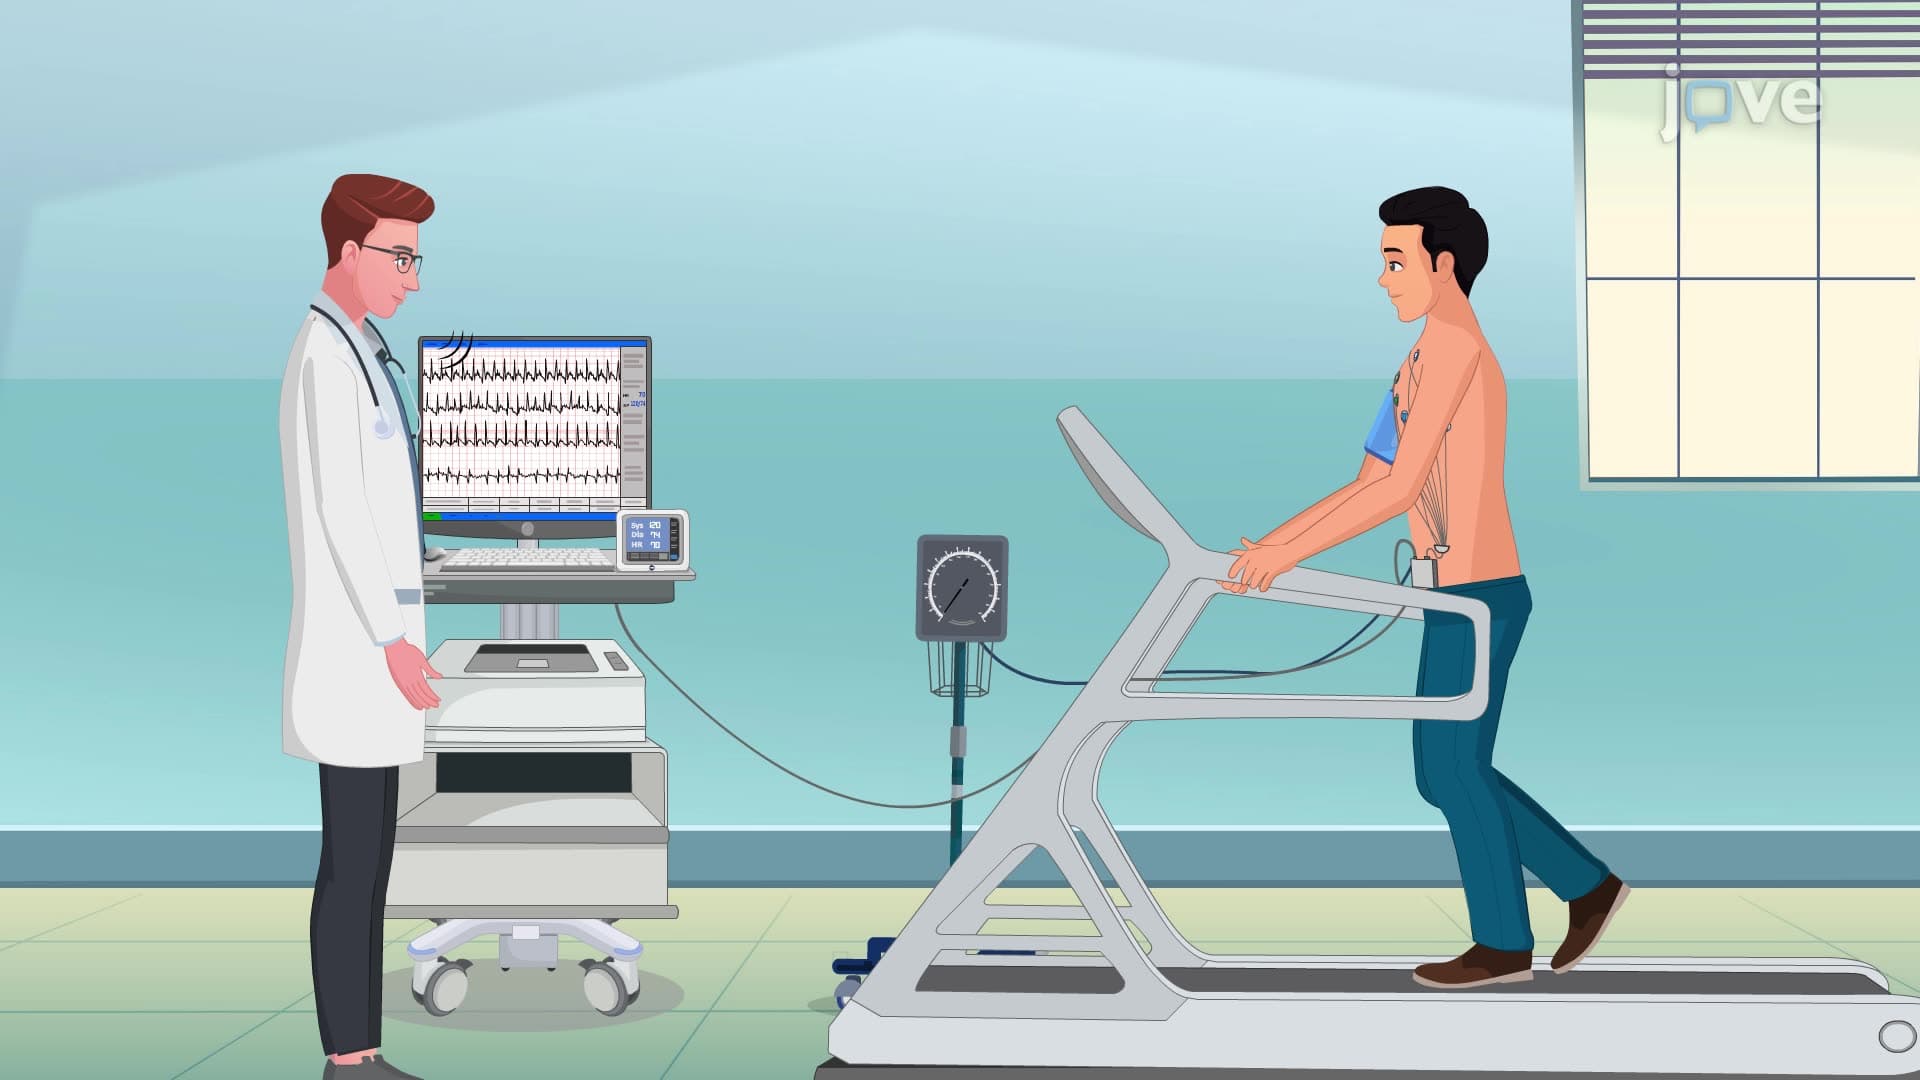
Exercise Stress Test
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes
 01:27
Coronary Artery Disease V: Interprofessional Care
 01:29
Cardiomyopathy V: Interprofessional Care
 01:26
Coronary Artery Disease IV: Preventive Measures