Related Experiment Video
Updated: Sep 20, 2026
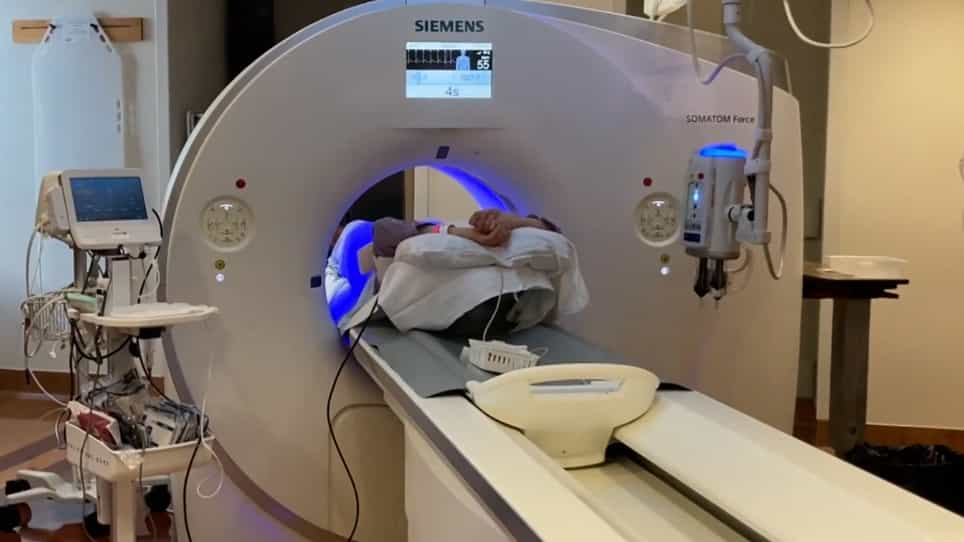

Time-Resolved, Dynamic Computed Tomography Angiography for Characterization of Aortic Endoleaks and Treatment Guidance via 2D-3D Fusion-Imaging
Published on: December 9, 2021
Comprehensive Artificial Intelligence Based Analysis of Pre- and Post-operative Computed Tomography Scans in Patients
Juan Garrido-Oliver1, Xavier Tenezaca-Sari2, Tiago Ribeiro3
1Vall d'Hebron Institut de Recerca, Barcelona, Spain; Department of Medicine, Universitat Autònoma de Barcelona, Bellaterra, Spain.

Objective:
Endovascular aortic repair (EVAR) requires lifelong imaging surveillance to monitor potential complications such as endoleaks (EL) or aneurysm growth. This study aimed to develop and validate a comprehensive artificial intelligence (AI) pipeline for analysing pre- and post-EVAR contrast enhanced computed tomography angiographies (CTAs) in abdominal aortic aneurysm (AAA) patients.
Methods:
Consecutive patients who underwent elective EVAR with available pre- and post-EVAR CTA were retrospectively identified at two independent centres. Four convolutional neural networks (nnU-Net) were developed to automatically identify pre-EVAR (lumen, thrombus, six anatomical landmarks) and post-EVAR CTAs (lumen, excluded aorta, six anatomical and three prosthetic landmarks) and to detect EL. Maximum AAA diameter and its progression during follow up were automatically extracted and compared with manual annotations across experts and protocols. Data from the internal centre were used to train and validate the models, while data from the external centre served for external validation.
Results:
A total of 372 patients (1 133 CT scans) were included: 135 patients (295 CTAs) for model development and 237 (838 CTAs) for external validation. Overall, age was 74 [69 - 79] years; 15 were female (4%), follow up was 8.1 [3.1, 27.9] months, pre-EVAR maximum AAA diameter was 59 [55, 68] mm, and 150 patients developed an EL during follow up. All AI segmentations were excellent (all Dice scores > 0.9) and landmarks were accurately identified, with errors comparable with the interobserver variability. EL detection achieved an area under the curve of 0.87 and 0.85 in the internal and external cohorts, respectively. Differences between AI derived and manual maximum AAA diameters were minor (median error ≤ 2 mm), with excellent correlations across centres (all R ≥ 0.97, p < .001; intraclass correlation ≥ 0.97). Disagreement in follow up diameter change between AI and manual measurements was lower than the interobserver variability.
Conclusion:
The AI based pipeline enabled accurate, generalisable, and explainable assessment of AAA patients, including both pre-EVAR evaluation and post-EVAR follow up.
Related Concept Videos
 01:22
Aneurysm IV: Nursing Management
 01:26
Aneurysm III: Interprofessional Care
 01:28
Imaging Studies for Cardiovascular System V: CT