Related Experiment Video
Updated: Sep 24, 2026

Intense Pulsed Light for the Treatment of Dry Eye Owing to Meibomian Gland Dysfunction
Published on: April 1, 2019
Repeatability and Reproducibility of the Dry Eye Analyzer in Participants With and Without Symptoms of Dry Eye
Reut Ifrah1, Efrat Netanya2,3
1Department of Optometry and Vision Science, Jerusalem Multidisciplinary College, Jerusalem, Israel. reutif@edu.jmc.ac.il.

Purpose:
Reliable evaluation and consistency between examiners and sessions are essential for dry eye diagnosis. This study examined the inter-examiner reproducibility (IER), inter-session repeatability (ISR) and within-subject variability (WSV) of the Dry Eye Analyzer (DEA) in participants with and without dry eye symptoms.
Methods:
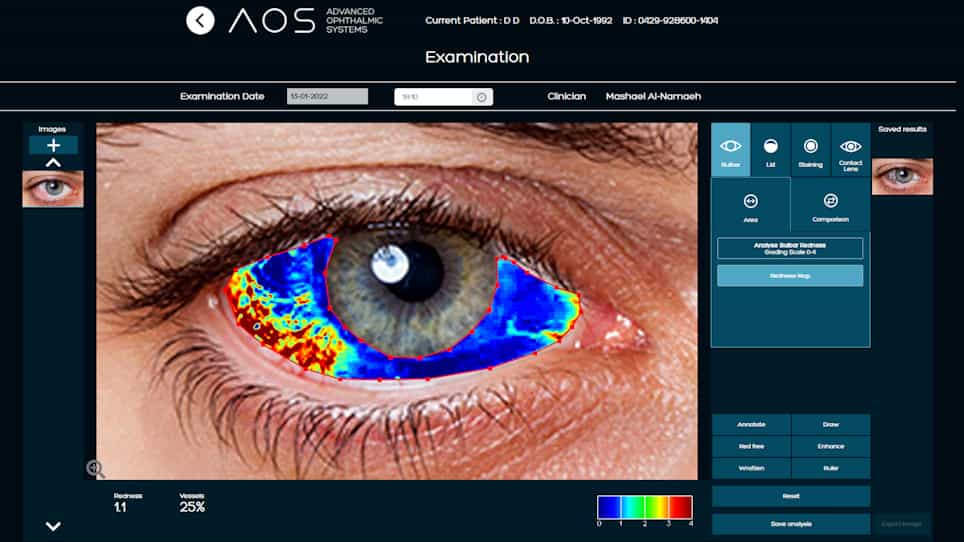
Participants with Dry Eye Questionnaire-5 (DEQ-5) scores ≥6 were classified as symptomatic. Non-invasive tear breakup time (NITBUT), Meibomian gland (MG) loss, tear meniscus height (TMH), interferometry and conjunctival redness were measured by two examiners on the same day for IER. Examiner 1 repeated measurements 1-2 weeks later for ISR. Analyses included Wilcoxon tests, Spearman correlation, weighted kappa (κw), within-subject standard deviation (Sw), repeatability limits (2.77Sw), intraclass correlation coefficients (ICCs) and Bland-Altman analysis.
Results:
IER included 84 participants (mean age 23 ± 2 years, range 18-34 years; 42 symptomatic). Examiner 1/Examiner 2 values were 7.2 ± 3.2/8.9 ± 3.0 s for NITBUT, 20.4 ± 7.4/20.4 ± 7.0% for upper MG loss, 27.2 ± 14.0/26.6 ± 14.0% for lower MG loss and 0.2 ± 0.0/0.2 ± 0.1 mm for TMH. Outcomes were positively correlated without significant differences for most comparisons; NITBUT differed significantly overall and in symptomatic participants. Agreement ranged from fair to good (κw 0.30-0.63), ICCs from 0.51 to 0.99 and Sw was <3.40. Mean NITBUT bias was -1.68 s overall and -2.90 s in symptomatic participants; 93-98% of observations fell within the limits of agreement. ISR included 68 participants (mean age 23 ± 2 years, range 18-32; 36 symptomatic). Session 1/Session 2 values were 7.1 ± 3.2/6.8 ± 3.1 s for NITBUT, 20.7 ± 7.4/20.7 ± 8.1% for upper MG loss, 27.0 ± 14.6/26.9 ± 13.9% for lower MG loss and 0.2 ± 0.0/0.2 ± 0.0 mm for TMH. Outcomes were positively correlated without significant differences. Agreement ranged from fair to very good (κw 0.28-1.00), with Sw < 3.14.
Conclusions:
DEA reliability was parameter-dependent. MG-loss measurements showed excellent IER and low WSV, whereas NITBUT showed moderate reliability and examiner-related bias. NITBUT and TMH should be interpreted cautiously during follow-up.