Related Experiment Video
Updated: Sep 25, 2026


Irradiator Commissioning and Dosimetry for Assessment of LQ α and β Parameters, Radiation Dosing Schema, and in vivo Dose Deposition
Published on: March 11, 2021
Dose equivalence calculation in radiotherapy: A Call for Standardization
1Mines Paris, PSL University Centre for Observation, Impacts, Energy (O.I.E,) Sophia-Antipolis, Antibes 06904, France.

Abstract:
Accurate dose equivalence calculations are essential in radiotherapy to balance tumor control with tissue preservation. Despite decades of research, clinical implementation remains highly variable. A structured workshop analysis involving radiation oncologists, medical physicists, and technicians revealed alarming heterogeneity: when applying equivalent dose models (LQ/LQL) to identical clinical scenarios, mean inter practitioner agreement reached only 25.8% (Jaccard index), with consensus as low as 10% for head-and-neck cases. Proposed dose-per-fraction adjustments for identical situations ranged from 1.8 to 2.5 Gy, representing 15 to 20% biological dose variations (Kruskal-Wallis on the distribution of proposed doses across participant responses, case 1: p=0.18 head and neck, p=0.032 breast, p=0.027 bladder; p<0.05 for the three remaining cases). This variability persists across treatment interruptions, hypofractionation, and reirradiation: nearly 50% of surveyed centers cannot compute biologically equivalent schedules using available tools. Root causes include systematic reliance on the linear-quadratic model beyond the fraction sizes for which it is best established, outdated radiobiological parameters, and omission of repopulation correction despite international guidelines. Clinical consequences are not theoretical: for a 7-day treatment gap, institutional practices vary from 1.8 to 2.5 Gy compensatory fractions, potentially resulting in 10 to 15 Gy equivalent dose differences. In reirradiation, heterogeneous dose summation compromises spinal cord protection where small errors translate to irreversible myelopathy risk. Current practice depends on local tradition rather than evidence, creating unacceptable geographic disparities. Urgent harmonization through validated models, standardized workflows with mandatory repopulation correction, voxel-based BED/EQD2 assessment, and clearly defined professional accountability is imperative to ensure consistent, safe patient care.


Related Concept Videos
 02:59
Biological Effects of Radiation
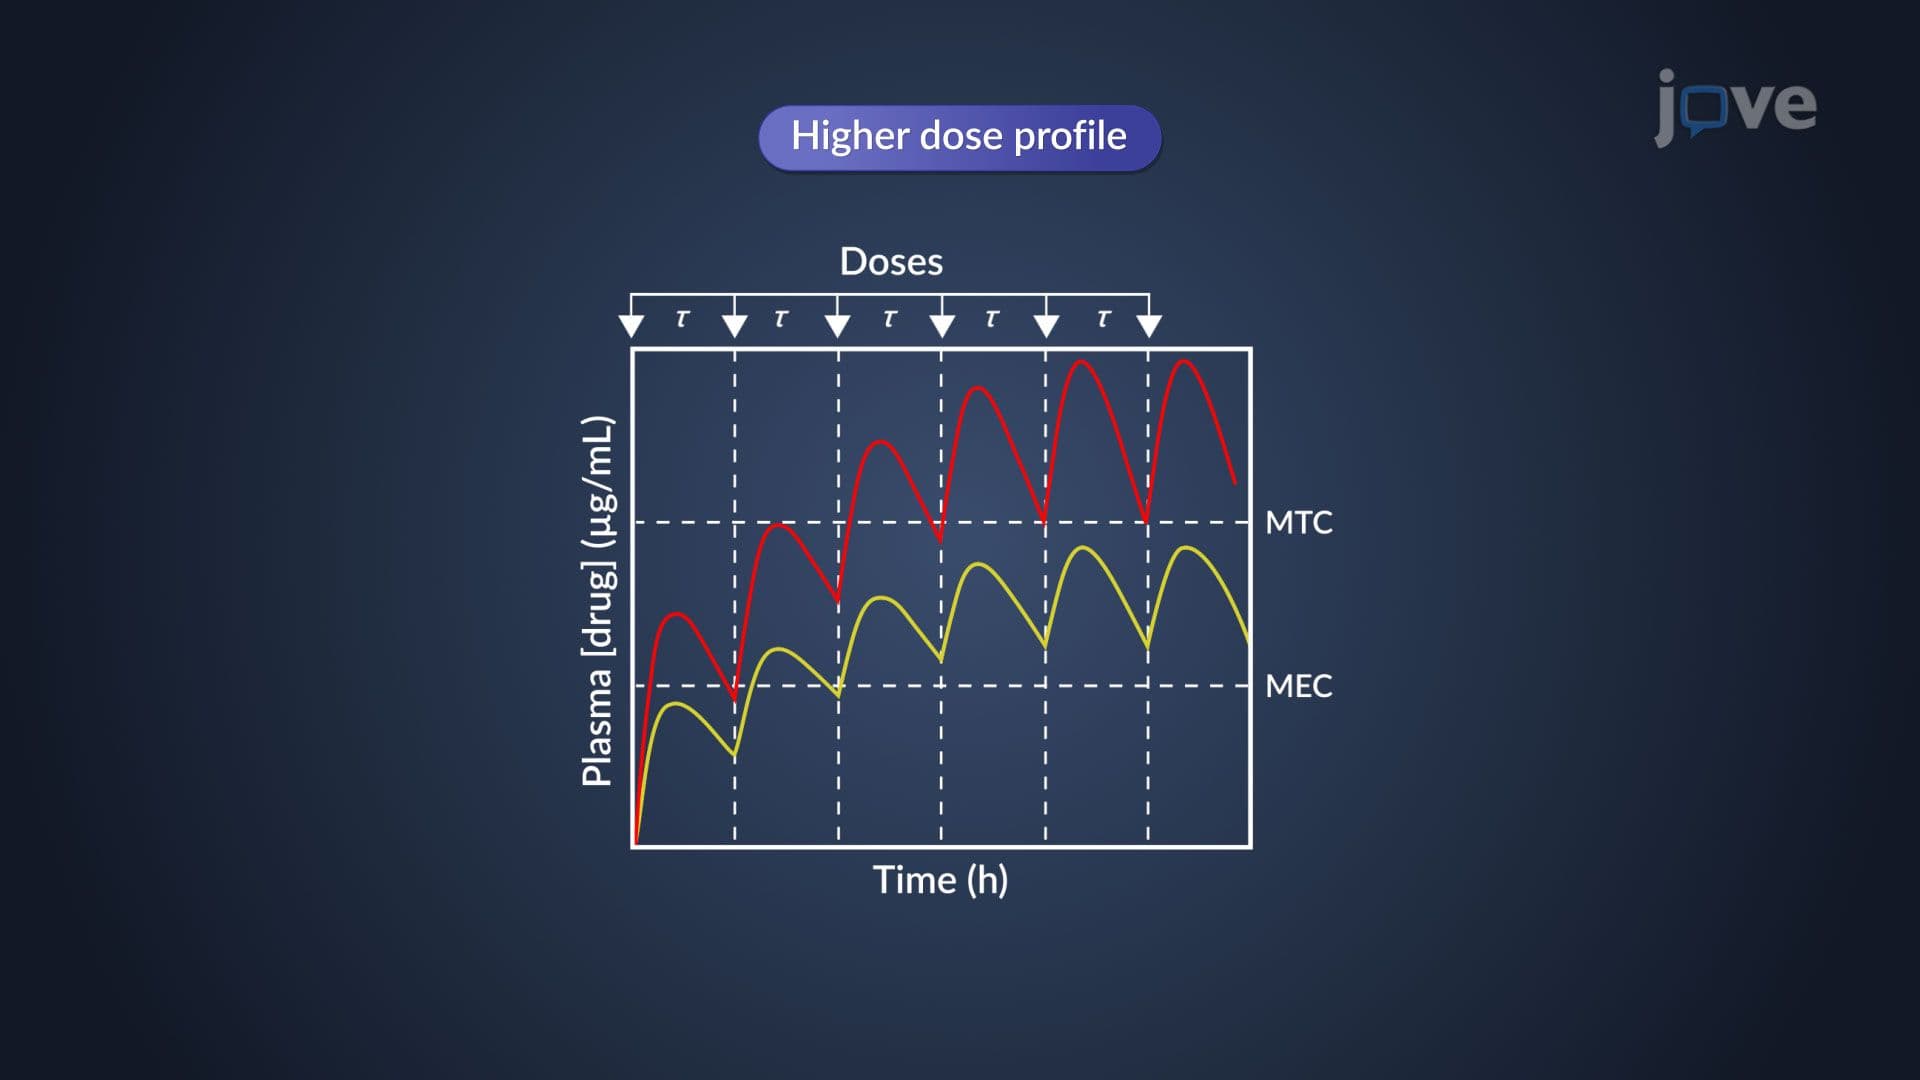 01:21
Dose Size and Dosing Frequency: Determination Methods
 01:25
Determination of Multiple Dosing Parameters: Loading and Maintenance Doses
 01:29
Drug Dosing: Infants and Children
 01:24
Dosage Regimen: Individualization
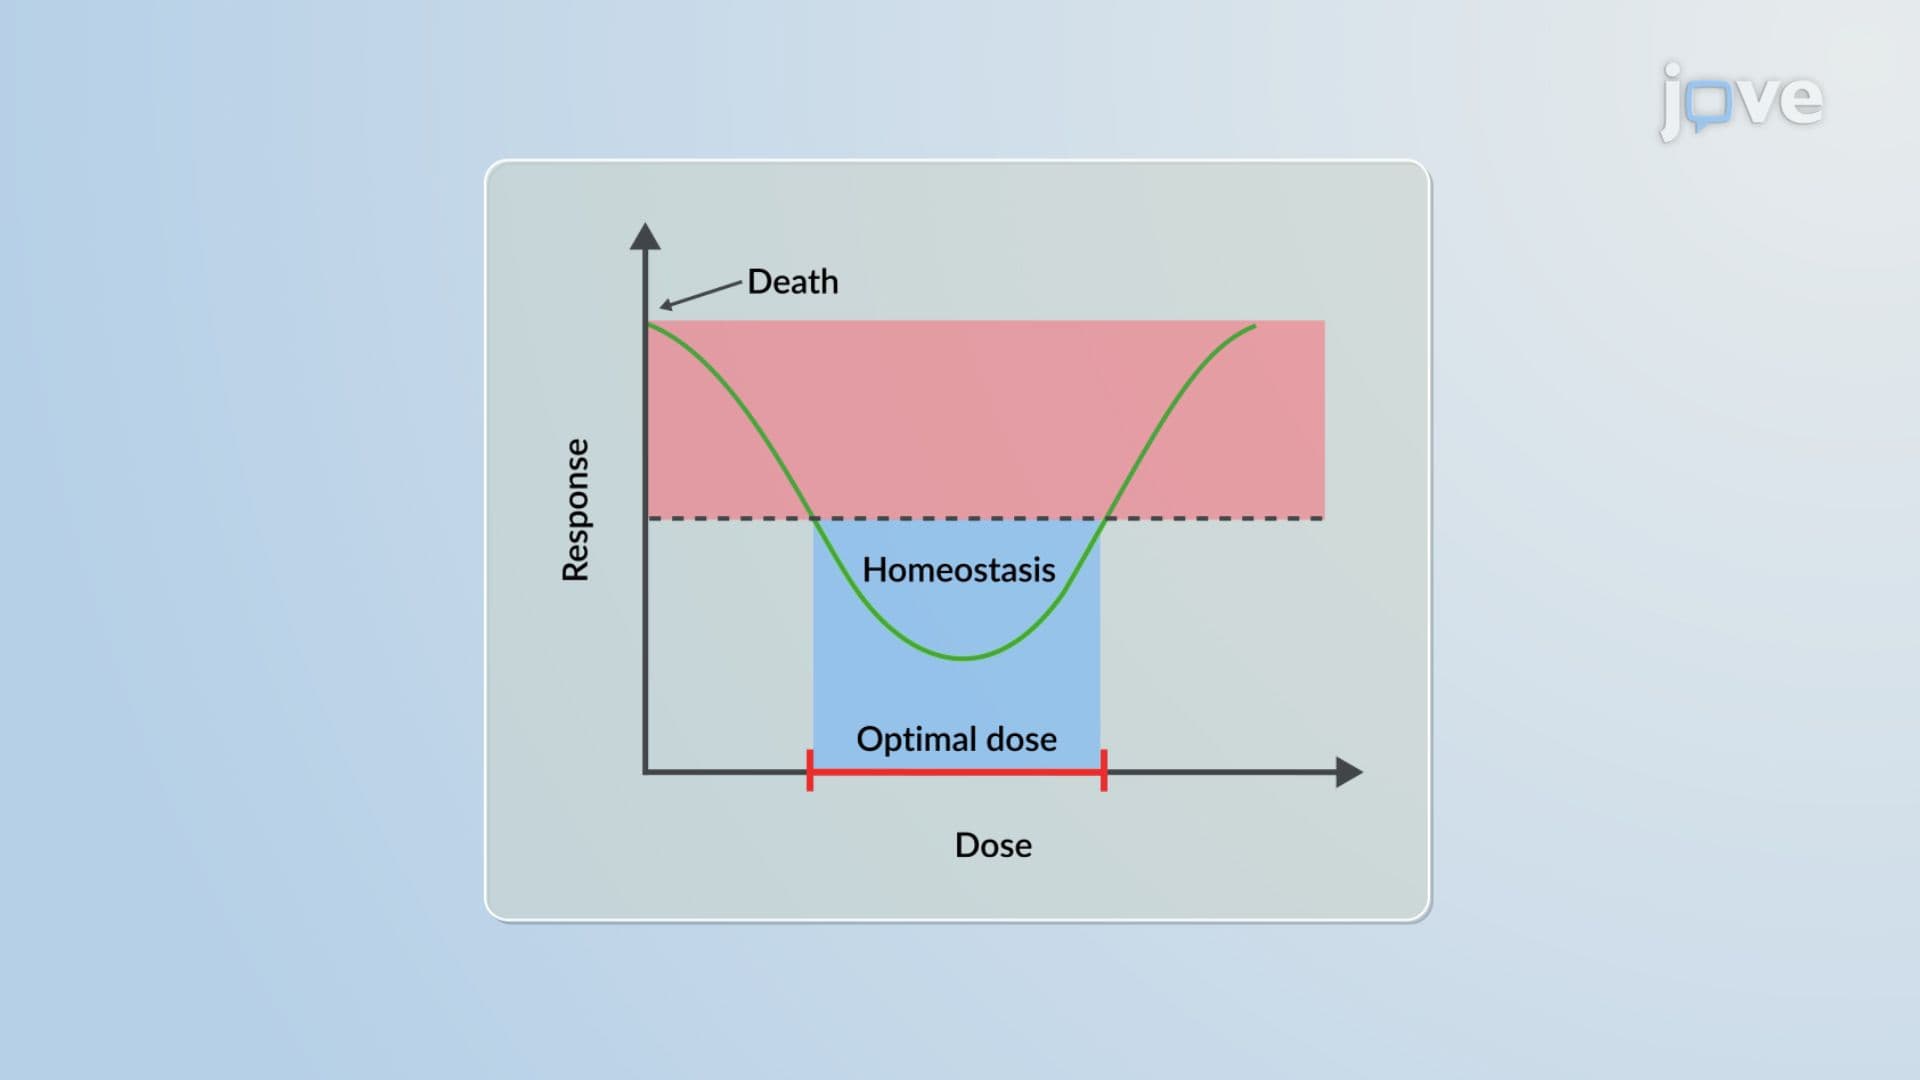 01:21
Dose Response Curve: Conventional Versus Nonmonotonic