Related Experiment Video
Updated: Sep 25, 2026
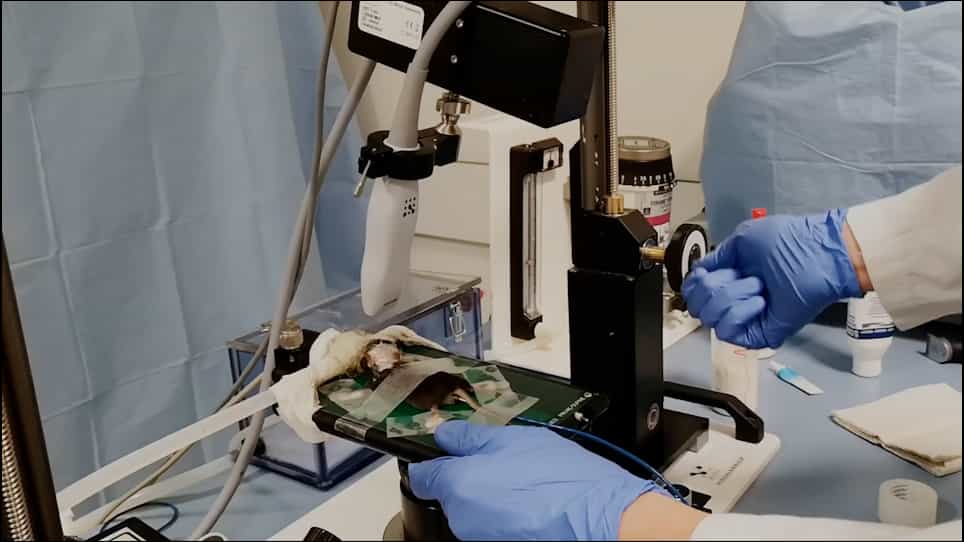

Analysis of Cerebral Vasospasm in a Murine Model of Subarachnoid Hemorrhage with High Frequency Transcranial Duplex Ultrasound
Published on: June 3, 2021
Diagnostic Yield of Repeat Myelography After an Initial Negative Study in Patients With Suspected Spontaneous
Andrew L Callen1, Kyle Jenkins2, Debayan Bhaumik2
1From the Department of Radiology (A.L.C., D.B., K.K., M.S.), Neurology (A.L.C., K.J.), Neuroradiology Section, University of Colorado Anschutz Medical Campus, Aurora, Colorado and Neurosurgery (T.B., P.L.), University of Colorado Anschutz Medical Campus, Aurora, Colorado. andrew.callen@cuanschutz.edu.

Background And Purpose:
Patients with suspected spontaneous intracranial hypotension and no spinal epidural fluid collection may harbor a CSF-venous fistula (CVF). When an initial myelogram is negative or shows only a suspicious finding, the value of another examination is uncertain. We measured the clinically supported yield of repeat myelography and sought features associated with positivity.
Materials And Methods:
This retrospective single-center study evaluated 71 patients with an earlier negative or nonlocalizing myelogram and, secondarily, 13 whose earlier suspicious target remained unresolved after treatment. Repeat reports were classified as definite, suspicious, or negative. Improvement after treatment directed to a suspicious (but not definite) finding provided clinical support. Clinical, MRI, and procedural features, including Bern-score strata, were explored in the primary cohort.
Results:
In the primary cohort, repeat myelography definitively localized a CVF in 3/71 patients (4.2%; 95% CI, 0.9%-11.9%). Four additional patients had treatment-responsive suspicious findings, producing a clinically supported yield of 7/71 (9.9%; 95% CI, 4.1%-19.3%). Clinically supported yield rose from 7.3% (3/41) at Bern scores of 0-2 to 12.5% (2/16) at 3-4 and 16.7% (2/12) at 5 or greater (P = .55). In the secondary cohort, 3/13 patients had definite localizations, all with photon-counting detector CT (PCCT). Across both cohorts, the yield was 10/84 (11.9%). Saline augmentation was used in 7/7 clinically supported cases and 31/59 negative repeats (P = .02). In post hoc analysis, yield was 5/19 with pressure- or exertion-provoked headache and 2/47 without this phenotype (relative risk, 6.18; 95% CI, 1.31-29.16; P = .02).
Conclusions:
After an earlier negative or nonlocalizing study, repeat myelography provided a definite or clinically supported localization in approximately 1 in 10 patients. Yield rose numerically with Bern score, but differences were not significant. All 3 definite localizations in the smaller secondary cohort were made with PCCT. Pressure- or exertion-provoked headache and saline augmentation warrant prospective evaluation.