Related Experiment Video
Updated: Sep 26, 2026


Single Incision Plus One Port Laparoscopic Proximal Gastrectomy with Double Channel Anastomosis for Gastric Cancer Treatment
Published on: December 27, 2024
Gastric fistula after 20 months of postoperative drain retention: a case report
Changzhi Chen1, Lin Li1, Jingfeng Qiu1
1Department of Hepatobiliary and Pancreatic Surgery, The Third Affiliated Hospital of Guangxi Medical University, Nanning, China.

Background:
In trauma or emergency surgery, postoperative drainage may be required for a prolonged period in selected patients because of complex injuries, contamination, or postoperative complications. However, visceral erosion, drain migration, and fistula formation related to long-term drain retention are rare but potentially serious.
Case Presentation:
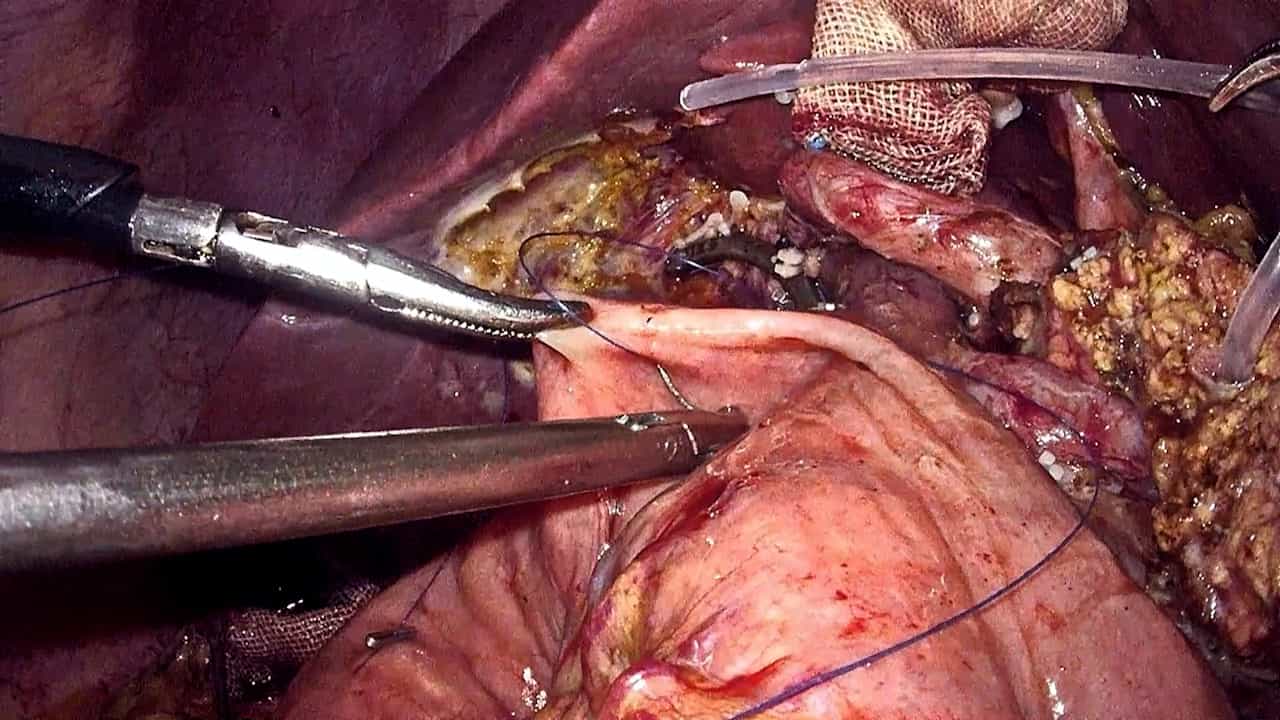
In April 2024, a 32-year-old man underwent emergency abdominal surgery after a traffic accident, including laparoscopic cholecystectomy and conversion to open splenectomy because of intraoperative bleeding, and a drainage tube was placed in the splenic fossa. Postoperatively, he developed intra-abdominal infection and postoperative pancreatic fistula. After five weeks of treatment at the outside hospital without significant improvement in symptoms or drainage, he was transferred to our department for further management in June 2024. After admission, computed tomography showed fluid accumulation in the splenectomy bed and an encapsulated collection anterior to the pancreatic body; the original drain was not located within the collection. Percutaneous drainage was performed for the fluid collection anterior to the pancreas. The amylase level in the peripancreatic drainage fluid was 9,526 U/L, compared with a serum amylase level of 75 U/L, supporting the diagnosis of pancreatic fistula. The drain in the splenic region was accidentally dislodged, and a new drainage catheter was promptly inserted through the existing sinus tract. After three weeks of therapy, the patient's symptoms improved and inflammatory markers returned to normal. However, persistent drainage remained, and he was discharged with both drains in place. By September 2024, at the first follow-up visit three months after discharge, the patient still had a daily drainage output of approximately 30-100 mL. The patient was subsequently lost to follow-up. In February 2026, he revisited our department because food residue was observed in the splenic fossa drain. Computed tomography showed that the splenic fossa drain was within the gastric cavity. The peripancreatic drain was removed, and the splenic fossa drain was gradually withdrawn under a clear liquid diet. Three days after complete drain removal, repeat computed tomography showed no intra-abdominal fluid collection and disappearance of the previous sinus tract. At three months after drain removal, the patient remained asymptomatic, with no evidence of recurrent infection or gastric fistula.
Conclusion:
Gastric fistula caused by long-term postoperative drain retention is extremely rare. In patients with long-term drainage tubes, the appearance of food residue, gas, abnormal drainage color, or sudden changes in drainage output should raise suspicion of gastrointestinal fistula. Regular follow-up, timely imaging reassessment, and individualized drain removal strategies are essential for preventing delayed drain-related visceral erosion.
Related Concept Videos
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD: