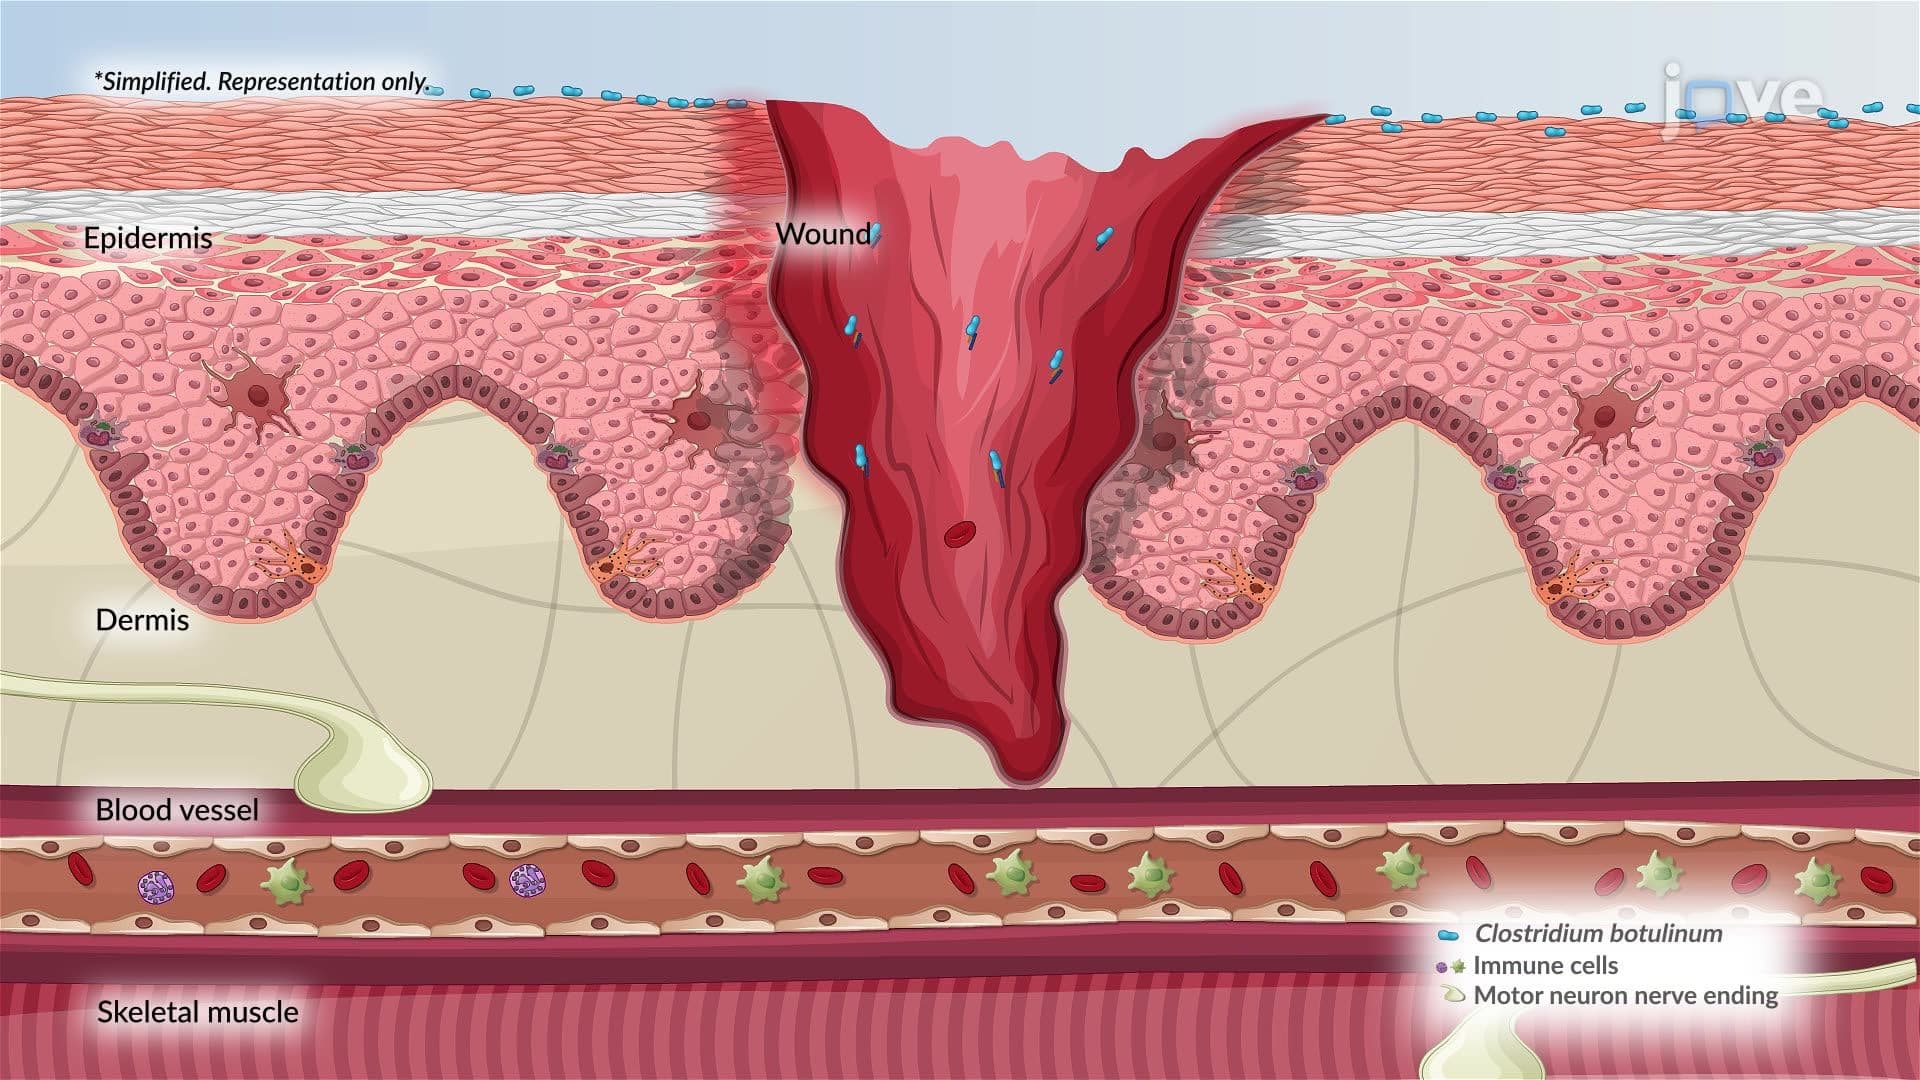
Related Experiment Video
Updated: Sep 26, 2026

Soft Pneumatic Robot Modulates Graph Theory Metrics of Brain Network for Hand Rehabilitation After Stroke
Published on: October 10, 2025
From Neurophysiological Mechanisms to Rehabilitation After Botulinum Toxin Type A in Post-Stroke Spasticity
Bart Eeckhaut1, Steven Truijen1, Parham Haghshenas1
1Department of Rehabilitation Sciences and Physiotherapy, Faculty of Medicine and Health Sciences, University of Antwerp, Universiteitsplein 1, 2610 Antwerpen, Belgium.

Background:
Botulinum toxin type A (BoNT-A) is globally recognized as a standard treatment for post-stroke spasticity (PSS), although its secondary mechanisms remain underinvestigated. The objective of this study was to investigate the neurophysiological mechanisms underlying BoNT-A treatment in PSS and explore their implications for mechanism-based rehabilitation.
Methods:
A systematic review and meta-analysis (PROSPERO registration number ID: CRD420261352230) of 39 studies involving 760 patients was conducted on 18 August 2026, following the Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA) guidelines. PubMed, Web of Science, Scopus, and Embase were systematically searched using the PICO framework. Where possible, quantitative data were pooled according to predefined neurophysiological constructs, including passive stretch-evoked activity, voluntary activation of the injected muscle, compound muscle action potential (CMAP), reciprocal motor control, normalized Hmax/Mmax, and specific spinal inhibitory mechanisms.
Results:
Quantitative synthesis demonstrated construct-specific neurophysiological changes following BoNT-A treatment. Passive stretch-evoked activity showed the largest pooled effect (Hedges' g = 0.80, 95% CI 0.35-1.24), followed by CMAP amplitude (g = 0.69, 95% CI 0.23-1.14) and reciprocal motor control (g = 0.52, 95% CI 0.23-0.81). Effects on voluntary activation of the injected muscle (g = 0.31, 95% CI -0.38 to 1.00) and normalized Hmax/Mmax (g = 0.22, 95% CI -0.74 to 1.17) were smaller and more heterogeneous. Reciprocal and recurrent inhibition were each represented by single-study estimates, while supraspinal outcomes were synthesized narratively due to methodological heterogeneity.
Conclusions:
The findings support a predominantly peripheral mechanism of BoNT-A while suggesting possible secondary changes within spinal and supraspinal motor control pathways. However, the certainty of evidence was low to very low. These neurophysiological effects provide a rationale for individualized, mechanism-based rehabilitation during the post-injection therapeutic window, although higher-quality evidence is required to confirm this framework.