Related Experiment Video
Updated: Sep 26, 2026


Biventricular Assessment of Cardiac Function and Pressure-Volume Loops by Closed-Chest Catheterization in Mice
Published on: June 15, 2020
Biventricular Pressure-Volume Loop Assessment of Impella 5.5 in an Acute ST-Segment-Elevation Myocardial Infarction
Sara S Inglis1,2, Serena Rahme2, Skylar A Rizzo2
1Department of Cardiovascular Medicine Mayo Clinic Rochester MN USA.

Background:
The Impella 5.5 is employed to provide left ventricular support in cardiogenic shock. Mechanistic understanding of biventricular relationships is essential in device optimization. Using a porcine model of acute myocardial infarction in tandem with pressure-volume loops, this study aimed to understand the impact of Impella 5.5 on biventricular hemodynamics.
Methods:
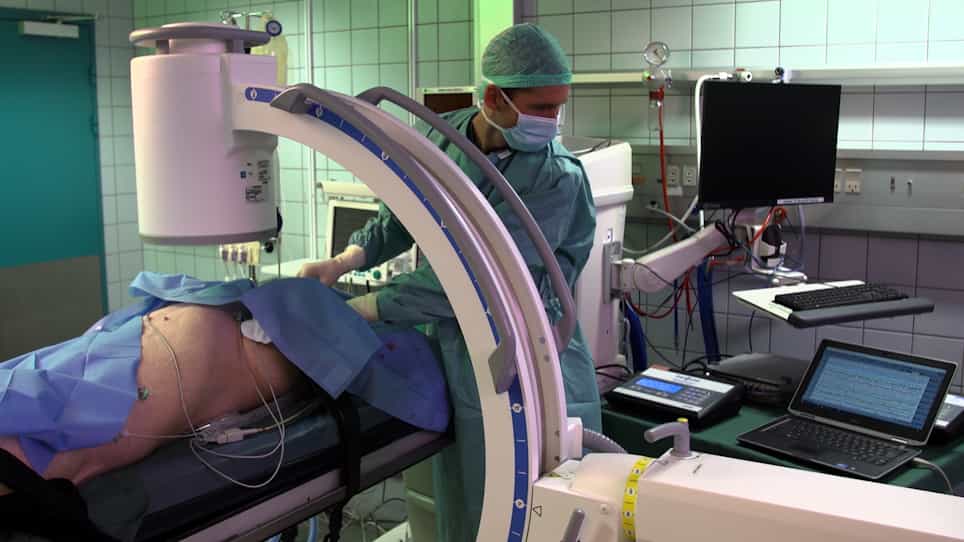
Using Domestic Yorkshire pigs, an Impella 5.5 was inserted percutaneously under fluoroscopic guidance via carotid/aortic access and an acute myocardial infarction was created. Biventricular pressure-volume loops and derived parameters were generated for each level of support before (n=6) and after myocardial infarction (n=6).
Results:
With increasing Impella 5.5 support, left ventricular pressure-volume loops shifted left, and right ventricular (RV) loops shifted right. In a healthy porcine heart, the RV adequately compensated for increased preload from the device, demonstrated by increased RV performance at higher P levels. After myocardial infarction, pigs were unable to tolerate speeds beyond P7 from diminished RV stroke volume reserve compared to healthy hearts. Median RV stroke volume percentage change from P1 to P9 before myocardial infarction was from 5.7% (interquartile range, -15.1% to 9.7%) to 50.6% (interquartile range, -11.6% to 60.2; P<0.05), and following acute myocardial infarction from P1 to P7 was from 3.9% (interquartile range, -2.7 to 78.4) to 13.4% (interquartile range, -8.9% to 147.2; P=0.94).
Conclusions:
Impella 5.5 speed modulation highlights significant interventricular interactions with opposing biventricular trends. While the heart can mount an improvement in RV stroke volume with increasing Impella 5.5 support, these data suggest an attenuated response following acute myocardial infarction, which may relate to inadequate response to increased preload needed by the device after infarction affecting the interventricular septum.