
Iatrogenic ventricular septal defect following papillary muscle premature ventricular contraction ablation: a case
Maria Luisa Benesch Vidal1,2, Niklas Schenker1,2, Katharina Alina Riedl1,2
1Department of Cardiology, University Medical Center Hamburg-Eppendorf, Martinistraße 52, Hamburg 20251, Germany.

Background:
Catheter ablation of monomorphic premature ventricular contractions (PVCs) in symptomatic or haemodynamically compromised patients has a Class I recommendation in cardiomyopathy and a Class IIa recommendation in patients comprising non-outflow tract PVC morphology and a physiologic anatomy according to current ESC guidelines. It is therefore widely performed and generally considered safe. Rare but clinically significant complications can occur and may present considerable diagnostic and therapeutic challenges.
Case Summary:
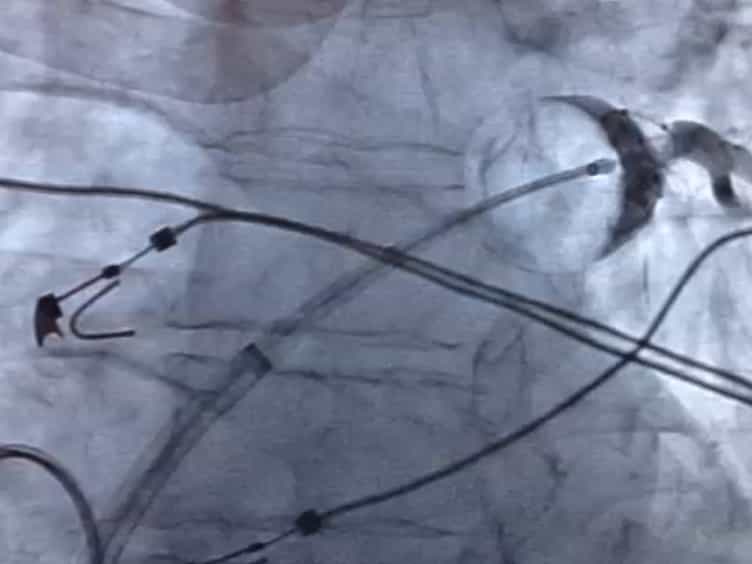
A 77-year-old woman underwent radiofrequency (RF) catheter ablation for symptomatic PVCs originating from the posteromedial papillary muscle. The acute procedural course was uneventful. Two months later, she presented with progressive dyspnoea. Transthoracic echocardiography revealed a newly developed haemodynamically significant ventricular septal defect (VSD) with left-to-right shunting. Retrospective analysis demonstrated anatomical concordance between the ablation site and the septal defect, suggesting an ablation-related iatrogenic VSD. Transoesophageal echocardiography confirmed an 8 mm defect. Cardiovascular magnetic resonance imaging demonstrated a significant shunt volume (Q p:Q s 1.7:1) and corresponding mild-to-moderate aortic, mitral, and tricuspid valve regurgitation secondary to volume overload. Right heart catheterization corroborated haemodynamic relevance. Following multidisciplinary heart team discussion, percutaneous closure was performed using a 12 mm muscular VSD occluder. Post-procedural imaging confirmed stable device position with minimal residual shunting and clinical improvement.
Discussion:
Iatrogenic VSD represents a rare but potentially serious delayed complication of RF catheter ablation for PVCs. Given the possibility of insidious onset, new heart failure symptoms or murmurs after ablation should prompt timely multimodality imaging. Structured follow-up may facilitate early detection and appropriate management of this uncommon but clinically relevant complication.


Related Concept Videos
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias
 01:29
Cardiomyopathy V: Interprofessional Care
 01:18
Dysrhythmias IV: Characteristics of Bradyarrhythmias
 01:27
Mitral Valve Prolapse I: Introduction