Related Experiment Video
Updated: Sep 29, 2026
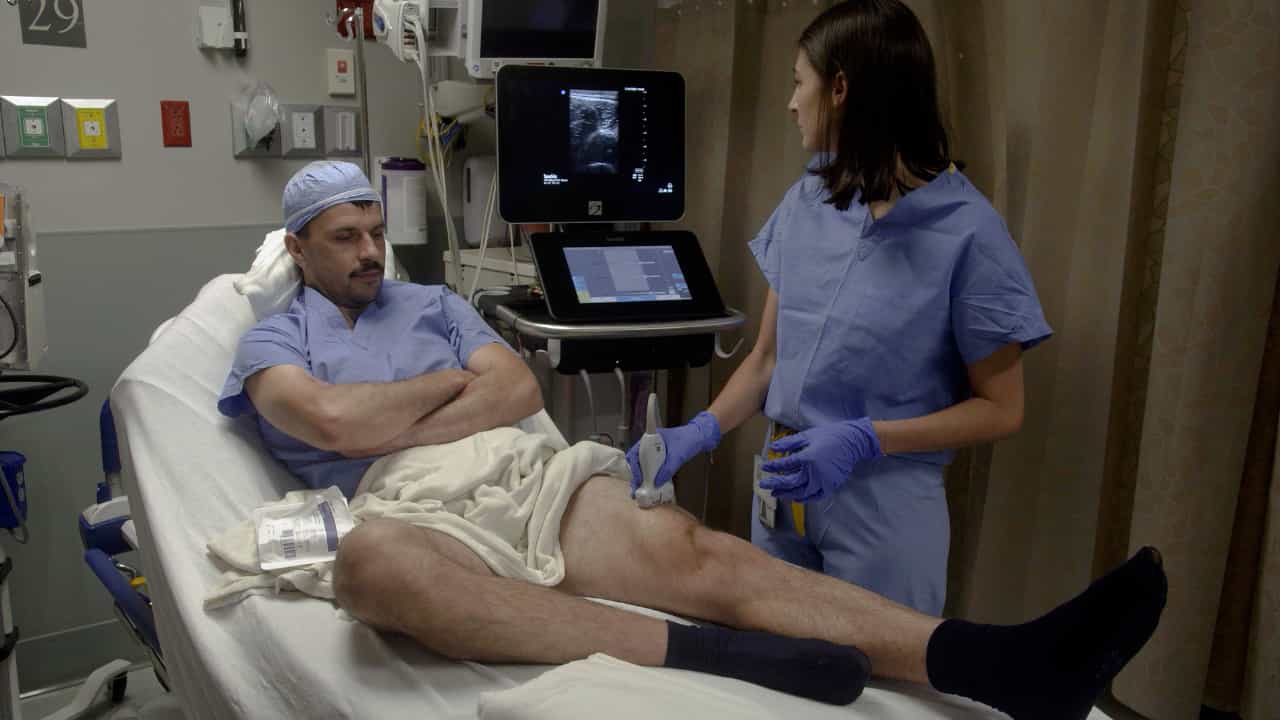

Identifying Frailty Using Point-of-Care Ultrasonography: Image Acquisition and Assessment
Published on: July 26, 2024
Association between Frailty and Reperfusion Treatments for Stroke by Age and Sex: A Retrospective Cohort Study
Manav V Vyas1, Moira K Kapral2, Amy Y X Yu3
1Division of Neurology, Department of Medicine, St. Michael's Hospital-Unity Health Toronto-University of Toronto, Canada.

Background:
The association between age and frailty and the use of thrombolysis or thrombectomy for acute ischemic stroke in females and males is not well understood.
Methods:
In a population-based retrospective cohort study of adults hospitalized with an ischemic stroke between April 1, 2018, and March 31, 2022, in Ontario, Canada, frailty was determined using a hospital-based frailty index (categorized as low, medium and high). In sex-stratified modified Poisson models estimated using generalized estimating equation methods, we evaluated the associations between age and frailty and the receipt of thrombolysis, thrombectomy, and 30-day mortality. Using interaction terms, we evaluated the modifying effect of frailty on the association between age and receipt of reperfusion therapy and mortality.
Results:
We included 59,346 patients with ischemic stroke, of whom 57.6% had medium and 38.9% had high frailty scores. In both sexes, older patients were less likely than younger patients to receive thrombolysis or thrombectomy and more likely to die within 30 days. Compared to those who were least frail, patients with high frailty were less likely to receive thrombolysis (adjusted risk ratio [aRR] female = 0.66 [0.57-0.77]; male = 0.72 [0.63-0.82]), but not thrombectomy (female = 0.87 [0.69-1.09]; male = 1.11 [0.88-1.39]). High frailty was associated with an increased risk of 30-day mortality in males (2.09, 1.52-2.87), but not females (1.22, 0.90-1.66).
Conclusions:
Frailty is independently associated with lower rates of thrombolysis in both sexes and increased mortality in males. Frailty should be accounted for when comparing the quality of acute stroke care and outcomes across jurisdictions.