Related Experiment Video
Updated: Sep 28, 2026
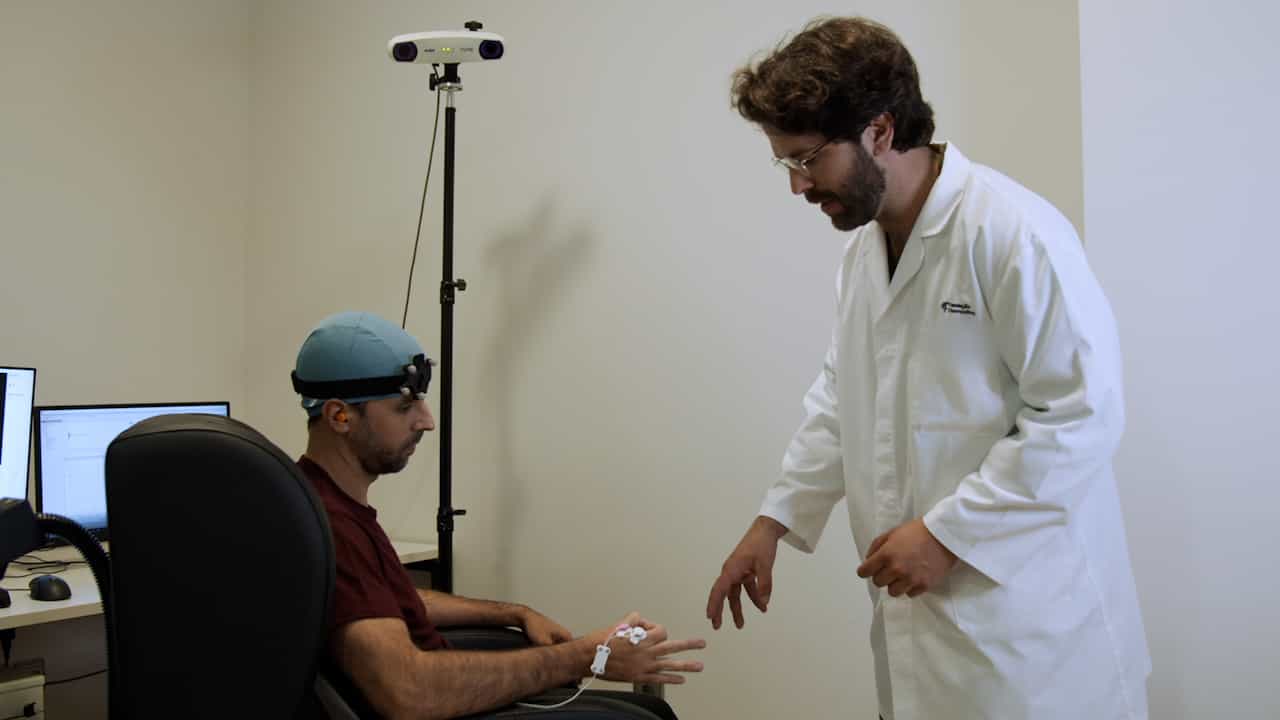

Assessing Primary Motor Cortex Excitability and Excitability Modulation by Pairing Transcranial Magnetic Stimulation with Electromyography
Published on: October 7, 2025
Theta burst stimulation with 80 and 120% resting motor threshold do not differ in their antidepressant efficacy: a
Mohamed A Abdelnaim1, Andreas Reissmann2, Katharina Kerkel2
1Department of Psychiatry and Psychotherapy, University of Regensburg, Universitaetsstr. 84, 93053, Regensburg, Germany. mohamed.abdelnaim@medbo.de.

Background:
rTMS, particularly intermittent theta burst stimulation (iTBS), is an effective treatment for treatment-resistant depression; however, the optimal stimulation intensity remains uncertain. Clinical protocols typically use intensities between 80 and 120% of resting motor threshold (RMT), but direct comparative evidence is limited.
Methods:
We conducted a retrospective analysis of 215 patients with unipolar or bipolar depression who received iTBS at either 120% RMT (n = 108) or 80% RMT (n = 107). Depression severity was assessed using the Hamilton Depression Rating Scale (HAMD-21) and Major Depression Inventory (MDI) before and after treatment. Response (≥ 50% symptom reduction) and remission (HAMD-21 ≤ 7; MDI ≤ 14) rates were compared between groups using mixed ANOVAs, with Bonferroni correction for multiple comparisons (p < .025). In addition, non-inferiority analyses were performed.
Results:
Both groups showed large, significant symptom reductions (HAMD-21: F(1,213) = 250.98, p < .001, partial η² = 0.541; MDI: F(1,213) = 247.45, p < .001, partial η² = 0.537). No significant group effects or group × time interactions emerged for either scale. In a formal non-inferiority analysis (ANCOVA adjusting for baseline severity), 80% RMT was non-inferior to 120% RMT on the HAMD-21 (adjusted difference - 0.90, 95% CI [- 2.61, 0.82]; margin 2.25 points), a result robust across sensitivity analyses. Response rates ranged from 30.84 to 38.32% and remission rates from 23.36 to 31.48%, with no significant differences between intensity groups. Side effects occurred in 20.56% (80% RMT) versus 27.77% (120% RMT) of patients. Notably, treatment-site pain necessitating intensity reduction occurred exclusively in the 120% RMT group (n = 5, 4.6%).
Conclusion:
iTBS at 80% RMT produced antidepressant outcomes non-inferior to iTBS at 120% RMT on the HAMD-21, with supportive MDI findings and better tolerability. These findings suggest a broader intensity range for antidepressant effects of iTBS and support the systematic investigation of lower-intensity protocols.


